

Clinical Subject Page
Myocardial Infarction (MI)
Also called
ICD-10
Specialty
Onset
Reviewed
-
OverviewOverview
-
Etiology & Risk FactorsEtiology & Risk Factors
-
PathophysiologyPathophysiology
-
Clinical PresentationClinical Presentation
-
Types of MITypes of MI
-
ECG Changes In MIECG Changes In MI
-
InvestigationsInvestigations
-
DiagnosisDiagnosis
-
ManagementManagement
-
ComplicationsComplications
-
PrognosisPrognosis
-
Key Points / Clinical PearlsKey Points / Clinical Pearls
Overview
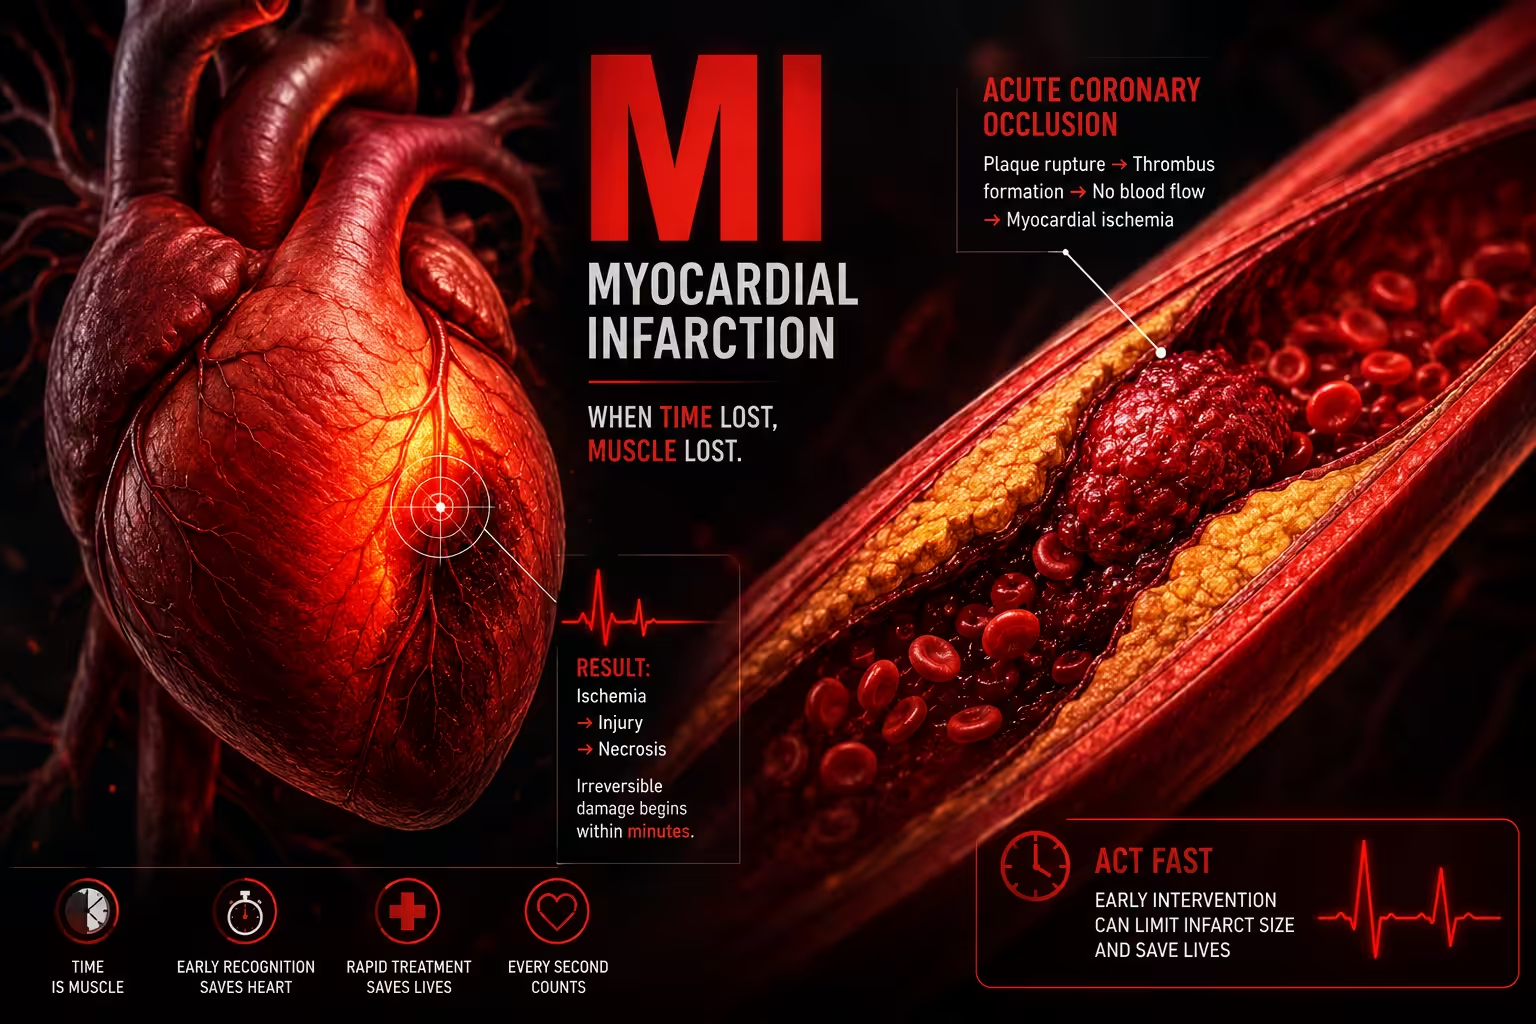
A myocardial infarction (MI), or heart attack, occurs when blood flow to part of the heart muscle is blocked long enough to cause ischemic necrosis (death of heart muscle tissue).
Etiology & Risk Factors
The main causes for Myocardial Infarction (MI) include:
- Coronary artery disease (CAD) – the most common cause
- Coronary artery vasospasm (e.g., Prinzmetal angina, cocaine use)
- Coronary artery dissection (e.g., spontaneous coronary artery dissection [SCAD])
- Coronary artery embolism (e.g., from atrial fibrillation or a prosthetic heart valve)
- Takotsubo cardiomyopathy
- Myocarditis
- Thrombophilia (e.g., polycythemia vera)
- Vasculitis (e.g., polyarteritis nodosa, Kawasaki syndrome)
- Myocardial oxygen supply-demand mismatch (Type 2 MI), such as:
- Hypotension
- Severe anemia
- Hypertrophic cardiomyopathy
- Severe aortic stenosis
Risk Factors ;
- Coronary vasospasm: cocaine use
- Spontaneous coronary artery dissection (SCAD):
- Pregnancy
- Fibromuscular dysplasia
- Connective tissue disorders (e.g., Marfan syndrome, Ehlers-Danlos syndrome, Loeys-Dietz syndrome)
- Inflammatory disorders
- Hormonal therapy
- Physical or emotional stress
- Stimulant drug use (e.g., cocaine, amphetamines)
Pathophysiology
- Atherosclerotic plaque rupture (Type 1 Myocardial Infarction (MI) ): An unstable, lipid-rich plaque with a thin fibrous cap ruptures. Macrophages release matrix metalloproteinases, weakening the fibrous cap and promoting rupture.
- Thrombus formation: Rupture exposes the highly thrombogenic lipid core, causing platelet activation and thrombus formation, which partially or completely occludes the coronary artery.
- Myocardial ischemia: Coronary artery occlusion reduces myocardial blood flow, producing an oxygen supply-demand mismatch and ischemia.
- Myocardial necrosis: If ischemia persists without reperfusion, irreversible death of myocardial cells (ischemic necrosis) occurs.
- Partial occlusion → Subendocardial infarction (NSTEMI)
- Complete occlusion → Transmural infarction (STEMI)
- Type 2 Myocardial Infarction (MI) : Occurs without plaque rupture when myocardial oxygen supply is inadequate or oxygen demand is increased (e.g., hypotension, anemia, bradycardia, sustained tachyarrhythmia, vasospasm, or coronary dissection).
Clinical Presentation
-Typical Symptoms
Acute retrosternal chest pain lasting >20 minutes
Dull, squeezing, or pressure-like chest discomfort
Pain may radiate to the left arm, shoulder, neck, jaw, chest, or epigastrium
Often precipitated by physical exertion or emotional stress
Dyspnea
Diaphoresis (profuse sweating)
Nausea and vomiting
Pallor
Dizziness, lightheadedness, or syncope
Anxiety
-Physical Findings
Tachycardia or arrhythmias
Signs of heart failure (e.g., pulmonary edema, orthopnea)
Signs of cardiogenic shock (e.g., hypotension, cold extremities)
New heart murmur (e.g., S4)
Atypical Presentation of Myocardial Infarction (MI)
More common in older adults, women, and patients with diabetes:
Little or no chest pain (silent Myocardial Infarction MI)
Sharp or stabbing chest pain
Predominantly autonomic symptoms (e.g., nausea, diaphoresis)
-Inferior Wall Myocardial Infarction (MI)
Epigastric pain
Bradycardia
Right ventricular infarction may present with:
Hypotension
Elevated jugular venous pressure (JVP)
Clear lung fields
Types of Myocardial Infarction (MI)
Myocardial Infarction · Universal Classification (4th Universal Definition 2018)
| Type | Mechanism | ECG findings | Troponin | Coronary angiography | Treatment |
|---|---|---|---|---|---|
| Type 1 Spontaneous |
Atherosclerotic plaque rupture or erosion → coronary thrombus → partial or complete occlusion Includes: STEMI, NSTEMI, UA |
STEMI: ST elevation ≥1mm in ≥2 contiguous leads or new LBBB NSTEMI: ST depression, T-wave inversion, or normal |
Elevated Rise & fall pattern above 99th percentile URL | Obstructive CAD with culprit lesion; thrombus visible |
STEMI: Primary PCI <90 min (or thrombolysis if PCI unavailable) NSTEMI: Anticoagulation, antiplatelet, early invasive strategy |
| Type 2 Secondary |
Supply-demand mismatch without plaque rupture: • Coronary spasm • Embolism • Tachyarrhythmia • Severe anaemia • Hypertensive crisis • Respiratory failure |
ST depression, T-wave changes, or diffuse ST changes depending on cause; may be non-specific | Elevated Often modest rise; correlates with degree of ischaemia | Normal or non-obstructive coronaries (<50% stenosis) in many cases; no culprit thrombus | Treat underlying cause (arrhythmia, anaemia, hypoxia). Antiplatelet ± anticoagulation based on context |
| Type 3 Fatal MI |
Presumed MI causing sudden cardiac death before biomarkers or ECG can be obtained. Autopsy may confirm coronary thrombus or plaque rupture. | ECG may show new ST changes or LBBB before death; often unavailable | Unavailable Patient dies before blood drawn or results returned | Post-mortem angiography or autopsy findings | CPR / ACLS. Post-mortem diagnosis. Family counselling and genetic screening if inherited cause suspected. |
| Type 4a Peri-PCI |
MI occurring within 48h of PCI due to: side branch occlusion, slow/no reflow, dissection, embolisation of atherosclerotic debris | New ST changes or new LBBB post-procedure | Elevated cTn >5× 99th percentile URL with rise from normal baseline, or >20% rise if already elevated | Post-PCI: may show side branch loss, dissection, or no-reflow phenomenon | GP IIb/IIIa inhibitors, intracoronary vasodilators (adenosine), thrombectomy; IABP if haemodynamically compromised |
| Type 4b Stent thrombosis |
Acute, subacute, late, or very late stent thrombosis confirmed angiographically or at autopsy. Risk: dual antiplatelet non-adherence, stent underexpansion | Acute STEMI pattern in stented territory | Elevated Same as Type 1 criteria | Thrombus within previously placed stent confirmed on angiography | Emergency PCI; aspiration thrombectomy; optimise DAPT (prasugrel/ticagrelor preferred) |
| Type 4c Restenosis |
In-stent restenosis or restenosis at balloon angioplasty site causing ischaemia — intimal hyperplasia, not thrombosis | ST depression or T-wave changes in territory of prior PCI | Elevated Meets MI criteria in setting of prior PCI | Luminal narrowing at stent site without thrombus; no new culprit lesion | Repeat PCI with drug-eluting balloon or new DES; CABG if anatomy unfavourable |
| Type 5 CABG-related |
Perioperative MI within 48h of CABG: graft occlusion, inadequate myocardial protection, coronary spasm, air embolism | New Q waves ≥0.02s or new LBBB post-operatively | Elevated cTn >10× 99th percentile URL from normal baseline; or >20% rise if already elevated | Graft occlusion or native vessel disease on post-op angiography; diffuse ischaemia on imaging | Urgent re-angiography; surgical revision if graft occluded; IABP / mechanical support; optimise antiplatelet |
ECG Changes In Myocardial Infarction (MI)
ECG Changes in Myocardial Infarction · Systematic Guide
| Territory | Artery (culprit) | Leads with ST elevation | Reciprocal ST depression | Clinical notes |
|---|---|---|---|---|
| Inferior MI | RCA (80%) or LCx (20%) |
II
III
aVF
|
I
aVL
|
Most common STEMI. Check RV involvement with V4R. Hypotension may indicate RV infarct — avoid nitrates. |
| Lateral MI | LCx or diagonal branch of LAD |
I
aVL
V5
V6
|
II
III
aVF
|
High lateral (I, aVL) — often from small diagonal. Low lateral (V5, V6) — LCx territory. May be subtle. |
| Anterior MI | LAD (proximal) |
V1
V2
V3
V4
|
II
III
aVF
|
Largest territory — worst prognosis. Proximal LAD occlusion → anteroseptal + lateral involvement. Risk of LBBB, CHB. |
| Septal MI | LAD (septal perforators) |
V1
V2
|
— | Isolated septal MI uncommon. Often part of anteroseptal MI. Risk of complete heart block and VSD. |
| Posterior MI | RCA or LCx (dominant) | No ST elevation in standard leads |
V1
V2
V3
ST depression + tall R + upright T in V1–V3 = posterior STEMI equivalent
|
Must use posterior leads V7–V9 to confirm — ST elevation ≥0.5mm in V7–V9 is diagnostic. Frequently missed. |
| RV MI | Proximal RCA |
V1
V4R
Right-sided leads V3R–V6R
|
— | Always consider with inferior STEMI (II,III,aVF). Triad: hypotension + JVD + clear lungs. Nitrates & diuretics CONTRAINDICATED. |
Type B: Deep symmetric T inversion in V2–V3.
Seen after chest pain resolves. Indicates critical proximal LAD stenosis. Stress test CONTRAINDICATED — can precipitate massive MI.
Investigations
1. Electrocardiogram (ECG) – First-line Investigation in Myocardial Infarction (MI)
12-lead ECG should be performed immediately.
Findings:
ST-segment elevation (STEMI)
ST-segment depression or T-wave inversion (NSTEMI)
Pathological Q waves (myocardial necrosis)
Repeat serial ECGs if initial ECG is nondiagnostic.
2. Cardiac Biomarkers
Cardiac troponin I or T (most sensitive and specific marker)
High-sensitivity assays: rise in 1–3 hours
Peak: 12–24 hours
Remain elevated for 7–10 days
CK-MB
Rise: 4–9 hours
Returns to normal in 2–3 days
May help detect reinfarction.
3. Laboratory Tests
CBC
Renal function and electrolytes
CRP and WBC
Coagulation profile
BNP/NT-proBNP (if heart failure is suspected)
4. Coronary Angiography
Gold standard for identifying coronary artery occlusion.
Confirms diagnosis and allows percutaneous coronary intervention (PCI).
5. Transthoracic Echocardiography
Detects regional wall motion abnormalities
Assesses left ventricular function (LVEF)
Identifies complications (e.g., mitral regurgitation, ventricular aneurysm, pericardial effusion, free wall rupture)
Diagnosis of Myocardial Infarction (MI)
1. Electrocardiogram (ECG) – First-line Investigation
12-lead ECG should be performed immediately when Myocardial Infarction (MI) is suspected.
Findings:
ST-segment elevation (STEMI)
ST-segment depression or T-wave inversion (NSTEMI)
Pathological Q waves (myocardial necrosis)
Repeat serial ECGs if initial ECG is nondiagnostic.
2. Cardiac Biomarkers
Cardiac troponin I or T (most sensitive and specific marker)
High-sensitivity assays: rise in 1–3 hours
Peak: 12–24 hours
Remain elevated for 7–10 days
CK-MB
Rise: 4–9 hours
Returns to normal in 2–3 days
May help detect reinfarction.
3. Laboratory Tests
CBC
Renal function and electrolytes
CRP and WBC
Coagulation profile
BNP/NT-proBNP (if heart failure is suspected)
4. Coronary Angiography
Gold standard for identifying coronary artery occlusion.
Confirms diagnosis and allows percutaneous coronary intervention (PCI).
5. Transthoracic Echocardiography
Detects regional wall motion abnormalities
Assesses left ventricular function (LVEF)
Identifies complications (e.g., mitral regurgitation, ventricular aneurysm, pericardial effusion, free wall rupture)
Management of Myocardial Infarction (MI)
Initial Management for All ACS Patients
Monitoring
• Continuous telemetry
• Serial ECGs
• Serial troponins
Oxygen
• Supplement oxygen as needed to maintain saturation ≥ 90%
Antiplatelet Therapy
• Aspirin
• P2Y12 inhibitor
• Dual antiplatelet therapy (DAPT)
Anticoagulation
• Parenteral anticoagulation (e.g., UFH)
Additional Medical Therapy
• Statins
• Beta blockers
• RAAS inhibitors
• Analgesia for chest pain
MONA-BASH Mnemonic
| Letter | Therapy |
|---|---|
| M | Morphine |
| O | Oxygen |
| N | Nitroglycerin |
| A | Antiplatelet drugs |
| B | Beta blockers |
| A | ACE inhibitors |
| S | Statins |
| H | Heparin |
Complications of Myocardial Infarction (MI)
Early (0–24 hours)
Arrhythmias (especially ventricular fibrillation) – common cause of early death
Sudden cardiac death
Acute heart failure → pulmonary edema
Cardiogenic shock
1–3 days
Early fibrinous pericarditis (usually self-limiting)
3–14 days
Papillary muscle rupture → acute mitral regurgitation
Ventricular septal rupture → acute VSD
Left ventricular free wall rupture → cardiac tamponade
Ventricular pseudoaneurysm
Weeks to months
True ventricular aneurysm → mural thrombus
Dressler syndrome (post-MI autoimmune pericarditis)
Mural thrombus → systemic thromboembolism (e.g., stroke)
Arrhythmias
Congestive heart failure
Reinfarction
Prognosis of Myocardial Infarction (MI)
-
-
- Early reperfusion therapy reduces the extent of myocardial necrosis and helps prevent complications such as early pericarditis.
- Early infarct-associated pericarditis is usually self-limiting.
- Prevention of recurrent Myocardial Infarction (MI) and complications includes:
- Dual antiplatelet therapy
- Statin therapy
- Beta blockers and/or ACE inhibitors
- Management of modifiable cardiovascular risk factors
-
Key Points / Clinical Pearls of Myocardial Infarction (MI)
- Myocardial Infarction (MI) = ischemic necrosis of heart muscle, most commonly due to coronary artery disease.
- Diagnosis of Myocardial Infarction (MI) is based on:
- Typical symptoms
- ECG changes
- Elevated cardiac biomarkers
- Cardiac catheterization confirms the diagnosis and enables treatment.
- Emergency revascularization should be considered in suspected Myocardial Infarction (MI).
- Remember the timing of major complications of Myocardial Infarction (MI):
- 0–24 h: Arrhythmias, cardiogenic shock, heart failure
- 1–3 d: Pericarditis
- 3–14 d: Papillary muscle rupture, VSD, free wall rupture
- Weeks–months: Ventricular aneurysm, Dressler syndrome, heart failure, reinfarction
- National Center for Biotechnology Information (NIH). Myocardial Infarction, StatPearls.
- Thygesen K, Alpert JS, Jaffe AS, et al. Fourth Universal Definition of Myocardial Infarction (2018). Eur Heart J. 2019;40:237-269. PMID: 30154043.
- Bhatt H, Ludhwani D. National Center for Biotechnology Information (NIH). Acute ST-Segment Elevation Myocardial Infarction (STEMI), StatPearls.
- MedlinePlus, National Library of Medicine (NIH). Heart Attack: Health Topic.
- Rao SV, O'Donoghue ML, Ruel M, et al. 2025 ACC/AHA/ACEP/NAEMSP/SCAI Guideline for the Management of Patients With Acute Coronary Syndromes. Circulation. 2025;151:e771-e862. doi: 10.1161/CIR.0000000000001309.