

Clinical Subject Page
Mitral Regurgitation
Also called
ICD-10
Specialty
Onset
Reviewed
-
OverviewOverview
-
Etiology & Risk FactorsEtiology & Risk Factors
-
PathophysiologyPathophysiology
-
Clinical PresentationClinical Presentation
-
History TakingHistory Taking
-
Mitral Stenosis Vs Mitral RegurgitationMitral Stenosis Vs Mitral Regurgitation
-
InvestigationsInvestigations
-
DiagnosisDiagnosis
-
ManagementManagement
-
ComplicationsComplications
-
PrognosisPrognosis
-
Key Points / Clinical PearlsKey Points / Clinical Pearls
Overview
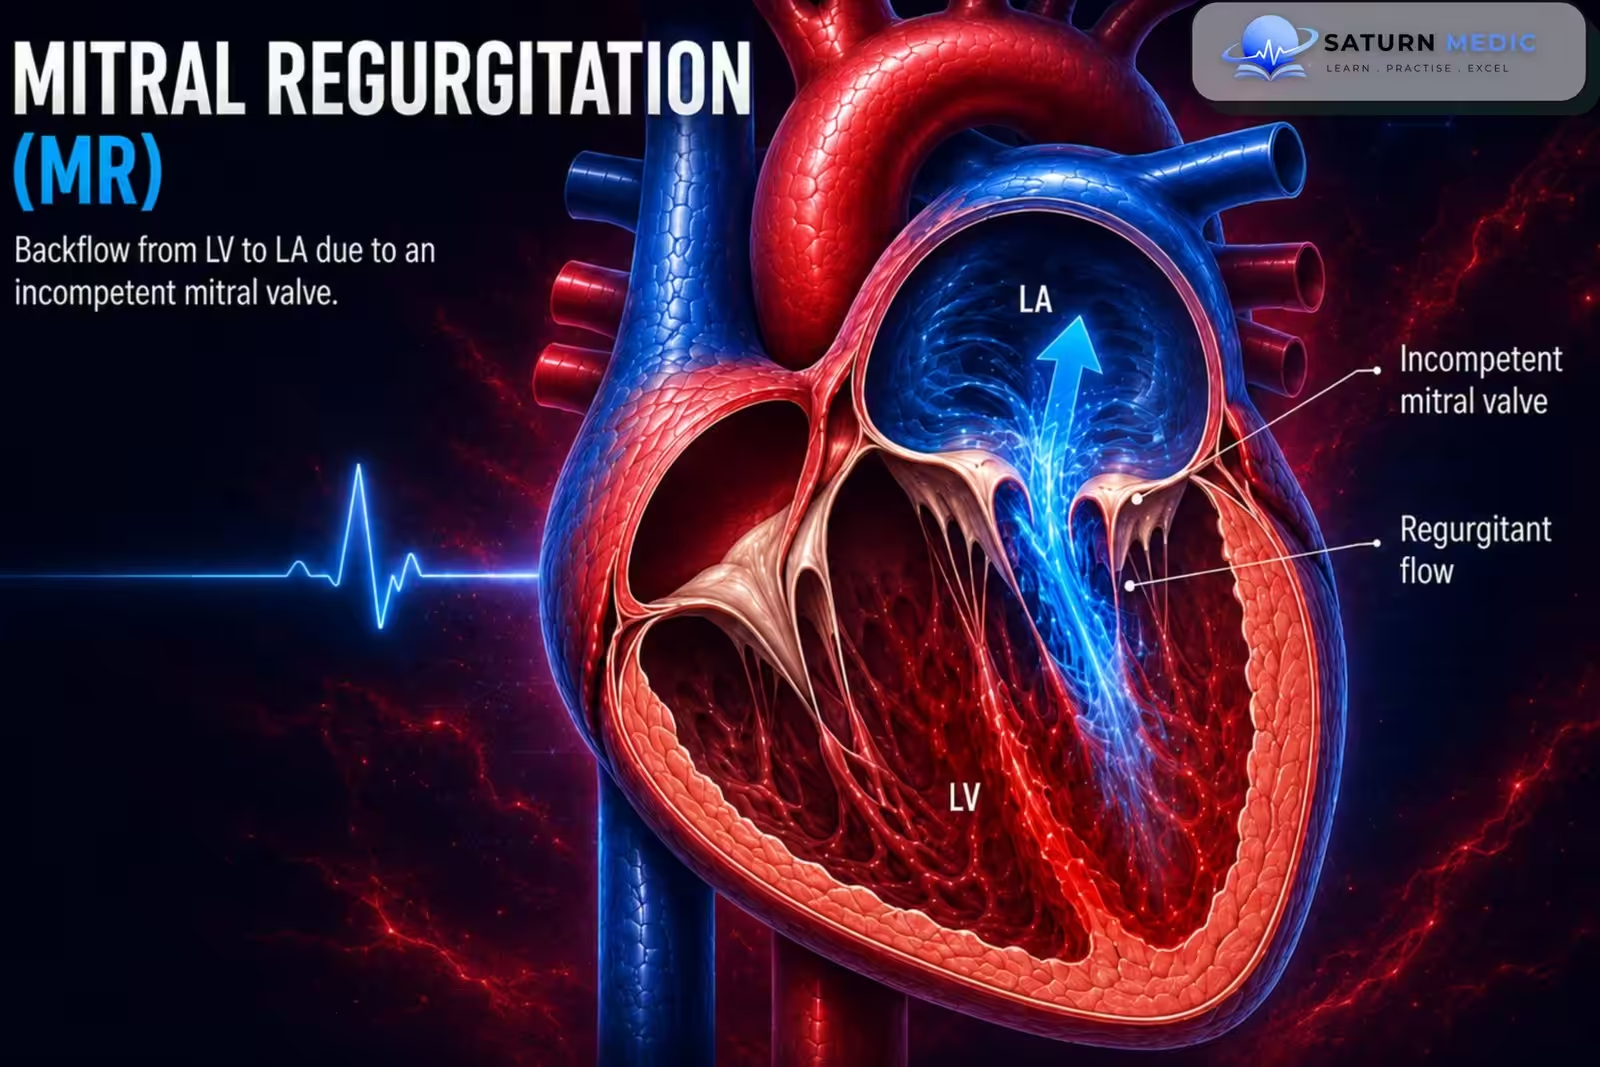
Mitral regurgitation (MR) is a leakage of blood from the left ventricle back into the left atrium because the mitral valve does not close completely during systole. This reduces the amount of blood pumped forward and can eventually lead to left-sided heart failure.
Etiology & Risk Factors
Primary (Organic) MR
Caused by disease of the mitral valve itself.
Mitral valve prolapse (most common degenerative cause)
Mitral annular calcification
Ruptured chordae tendineae
Rheumatic fever
Infective endocarditis
Ischemic MR (e.g., papillary muscle rupture after acute myocardial infarction)
Secondary (Functional) MR
Caused by left ventricular disease leading to valve incompetence.
Coronary artery disease (CAD)
Previous myocardial infarction (MI)
Dilated cardiomyopathy
Left-sided heart failure
Risk Factors
Mitral valve prolapse
Coronary artery disease
Previous myocardial infarction
Dilated cardiomyopathy
Heart failure
Rheumatic fever
Infective endocarditis
Mitral annular calcification
Pathophysiology
Acute MR
The mitral valve fails to close, causing blood to flow back from the left ventricle (LV) into the left atrium (LA) during systole.
This causes:
Rapid increase in LA pressure
Pulmonary venous congestion
Pulmonary edema
Increased LV volume overload to maintain cardiac output
Chronic MR
Long-term volume overload causes:
Left atrial enlargement
Left ventricular dilation (eccentric hypertrophy)
Initially, the heart compensates and maintains cardiac output.
Over time, LV dysfunction develops, leading to:
Reduced stroke volume
Increased LA and LV pressures
Pulmonary congestion
Pulmonary hypertension
Right heart strain
Simple Flow
Mitral valve doesn’t close properly → Blood leaks back into LA during systole → LA & LV volume overload → LV dilation → Heart failure → Pulmonary hypertension (late)
Clinical Presentation
Acute MR
Symptoms
Sudden dyspnea
Pulmonary edema
Palpitations
Symptoms of left-sided heart failure
Cardiogenic shock (severe cases)
Examination
Soft decrescendo murmur (may be absent in severe MR)
S3 heart sound may be present
Chronic MR
Symptoms
Exertional dyspnea
Fatigue
Palpitations (often due to atrial fibrillation)
Dry cough
Symptoms of left-sided heart failure
Later, symptoms of right-sided heart failure
Examination
Holosystolic (pansystolic), high-pitched blowing murmur
Best heard at the apex
Radiates to the left axilla
Quiet S1
S3 heart sound (advanced disease)
Displaced apical impulse
History Taking
- “Do you get short of breath when walking or climbing stairs?”
- “Do you become short of breath when lying flat?”
- “Do you wake up at night feeling short of breath?”
- “Do you feel your heart racing or skipping beats?”
- “Do you feel tired more easily than before?”
- “Do you have a dry cough?”
- “Have you had chest pain or a recent heart attack?”
- “Have you ever had rheumatic fever or infective endocarditis?”
- “Do you have swelling in your legs or ankles?”
Mitral Stenosis Vs Mitral Regurgitation
Cardiology · Valvular Heart Disease — Mitral Stenosis vs Mitral Regurgitation
Normal area: 4–6 cm² | Severe: <1 cm²
Most common cause: Rheumatic fever
Volume overload of both LA and LV
Most common cause: MVP / rheumatic / ischaemic
Timing Diastolic — after S2, continues toward S1
Radiation Does not radiate
Character Low-pitched, rumbling
Special Loud S1 | Opening snap after S2
Positional Louder in left lateral decubitus
S1┈┈┈S2┈OS┈╾╾╾rumble╿╿╿┈S1
└ Shorter S2–OS interval = more severe stenosis (higher LA pressure)
Timing Throughout systole — S1 to S2
Radiation Axilla / left infrascapular
Character Blowing, high-pitched
Special Soft/absent S1 | S3 gallop (volume overload)
Positional Louder with squatting & expiration
S1┈╾╾╾╾╾╾╾╾╾S2┈┈┈┈┈┈S1
└ Uniform throughout systole — does not change with S1 or S2
P in V1 Biphasic — prominent negative terminal deflection
QRS Usually normal (LV not overloaded)
Late finding RVH pattern (RAD, dominant R in V1) if pulmonary HTN
Rhythm Atrial fibrillation common (LA dilation)
┈/╾╿┈P-mitrale┈┈┈┈narrow QRS┈┈┈┈
└ P mitrale = LA enlargement signature — notched P >2.5 mm wide in II
QRS LVH pattern — tall R in V5/V6, deep S in V1/V2
Axis LAD (LV volume overload)
Rhythm AF common (LA dilation, same as MS)
Key diff LVH present in MR — absent in MS
┈/╾╿┈P-mitrale┈┈tall QRS (LVH)┈┈
└ LVH on ECG = volume overload — key distinguisher from pure MS
| Feature | Mitral Stenosis | Mitral Regurgitation |
|---|---|---|
| Murmur timing | Mid-diastolic rumble | Pansystolic blowing |
| Best heard | Apex, left lateral decubitus | Apex, radiates to axilla |
| S1 | Loud (early) → soft (late/calcified) | Soft / obscured |
| Extra sounds | Opening snap (OS) after S2 | S3 gallop (volume overload) |
| ECG P wave | P mitrale (broad, notched) | P mitrale (broad, notched) |
| ECG QRS | Normal (RVH if pulm HTN) | LVH pattern |
| CXR heart size | LA enlarged, LV normal | LA + LV both enlarged |
| Pulmonary oedema | Chronic (gradual venous HTN) | Acute (sudden decompensation) |
| LV function | Preserved (underfilled) | Dilated → EF may fall |
| AF risk | Very high (thrombus → stroke) | High (LA dilation) |
| Main cause | Rheumatic fever | MVP, rheumatic, ischaemic, IE |
| Intervention | PTMC (balloon) or MVR | Repair preferred over replacement |
| Surgery trigger | MVA <1.5 cm² + symptoms | EF ≤60% or ESD ≥40 mm |
Investigations
1. Transthoracic Echocardiography (TTE) – Gold Standard
First-line and diagnostic test of choice
Assesses:
Severity of mitral regurgitation
Mitral valve anatomy
Left atrial and left ventricular size and function
2. Transesophageal Echocardiography (TEE)
If TTE is inadequate
Performed before surgery to better evaluate the valve
3. ECG
May show:
Atrial fibrillation
Left ventricular hypertrophy (LVH)
Left atrial enlargement (P mitrale)
Right heart strain in advanced disease
4. Chest X-ray
Assesses for:
Pulmonary edema
Pulmonary congestion
Left atrial enlargement
Left ventricular enlargement (chronic MR)
5. Laboratory Tests
Troponin (to rule out myocardial infarction)
BNP
Blood cultures if infective endocarditis is suspected
6. Additional Tests (when indicated)
Cardiac MRI
Stress echocardiography
Coronary angiography (especially if ischemic MR is suspected or before surgery)
Diagnosis
Mitral Regurgitation · Diagnostic Criteria
| Parameter | Mild | Moderate | Severe |
|---|---|---|---|
| Regurgitant Volume (RVol) | <30 mL | 30–59 mL | ≥60 mL |
| Regurgitant Fraction (RF) | <30% | 30–49% | ≥50% |
| Effective Regurgitant Orifice Area (EROA) | <0.20 cm² | 0.20–0.39 cm² | ≥0.40 cm² |
| Vena Contracta Width (VCW) | <0.3 cm | 0.3–0.69 cm | ≥0.7 cm |
Management
1. Acute MR (Medical Emergency)
Urgent cardiology and cardiothoracic surgery consultation
Urgent mitral valve repair or valve replacement (for acute primary MR)
Stabilize the patient while awaiting surgery:
Diuretics (for pulmonary edema)
Vasodilators (e.g., nitrates, nitroprusside) to reduce afterload
Inotropes/vasopressors if cardiogenic shock develops
If secondary MR, treat the underlying cause (e.g., revascularization for ischemic MR).
2. Chronic MR
Medical Management
Treat the underlying cause.
Manage heart failure with:
Diuretics
ACE inhibitors
Beta-blockers
Manage associated atrial fibrillation if present.
-Definitive Treatment
Mitral valve repair is the preferred treatment.
Mitral valve replacement if repair is not possible.
Transcatheter mitral valve repair (e.g., clip device) may be considered in selected patients who are not suitable for surgery.
Complications
- Heart failure
- Pulmonary edema
- Cardiogenic shock (especially acute MR)
- Atrial fibrillation
- Increased risk of stroke and other thromboembolic events
- Pulmonary hypertension
- Infective endocarditis
Prognosis
- Acute MR has a poor prognosis if not treated urgently.
- Chronic MR may remain compensated for years but gradually progresses to left ventricular dysfunction and heart failure.
- Early diagnosis and timely valve repair improve long-term outcomes.
- Prognosis depends on the cause, severity, and timing of intervention.
Key Points / Clinical Pearls
- MR = blood leaks from the LV back into the LA during systole.
- Gold-standard investigation: Transthoracic echocardiography (TTE).
- Classic murmur: Holosystolic (pansystolic) murmur at the apex radiating to the left axilla.
- Acute MR is a medical and surgical emergency.
- Mitral valve repair is preferred over replacement when feasible.
- Common complications: heart failure, atrial fibrillation, pulmonary edema, pulmonary hypertension, and cardiogenic shock.
- National Center for Biotechnology Information (NIH). Mitral Regurgitation, StatPearls.
- Otto CM, Nishimura RA, Bonow RO, et al. 2020 ACC/AHA Guideline for the Management of Patients With Valvular Heart Disease. Circulation. 2021;143:e72-e227. PMID: 33972115.
- MedlinePlus, National Library of Medicine (NIH). Mitral Regurgitation: Medical Encyclopedia.
- Highlights From the 2020 ACC/AHA Guidelines on Valvular Heart Disease: Review of 2020 AHA/ACC VHD Guidelines. PMC9707478.
- National Center for Biotechnology Information (NIH). Mitral Valve Repair, StatPearls.