

Clinical Subject Page
Nephrotic Syndrome
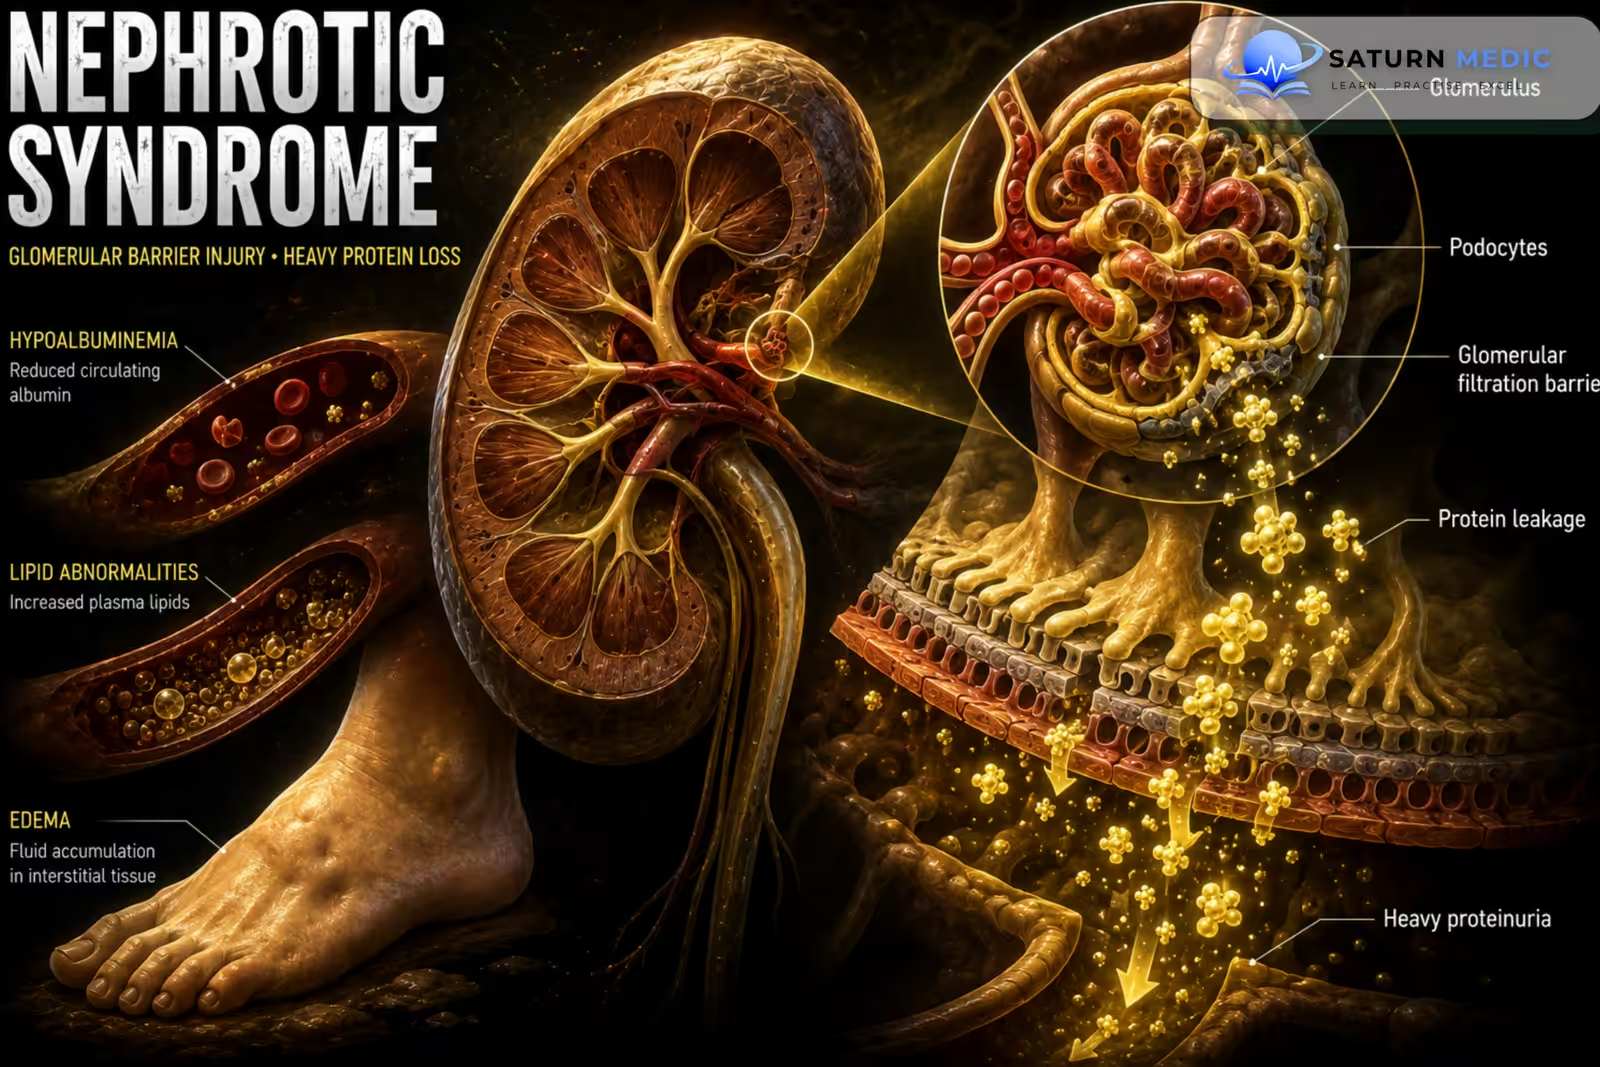
Nephrotic Syndrome is a clinical syndrome caused by increased glomerular permeability to proteins, resulting in heavy proteinuria, hypoalbuminemia, edema, and hyperlipidemia
Also called
ICD-10
Specialty
Onset
Reviewed
On This Page
-
OverviewOverview
-
Etiology & Risk FactorsEtiology & Risk Factors
-
PathophysiologyPathophysiology
-
Clinical PresentationClinical Presentation
-
History TakingHistory Taking
-
Physical ExaminationPhysical Examination
-
InvestigationsInvestigations
-
DiagnosisDiagnosis
-
ManagementManagement
-
ComplicationsComplications
-
PrognosisPrognosis
-
Key Points / Clinical PearlsKey Points / Clinical Pearls
Overview
–Nephrotic Syndrome is characterized by:
- Heavy proteinuria
- Hypoalbuminemia
- Generalized edema
- Hyperlipidemia
-It may be caused by a primary glomerular disease or secondary systemic disease.
-Common primary causes include:
-
-
- Minimal Change Disease
- Focal Segmental Glomerulosclerosis
- Membranous Nephropathy
-
Etiology & Risk Factors
-Etiology
–Primary Renal Causes
- Minimal Change Disease
- Focal Segmental Glomerulosclerosis
- Membranous Nephropathy
-Secondary Causes
- Diabetes Mellitus
- Systemic Lupus Erythematosus
- Amyloidosis
- Hepatitis B/C
- HIV
- Malignancy
- Drugs such as NSAIDs
-Risk Factors:
- Diabetes Mellitus
- Systemic Lupus Erythematosus
- Obesity
- Chronic infections
- Malignancy
- Nephrotoxic medications
Pathophysiology
-Glomerular injury → ↑ glomerular permeability → heavy urinary protein loss → ↓ serum albumin → ↓ plasma oncotic pressure → fluid shifts into tissues → edema
-Protein loss + hepatic compensation → ↑ hepatic lipoprotein production → hyperlipidemia
-Urinary loss of anticoagulant proteins → hypercoagulability → thrombosis
-Urinary loss of immunoglobulins → impaired immunity → increased infection risk
Clinical Presentation
-Symptoms:
- Periorbital edema
- Leg swelling
- Generalized edema
- Frothy urine
- Weight gain from fluid retention
- Fatigue
- Reduced urine output in severe cases
-Signs:
- Massive edema
- Ascites
- Pleural effusion
- Acute kidney injury
- Thromboembolism
- Severe infection
History Taking
-Ask about:
- Onset and progression of edema
- Frothy urine
- Reduced urine output
- Weight changes
- Diabetes
- Hypertension
- Autoimmune disease
- Recent infections
- Hepatitis or HIV risk
- Malignancy symptoms
- Medication use, especially NSAIDs
- Thrombotic symptoms
Physical Examination
-General Examination
- Blood pressure
- Weight
- Degree of edema
- Hydration status
-Look for:
- Periorbital edema
- Peripheral edema
- Ascites
- Pleural effusion
-System-Specific Examination:
- Signs of systemic autoimmune disease
- Diabetic complications
- Infection
- Deep vein thrombosis
- Pulmonary embolism
Investigations
-Urine Testing
-
Urinalysis
-
Urine protein measurement
-
Urine protein-to-creatinine ratio (UPCR) or albumin-to-creatinine ratio
-Blood Tests
-
Serum albumin
-
Serum creatinine
-
Urea
-
Electrolytes
-
Lipid profile
-Evaluation for Secondary Causes
Depending on clinical suspicion:
-
HbA1c/glucose
-
ANA and complement
-
Hepatitis B and C testing
-
HIV testing
-
Serum protein electrophoresis/immunofixation
-
Serum free light chains
-
Other autoimmune or infectious tests when indicated
-Imaging
Renal Ultrasound
May be performed to:
-
Assess kidney size and structure
-
Exclude obstruction
-
Support evaluation of underlying renal disease
-Special / Confirmatory Tests
Kidney Biopsy
Used when the underlying cause cannot be established clinically or when histological diagnosis will change management.
Diagnosis
-Diagnosis of Nephrotic Syndrome is established by:
Heavy proteinuria + hypoalbuminemia + edema ± hyperlipidemia → nephrotic syndrome
-Then determine the underlying cause using:
Clinical assessment → targeted blood/urine tests → kidney biopsy when indicated
Management
1. First-Line / Emergency Management
Urgent treatment is required for complications such as:
-
Severe edema with respiratory compromise
-
Acute Kidney Injury
-
Severe infection
-
Thrombosis
Treat the specific complication while addressing the underlying renal disease.
2. Definitive Treatment
Treat the underlying cause.
Examples:
-
Immunosuppressive therapy for selected primary glomerular diseases
-
Glycemic control in diabetic kidney disease
-
Treatment of autoimmune disease
-
Treatment of underlying infection or malignancy
-
Withdrawal of causative drugs
3. Medical Treatment
-ACE Inhibitors / ARBs
Used to:
-
Reduce proteinuria
-
Control blood pressure
-Diuretics
Loop diuretics are commonly used to control clinically significant edema.
-Statins
Used when indicated for persistent dyslipidemia and cardiovascular risk rather than routinely for every patient solely because nephrotic syndrome is present.
-Anticoagulation
Considered in selected patients at high risk of thrombosis, particularly with severe hypoalbuminemia and high-risk underlying diseases.
-Immunosuppressive Therapy
Used according to the underlying glomerular disease, such as:
-
Corticosteroids
-
Calcineurin inhibitors
Complications
- Acute kidney injury
- Chronic kidney disease
- Venous thromboembolism
- Renal vein thrombosis
- Pulmonary embolism
- Severe edema
- Pleural effusion
- Ascites
- Infections
- Malnutrition/protein wasting
Prognosis
-Prognosis depends mainly on the underlying cause, degree of proteinuria, renal function, and response to treatment.
-Some causes, such as Minimal Change Disease, have an excellent response to treatment, while others may progress to chronic kidney disease or kidney failure.
Key Points / Clinical Pearls
- Nephrotic Syndrome is characterized by heavy proteinuria, hypoalbuminemia, and edema.
- Hyperlipidemia is a common associated finding.
- Major primary causes include Minimal Change Disease, FSGS, and Membranous Nephropathy.
- Common secondary causes include Diabetes Mellitus, SLE, and amyloidosis.
- Glomerular injury causes increased protein permeability.
- Heavy urinary protein loss causes hypoalbuminemia and reduced plasma oncotic pressure.
- Reduced oncotic pressure leads to fluid movement into tissues → edema.
- Urinary loss of anticoagulant proteins increases the risk of thrombosis.
- Urinary loss of immunoglobulins increases susceptibility to infection.
- Urine protein quantification and serum albumin are key initial investigations.
- Renal function should be assessed with serum creatinine and eGFR.
- Kidney Disease: Improving Global Outcomes (KDIGO) Glomerular Diseases Work Group. KDIGO 2021 Clinical Practice Guideline for the Management of Glomerular Diseases. Kidney Int. 2021;100(4S):S1-S276. KDIGO .
- Kodner C. Nephrotic Syndrome in Adults: Diagnosis and Management. Am Fam Physician. 2016;93(6):479-485. American Family Physician .
- Hull RP, Goldsmith DJA. Nephrotic Syndrome in Adults. BMJ. 2008;336(7654):1185-1189. BMJ .
- Ronco P, Debiec H. Molecular Pathogenesis of Membranous Nephropathy: Recent Advances. Sci Rep. 2020;10:1441.
- National Institute of Diabetes and Digestive and Kidney Diseases (NIDDK). Nephrotic Syndrome in Adults . National Institutes of Health.
- National Library of Medicine (NIH). Nephrotic Syndrome . StatPearls.