
ICD-10
Specialty
Onset
Reviewed
-
OverviewOverview
-
Etiology & Risk FactorsEtiology & Risk Factors
-
PathophysiologyPathophysiology
-
Clinical PresentationClinical Presentation
-
History TakingHistory Taking
-
Physical ExaminationPhysical Examination
-
InvestigationsInvestigations
-
DiagnosisDiagnosis
-
ManagementManagement
-
ComplicationsComplications
-
PrognosisPrognosis
-
Key Points / Clinical PearlsKey Points / Clinical Pearls
What is Thoracic Aortic Aneurysm (TAA)?
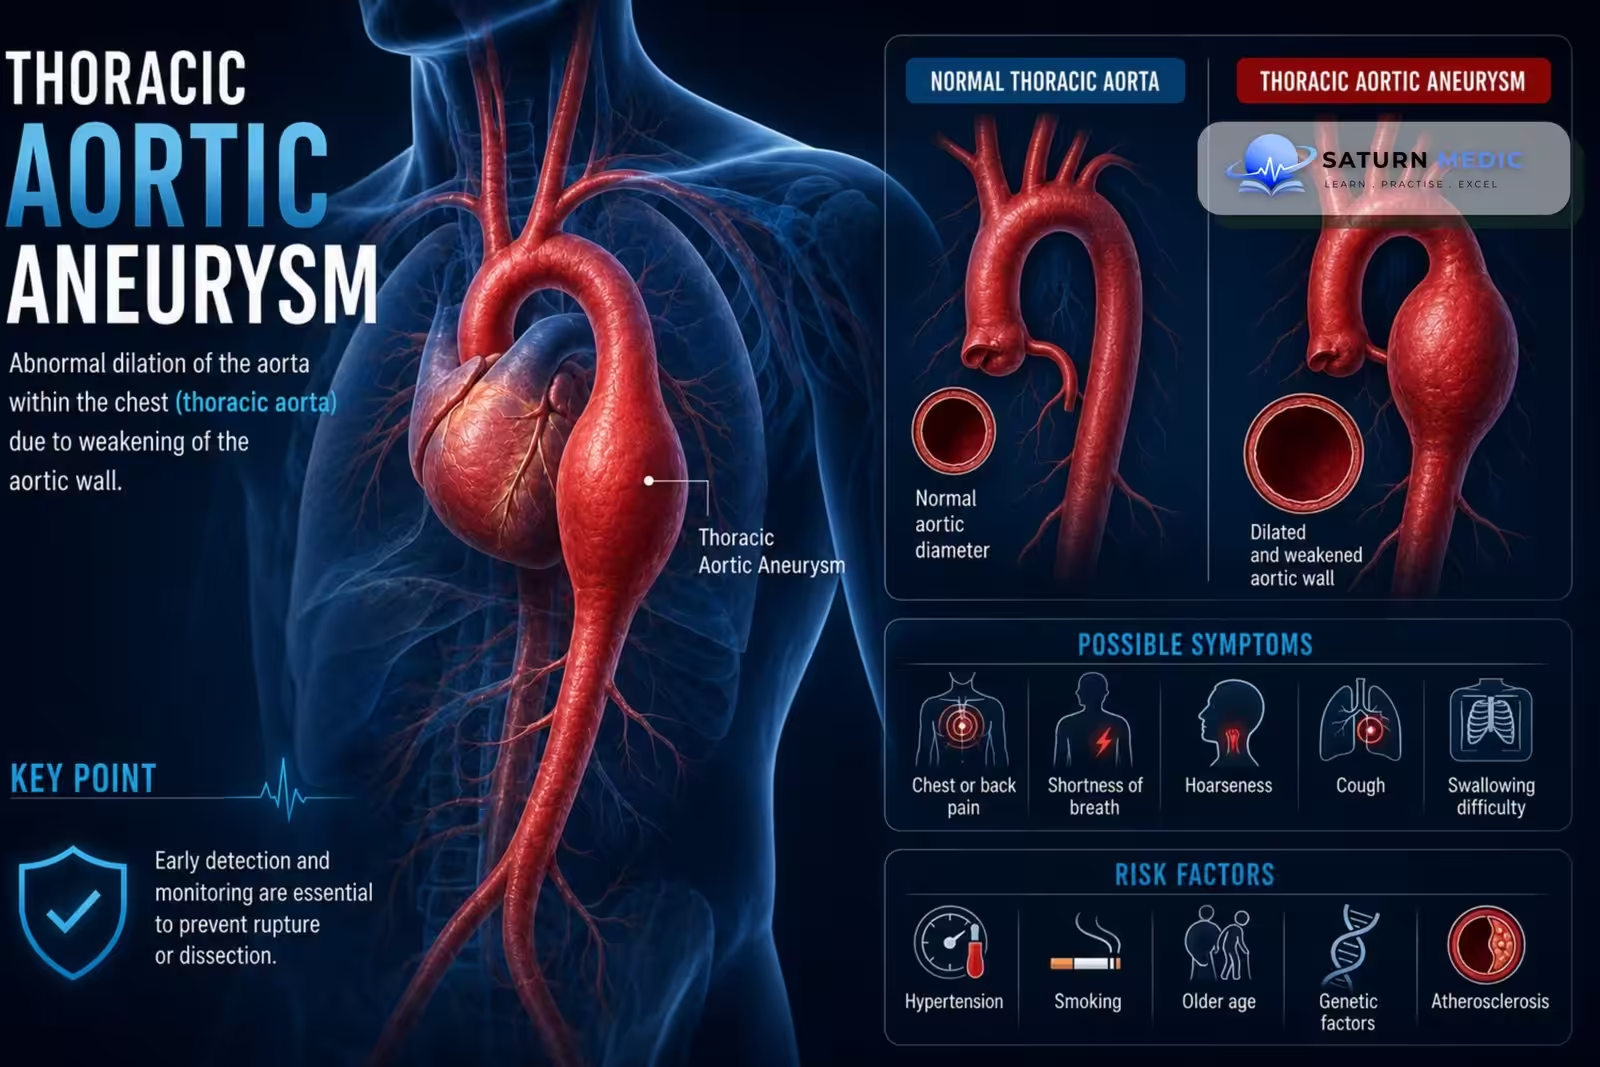
Thoracic aortic aneurysm (TAA) is a localized dilation of the thoracic aorta ≥50% above its normal diameter, resulting from weakening of the aortic wall and increasing the risk of dissection or rupture.
Etiology & Risk Factors
Etiology for Thoracic Aortic Aneurysm (TAA)
Degenerative (most common)
Chronic hypertension
Atherosclerosis
Bicuspid aortic valve
Marfan syndrome
Loeys-Dietz syndrome
Ehlers-Danlos syndrome
Aortitis (Takayasu, Giant cell arteritis)
Previous aortic dissection
Trauma
Risk Factors for Thoracic Aortic Aneurysm (TAA)
Older age
Male sex
Hypertension
Smoking
Family history
Connective tissue disorders
Hyperlipidemia
Bicuspid aortic valve
Pathophysiology
- Ascending Thoracic Aortic Aneurysm (TAA) is most often caused by cystic medial necrosis.
- Descending Thoracic Aortic Aneurysm (TAA) is typically caused by atherosclerosis.
- Inflammation and proteolytic degeneration of connective tissue proteins (collagen and elastin) and/or smooth muscle cells weaken the aortic wall.
- Loss of structural integrity causes progressive dilation (aneurysm formation).
- High blood pressure increases mechanical stress on the weakened wall, increasing the risk of aneurysm enlargement and rupture.
- The dilated aorta causes turbulent blood flow, which may produce a bruit.
- Thrombus may form within the aneurysm and embolize to peripheral arteries.
Simple Flow
Wall degeneration → Weak aortic wall → Aortic dilation → Turbulent flow → Thrombus formation ± Rupture
Clinical Presentation
Symptoms
Usually asymptomatic
Chest pain
Back pain
Hoarseness
Dysphagia
Dyspnea
Cough
Signs
Early diastolic murmur (aortic regurgitation)
Features of connective tissue disorders
Signs of compression of adjacent structures
Hypotension or shock (rupture)
History Taking
Key Questions
Chest or back pain?
Hoarseness or difficulty swallowing?
Shortness of breath?
Previous aneurysm or dissection?
History of hypertension?
Family history of aortic disease?
Marfan or other connective tissue disorders?
Smoking history?
Red Flags
Sudden severe chest or back pain
Syncope
Hypotension
Neurological deficits
Signs of rupture
Physical Examination
Inspection
May appear normal
Look for signs of respiratory distress if rupture occurs
Palpation
Usually no palpable mass
Auscultation
Assess heart sounds
May detect associated murmurs if there is underlying aortic valve disease
Look for Signs of Mediastinal Compression
Hoarseness
Stridor or wheeze
Signs of superior vena cava (SVC) syndrome
Dysphagia
If Rupture of Thoracic Aortic Aneurysm (TAA) Occurs
Hypotension
Signs of shock
Beck triad if cardiac tamponade develops (hypotension, muffled heart sounds, raised JVP)
Investigations
Laboratory
CBC
Renal function
Cardiac biomarkers (if chest pain)
Inflammatory markers (if aortitis suspected)
ECG
Usually normal
May show LVH or ischemic changes
Imaging
CT angiography (gold standard)
MR angiography
Transthoracic echocardiography (aortic root/ascending aorta)
Transesophageal echocardiography (unstable patients)
Chest X-ray
Widened mediastinum
Enlarged aortic silhouette
Diagnosis
Thoracic Aortic Aneurysm (TAA) · Diagnostic Criteria
| Segment | Normal Diameter | Aneurysm Threshold |
|---|---|---|
| Aortic Root / Sinuses of Valsalva | ~3.0–3.7 cm | ≥4.0–4.5 cm (varies by body size/guideline) |
| Ascending Aorta | ~2.9–3.5 cm | ≥4.0 cm (dilated); ≥5.5 cm = surgical threshold |
| Aortic Arch | ~2.5–3.0 cm | ≥4.0 cm |
| Descending Thoracic Aorta | ~2.4–3.0 cm | ≥3.5 cm (dilated); ≥6.0 cm = surgical threshold |
| Surgery threshold — Marfan/connective tissue disease | ≥4.5–5.0 cm ascending/root (lower threshold than general population due to higher rupture/dissection risk at smaller size) | |
| Surgery threshold — Bicuspid aortic valve | ≥5.0 cm (or ≥4.5 cm with risk factors: rapid growth, family history, coarctation) | |
Management
General Measures for Thoracic Aortic Aneurysm (TAA)
Sodium restriction
Fluid restriction (if congested)
Treat the underlying cause
Medications
Loop diuretics (symptom relief)
Mineralocorticoid receptor antagonists (selected patients)
Anticoagulation for atrial fibrillation
Disease-specific therapy (e.g., tafamidis for ATTR amyloidosis, chemotherapy for AL amyloidosis)
Advanced Therapy
Pacemaker (if conduction disease)
Heart transplantation (selected patients)
Complications
- Permanent valvular heart disease (especially mitral valve, followed by the aortic valve)
- Heart failure
- Atrial fibrillation
- Infective endocarditis
- Progressive worsening of valve disease, which may require valvuloplasty or heart valve replacement
- Recurrent acute rheumatic fever, leading to further valve damage if long-term antibiotic prophylaxis is not maintained
Prognosis
- Small, stable, asymptomatic TAA → generally favorable prognosis with surveillance.
- Large or rapidly enlarging TAA → increased risk of rupture/dissection.
- Symptomatic TAA → higher risk and usually requires urgent specialist assessment.
- Ruptured or dissected TAA → very high mortality and requires emergency treatment.
- Prognosis is also affected by Marfan syndrome, bicuspid aortic valve, other genetic aortopathies, hypertension, smoking, and comorbid disease.
Key Points / Clinical Pearls
- Thoracic Aortic Aneurysm (TAA) is a permanent dilation of the thoracic aorta.
- Most TAAs are asymptomatic and are discovered incidentally on imaging.
- Hypertension is the most important modifiable risk factor.
- Connective tissue disorders (e.g., Marfan syndrome, Loeys-Dietz syndrome) increase the risk of early TAA.
- Ascending aortic aneurysms are commonly associated with bicuspid aortic valve and genetic disorders.
- CT angiography and MRI are the preferred imaging modalities for diagnosis and surveillance.
- Regular imaging follow-up is essential to monitor aneurysm size and growth.
- Rapid aneurysm growth increases the risk of rupture and dissection.
- Acute chest or back pain in a patient with TAA should raise suspicion for acute aortic dissection.
- Blood pressure control and timely surgical repair for large or rapidly expanding aneurysms reduce the risk of rupture and improve survival.
- Faiza Z, Sharman T. National Center for Biotechnology Information (NIH). Thoracic Aorta Aneurysm, StatPearls.
- Isselbacher EM, Preventza O, Hamilton Black J 3rd, et al. 2022 ACC/AHA Guideline for the Diagnosis and Management of Aortic Disease. Circulation. 2022;146:e334-e482. PMID: 36334952.
- Loeys BL, Dietz HC, Braverman AC, et al. The Revised Ghent Nosology for the Marfan Syndrome. J Med Genet. 2010;47:476-485. PMID: 20591885.
- MedlinePlus, National Library of Medicine (NIH). Thoracic Aortic Aneurysm: Medical Encyclopedia.
- Sethi S, Parekh U. National Center for Biotechnology Information (NIH). Aortic Arch Aneurysm, StatPearls.
Practice Thoracic Aortic Aneurysm (TAA) questions
Lock in what you just read with exam-style MCQs and active-recall flashcards from Saturn Medic.