
Also called
ICD-10
Specialty
Onset
Reviewed
-
OverviewOverview
-
Etiology & Risk FactorsEtiology & Risk Factors
-
PathophysiologyPathophysiology
-
Clinical PresentationClinical Presentation
-
History TakingHistory Taking
-
Physical ExaminationPhysical Examination
-
InvestigationsInvestigations
-
DiagnosisDiagnosis
-
ManagementManagement
-
ComplicationsComplications
-
PrognosisPrognosis
-
Key Points / Clinical PearlsKey Points / Clinical Pearls
What is Hypothyroidism?
–Hypothyroidism occurs when the body does not produce enough thyroid hormones (T3 and T4).
-These hormones regulate metabolism, growth, and energy use.
–The most common cause is Hashimoto’s Thyroiditis, an autoimmune destruction of the thyroid gland.
-Patients commonly present with fatigue, weight gain, cold intolerance, constipation, and slowed body functions.
Etiology & Risk Factors
-Hypothyroidism can occur due to problems at different levels of the hypothalamic-pituitary-thyroid axis.
-Primary Hypothyroidism (most common):
Caused by thyroid gland failure:
• Hashimoto’s Thyroiditis
• Iodine deficiency
• Thyroid surgery
• Radioactive iodine therapy
• Thyroid gland destruction from autoimmune disease
-Secondary Hypothyroidism:
Caused by pituitary gland failure:
• Pituitary surgery
• Radiation therapy
• Sheehan syndrome
–
Tertiary Hypothyroidism:
Caused by hypothalamic dysfunction:
• Hypothalamic tumors
• Inflammatory or infiltrative disorders
-Risk Factors
• Female sex
• Increasing age
• Family history of thyroid disease
• Autoimmune diseases
• Previous thyroid surgery
• Previous radioactive iodine treatment
• Neck radiation exposure
• Iodine deficiency or excess
Pathophysiology
Thyroid gland dysfunction or reduced thyroid stimulation → ↓ Thyroid hormone synthesis (↓ T3 and ↓ T4) → Reduced negative feedback to pituitary gland
→ ↑ TSH secretion (in primary hypothyroidism)
→ Reduced metabolic activity in tissues
→ ↓ Oxygen consumption and energy production
→ Slowed physiological processes → Fatigue + weight gain + cold intolerance + constipation + bradycardia
-Severe untreated hypothyroidism
→ Progressive metabolic slowing
→ Multisystem dysfunction
→ Myxedema coma
Clinical Presentation
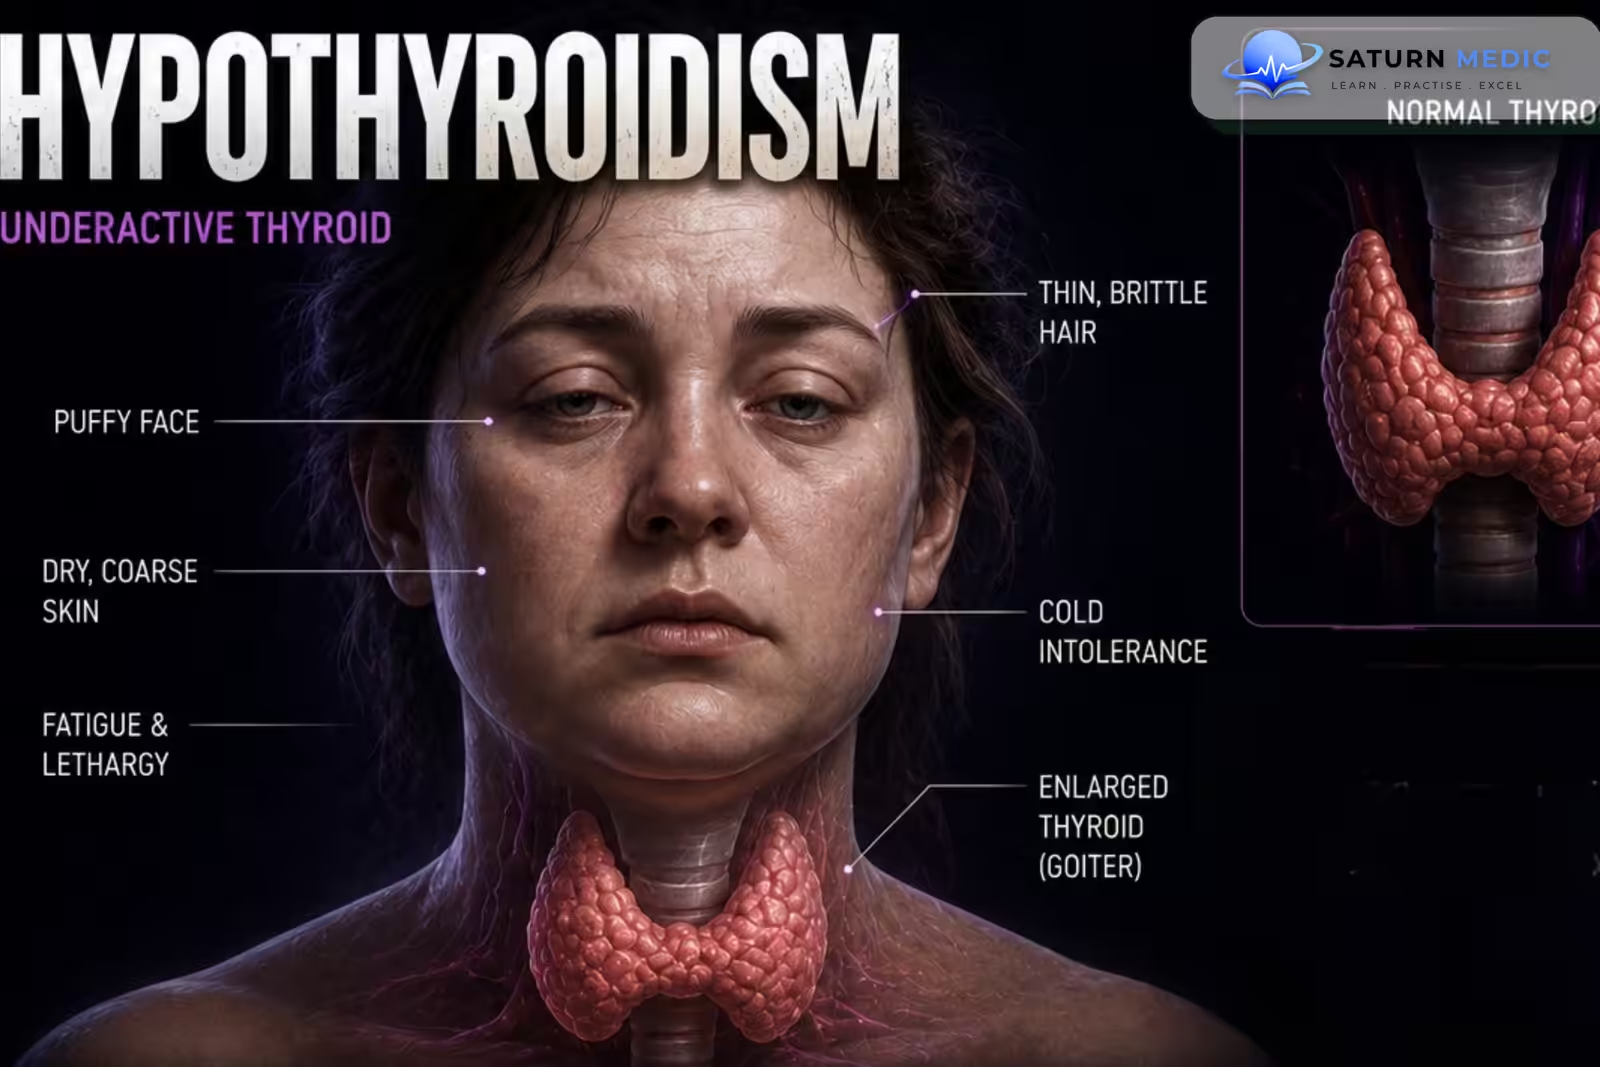
-Symptoms:
• Fatigue
• Weight gain
• Cold intolerance
• Constipation
• Dry skin
• Hair loss
• Muscle aches
• Muscle weakness
-Signs:
• Bradycardia
• Dry, coarse skin
• Brittle hair
• Facial puffiness
• Periorbital edema
• Non-pitting edema
• Delayed relaxation of deep tendon reflexes
• Slow speech
History Taking
-Ask about:
• Fatigue and reduced energy
• Weight gain
• Cold intolerance
• Constipation
• Dry skin
• Hair loss
• Voice changes
• Menstrual changes
• Fertility problems
• Mood changes
• Memory problems
Physical Examination
-General Examination
• Assess weight and BMI
• Measure heart rate and blood pressure
• Measure temperature
• Assess mental status
• Look for facial puffiness
• Assess skin and hair changes
• Check for peripheral edema
-System-Specific Examination:
-Thyroid Examination:
• Inspect for goiter
• Palpate thyroid gland
• Assess thyroid size and consistency
• Look for nodules
Investigations
-Biochemistry / Specific Tests
-Thyroid Stimulating Hormone (TSH):
Most important initial test.
-Findings:
• ↑ TSH in primary hypothyroidism
• Normal or low TSH in central hypothyroidism
-Free Thyroxine (Free T4)
Findings:
• ↓ Free T4 in overt hypothyroidism
-Thyroid Antibodies
Used when autoimmune thyroid disease is suspected:
• Thyroid peroxidase antibodies (TPO antibodies)
• Thyroglobulin antibodies
-Lipid Profile
May show:
• Increased LDL cholesterol
• Increased total cholesterol
-Electrolytes
Possible findings:
• Hyponatremia in severe hypothyroidism
-Imaging
Thyroid Ultrasound:
Not routinely required for diagnosis.
Diagnosis
-Hypothyroidism is diagnosed by demonstrating reduced thyroid hormone activity:
-Primary Hypothyroidism:
• Increased TSH
• Decreased free T4
-Subclinical Hypothyroidism:
• Increased TSH
• Normal free T4
-Central Hypothyroidism:
• Low free T4
• Low or inappropriately normal TSH
Management
1. First-Line / Emergency Management
Stable Hypothyroidism
-
Confirm diagnosis.
-
Start levothyroxine when indicated.
Myxedema Coma
-
Intravenous thyroid hormone
-
Intravenous corticosteroids until adrenal insufficiency is excluded
-
Supportive care and careful warming
-
Correct metabolic abnormalities
-
Treat the precipitating cause
2. Definitive Treatment
-
Levothyroxine (T4) replacement: definitive treatment for hypothyroidism.
3. Medical Treatment
-
Levothyroxine: first-line treatment, usually once daily.
-
Adjust dose according to TSH and clinical response.
-
Use lower starting doses in elderly patients or those with cardiovascular disease.
-
Increase dose requirements during pregnancy.
4. Surgical / Procedural Treatment
Not routinely required.
-
Treat the underlying cause when appropriate, such as pituitary disease in central hypothyroidism.
5. Supportive Management
-
Regular TSH monitoring
-
Patient education regarding lifelong treatme
Complications
• Myxedema coma
• Severe hypothermia
• Respiratory failure
• Cardiovascular instability
• Hyperlipidemia
• Atherosclerotic cardiovascular disease
• Heart failure
• Infertility
• Menstrual abnormalities
• Peripheral neuropathy
Prognosis
-The prognosis of hypothyroidism is excellent with appropriate treatment.
–Most patients achieve normal thyroid function with correct levothyroxine dosing.
-Outcome depends on:
• Early diagnosis
• Treatment adherence
• Regular monitoring
Key Points / Clinical Pearls
• Hypothyroidism is caused by insufficient thyroid hormone production.
• The most common cause is Hashimoto’s Thyroiditis.
• Primary hypothyroidism causes ↑ TSH and ↓ free T4.
• Symptoms develop gradually and may be nonspecific.
• Common symptoms include fatigue, weight gain, cold intolerance, and constipation.
• Bradycardia and delayed reflex relaxation are classic signs.
• Thyroid antibodies help identify autoimmune causes.
• Levothyroxine is the standard treatment.
• Treatment is usually lifelong in permanent thyroid failure.
• TSH is used to monitor treatment in primary hypothyroidism.
• Severe untreated disease can cause myxedema coma.
• Pregnancy increases thyroid hormone requirements.
- Jonklaas J, Bianco AC, Bauer AJ, et al. Guidelines for the Treatment of Hypothyroidism: Prepared by the American Thyroid Association Task Force on Thyroid Hormone Replacement. Thyroid. 2014;24(12):1670-1751. Thyroid .
- Garber JR, Cobin RH, Gharib H, et al. Clinical Practice Guidelines for Hypothyroidism in Adults: Cosponsored by the American Association of Clinical Endocrinologists and the American Thyroid Association. Endocr Pract. 2012;18(6):988-1028. Endocrine Practice .
- Chaker L, Bianco AC, Jonklaas J, Peeters RP. Hypothyroidism. Lancet. 2017;390(10101):1550-1562. The Lancet .
- Taylor PN, Albrecht D, Scholz A, et al. Global Epidemiology of Hyperthyroidism and Hypothyroidism. Nat Rev Endocrinol. 2018;14(5):301-316. Nature Reviews Endocrinology .
- National Institute of Diabetes and Digestive and Kidney Diseases (NIDDK). Hypothyroidism . National Institutes of Health.
- National Library of Medicine (NIH). Hypothyroidism . StatPearls.
Practice Hypothyroidism questions
Lock in what you just read with exam-style MCQs and active-recall flashcards from Saturn Medic.