

Clinical Subject Page
Diabetic Nephropathy
Diabetic Nephropathy is kidney damage caused by long-standing diabetes mellitus. It is characterized by persistent albuminuria and/or declining kidney function and is a major cause of Chronic Kidney Disease (CKD) and kidney failure
Also called
ICD-10
Specialty
Onset
Reviewed
-
OverviewOverview
-
Etiology & Risk FactorsEtiology & Risk Factors
-
PathophysiologyPathophysiology
-
Clinical PresentationClinical Presentation
-
History TakingHistory Taking
-
Physical ExaminationPhysical Examination
-
InvestigationsInvestigations
-
DiagnosisDiagnosis
-
ManagementManagement
-
ComplicationsComplications
-
PrognosisPrognosis
-
Key Points / Clinical PearlsKey Points / Clinical Pearls
Overview
-Diabetic Nephropathy develops as chronic hyperglycemia causes glomerular and renal vascular injury.
-Important features include:
- Albuminuria
- Progressive decline in eGFR
- Hypertension
- Progressive Chronic Kidney Disease (CKD)
-It may eventually progress to kidney failure.
Etiology & Risk Factors
-Etiology:
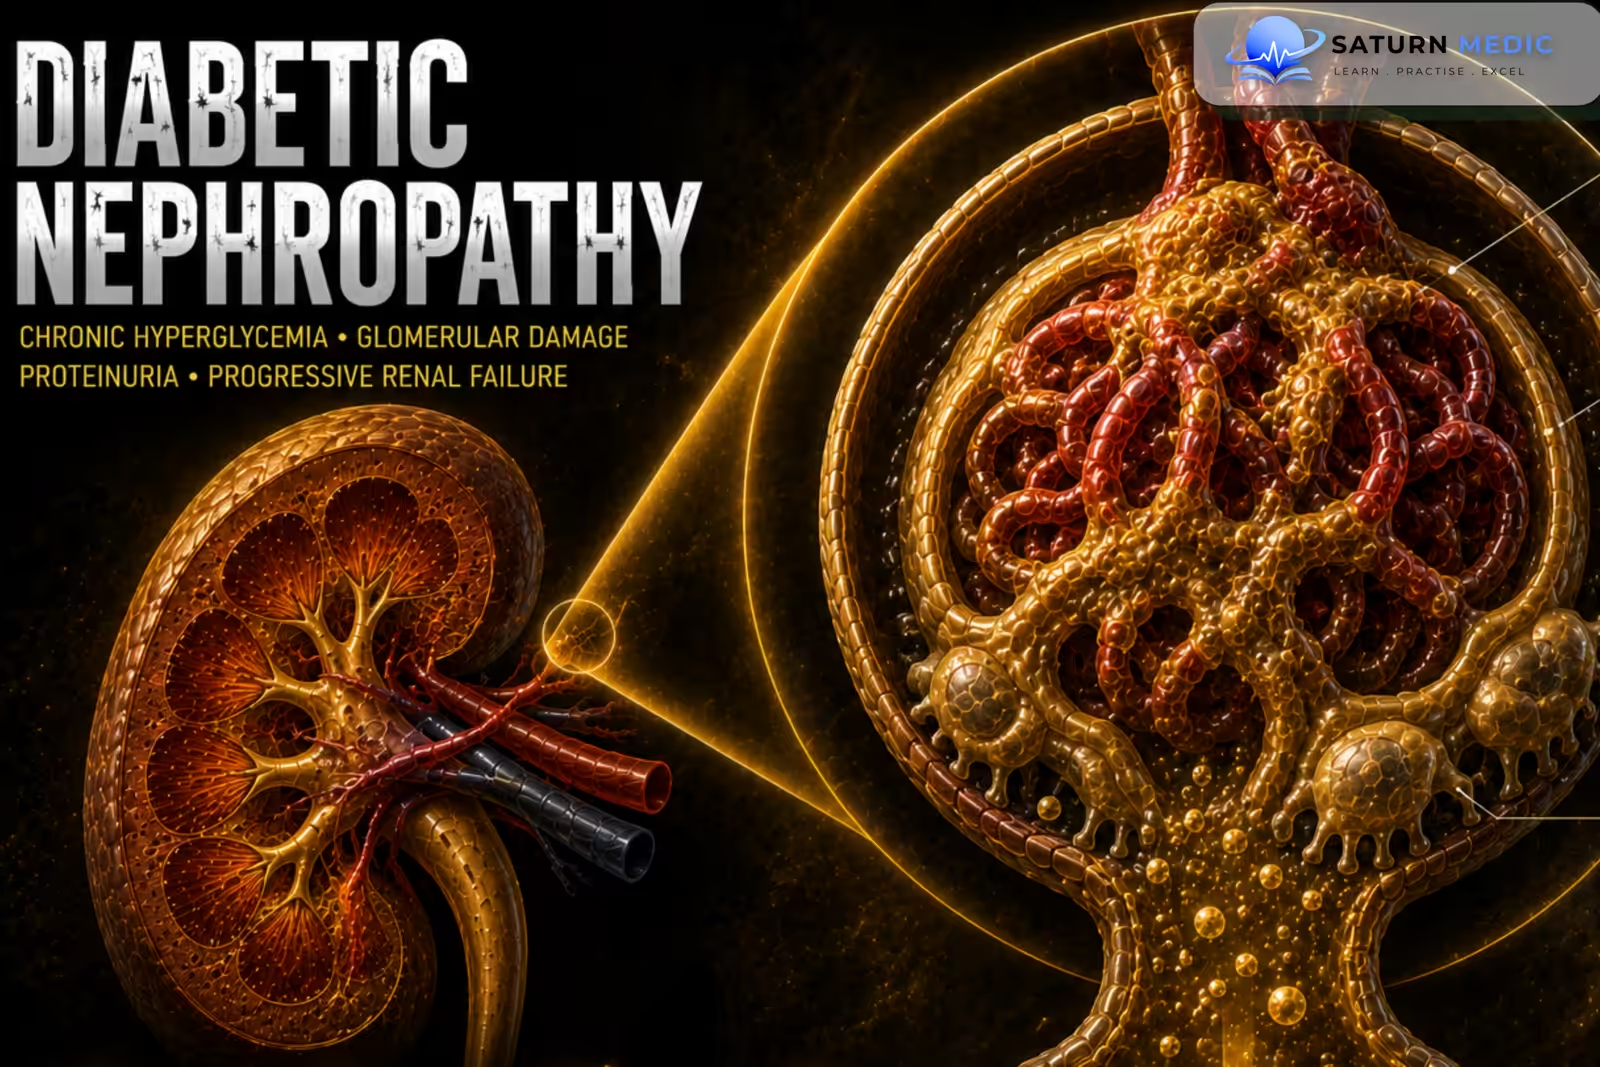
Persistent hyperglycemia causes glomerular hyperfiltration, endothelial injury, basement membrane thickening, mesangial expansion, and progressive glomerulosclerosis.
-Risk Factors:
- Long duration of diabetes
- Poor glycemic control
- Hypertension
- Smoking
- Obesity
- Established diabetic retinopathy
Pathophysiology
Chronic hyperglycemia → glomerular hyperfiltration → endothelial and podocyte injury → glomerular basement membrane thickening → mesangial expansion → glomerulosclerosis → albuminuria → declining GFR → Chronic Kidney Disease (CKD) → kidney failure
Clinical Presentation
-Symptoms:
-
Early Diabetic Nephropathy is often asymptomatic.
Progressive disease may cause:
- Frothy urine
- Fatigue
- Peripheral edema
- Nocturia
- Reduced exercise tolerance
- Symptoms of advanced kidney disease
-Signs:
- Hypertension
- Peripheral edema
- Features of diabetic complications
- Signs of advanced Chronic Kidney Disease (CKD)
History Taking
-Ask about:
- Duration and type of diabetes
- Glycemic control
- Previous urine albumin results
- Blood pressure history
- Medication adherence
- Diabetic retinopathy and other microvascular complications
- Cardiovascular disease
- Smoking
- NSAID and nephrotoxic medication use
- Frothy urine and edema
- Previous acute kidney injury
Physical Examination
-General Examination
- Blood pressure
- Weight and body mass index
- Peripheral edema
- Volume status
-System-Specific Examination:
- Fundoscopy for diabetic retinopathy
- Cardiovascular examination
- Assessment for other diabetic complications
Investigations
-Biochemistry / Specific Tests
-
Urine albumin-to-creatinine ratio (ACR)
-
Serum creatinine and eGFR
-
Serum potassium
-
Serum bicarbonate
-
Urinalysis
-
HbA1c for glycemic control
Persistent albuminuria should be confirmed because transient elevations can occur with infection, exercise, hyperglycemia, or other acute conditions.
-Imaging
Renal ultrasound is not routinely required for typical diabetic kidney disease.
It is useful when another renal pathology is suspected or when there are atypical features.
-Special / Confirmatory Tests
Kidney biopsy is not routinely required.
It may be considered when features suggest another kidney disease, such as:
-
Active urinary sediment
-
Rapid unexplained decline in kidney function
-
Sudden heavy proteinuria
-
Absence of typical diabetic microvascular disease
Diagnosis
-Diagnosis of Diabetic Nephropathy is based on:
- Diabetes mellitus
- Persistent albuminuria and/or reduced eGFR
- Exclusion of alternative kidney disease when clinically indicated
Persistent albuminuria is generally confirmed with repeated testing over time.
Management
1. Definitive Treatment
The main goals are:
-
Optimize glycemic control
-
Control blood pressure
-
Reduce albuminuria
-
Slow progression of Chronic Kidney Disease (CKD)
-
Reduce cardiovascular risk
2. Medical Treatment
-
ACE inhibitors or ARBs — particularly for patients with hypertension and albuminuria
-
SGLT2 inhibitors — appropriate patients with type 2 diabetes and Chronic Kidney Disease (CKD), and selected patients with diabetic kidney disease
-
Finerenone — selected patients with type 2 diabetes, CKD, and persistent albuminuria despite optimized renin-angiotensin system blockade
-
Statins for cardiovascular risk reduction
-
GLP-1 receptor agonists may be appropriate for selected patients with type 2 diabetes and cardiovascular or metabolic indications
3. Surgical / Procedural Treatment
No routine surgical treatment.
Dialysis or kidney transplantation may be required if kidney failure develops.
4. Supportive Management
-
Blood pressure control
-
Glycemic control
-
Sodium restriction
-
Weight management
-
Smoking cessation
-
Avoid NSAIDs and other nephrotoxins
Complications
- Progressive albuminuria
- Nephrotic syndrome
- Hypertension
- Hyperkalemia
- Fluid overload
- Chronic Kidney Disease (CKD)
- Kidney failure
- Cardiovascular disease
- Anemia
- CKD-mineral and bone disorder
Prognosis
-The prognosis of Diabetic Nephropathy depends mainly on the degree of albuminuria, baseline eGFR, glycemic control, blood pressure control, and cardiovascular disease
–Early detection and appropriate kidney-protective therapy can significantly slow progression to kidney failure.
Key Points / Clinical Pearls
- Diabetic Nephropathy is kidney damage caused by diabetes.
- It is a major cause of Chronic Kidney Disease (CKD) and kidney failure.
- Persistent albuminuria is an important early marker.
- eGFR is essential for assessing kidney function and staging CKD.
- Long duration of diabetes increases risk.
- Poor glycemic control and hypertension accelerate progression.
- Diabetic retinopathy supports the diagnosis but is not required.
- Urine albumin-to-creatinine ratio (ACR) is a key investigation.
- Kidney biopsy is not routinely required.
- ACE inhibitors or ARBs are important in diabetic patients with hypertension and albuminuria.
- SGLT2 inhibitors provide important kidney-protective effects in appropriate patients.
- Finerenone may be used in selected patients with type 2 diabetes and albuminuric CKD.
- Cardiovascular risk reduction is an essential part of management.
- Progressive disease can lead to Chronic Kidney Disease (CKD) and kidney failure.
- Kidney Disease: Improving Global Outcomes (KDIGO) Diabetes Work Group. KDIGO 2022 Clinical Practice Guideline for Diabetes Management in Chronic Kidney Disease. Kidney Int. 2022;102(5S):S1-S127. KDIGO .
- American Diabetes Association Professional Practice Committee. Chronic Kidney Disease and Risk Management: Standards of Care in Diabetes—2026. Diabetes Care. 2026;49(Suppl 1). Diabetes Care .
- Alicic RZ, Rooney MT, Tuttle KR. Diabetic Kidney Disease: Challenges, Progress, and Possibilities. Clin J Am Soc Nephrol. 2017;12(12):2032-2045. Clinical Journal of the American Society of Nephrology .
- Tuttle KR, Bakris GL, Bilous RW, et al. Diabetic Kidney Disease: A Report From an ADA Consensus Conference. Diabetes Care. 2014;37(10):2864-2883. Diabetes Care .
- National Institute of Diabetes and Digestive and Kidney Diseases (NIDDK). Diabetic Kidney Disease . National Institutes of Health.
- National Kidney Foundation. Diabetic Kidney Disease .