

Clinical Subject Page
Focal Segmental Glomerulosclerosis (FSGS)
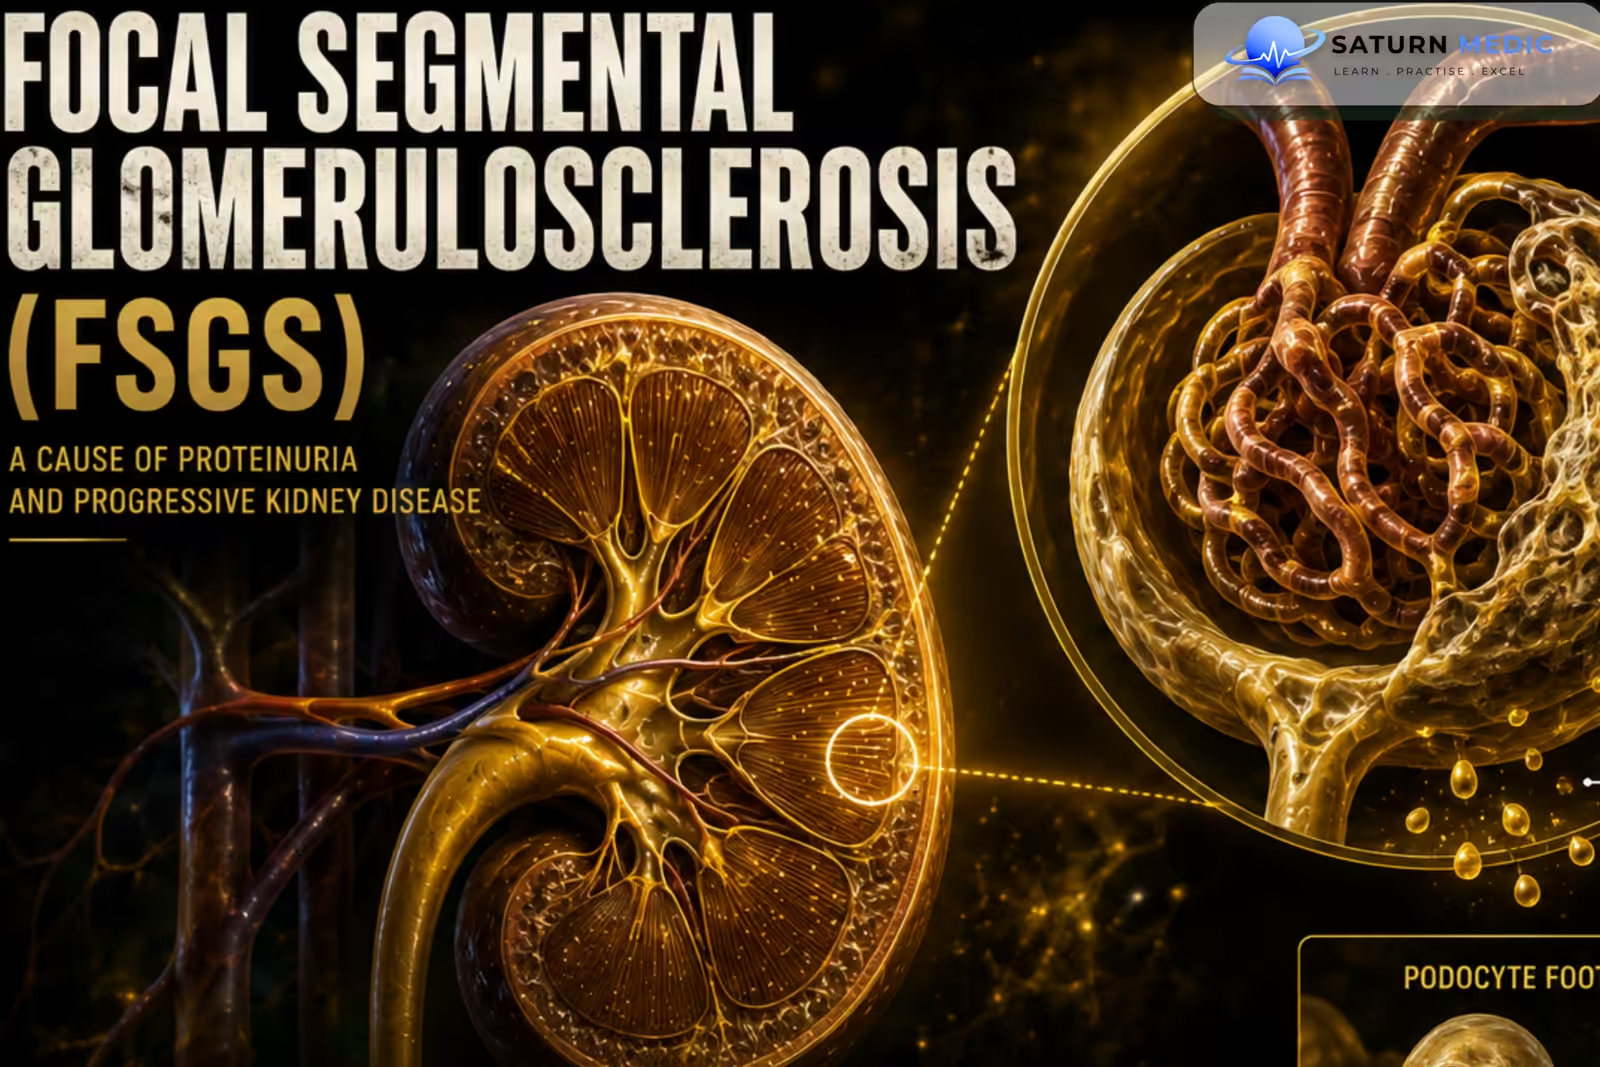
Focal Segmental Glomerulosclerosis (FSGS) is a pattern of kidney injury characterized by scarring in some (focal) glomeruli and only part (segmental) of the affected glomerulus. It is an important cause of nephrotic syndrome and progressive kidney dysfunction
Also called
ICD-10
Specialty
Onset
Reviewed
-
OverviewOverview
-
Etiology & Risk FactorsEtiology & Risk Factors
-
PathophysiologyPathophysiology
-
Clinical PresentationClinical Presentation
-
History TakingHistory Taking
-
Physical ExaminationPhysical Examination
-
InvestigationsInvestigations
-
DiagnosisDiagnosis
-
ManagementManagement
-
ComplicationsComplications
-
PrognosisPrognosis
-
Key Points / Clinical PearlsKey Points / Clinical Pearls
Overview
-Focal Segmental Glomerulosclerosis (FSGS) is a histopathological pattern of glomerular injury caused by damage to podocytes.
-It may be:
- Primary FSGS — usually due to a circulating permeability factor
- Secondary FSGS — due to adaptive, viral, drug-related, or other causes
- Genetic FSGS — caused by pathogenic variants affecting podocyte function
-It commonly presents with proteinuria and may cause nephrotic syndrome and progression to Chronic Kidney Disease (CKD).
Etiology & Risk Factors
–Focal Segmental Glomerulosclerosis (FSGS) results primarily from podocyte injury, leading to glomerular scarring.
-Major causes include:
- Primary podocyte injury
- Genetic podocyte disorders
- Adaptive hyperfiltration due to reduced nephron mass or obesity
- Viral infections, especially HIV
- Drug-associated injury
- Other secondary causes of glomerular stress
-Risk Factors
- Obesity
- Reduced nephron mass
- HIV infection
- Previous kidney injury
- Exposure to nephrotoxic drugs associated with FSGS
Pathophysiology
Podocyte injury or loss → disruption of the glomerular filtration barrier → proteinuria → persistent glomerular injury → segmental glomerular sclerosis → progressive nephron loss → declining GFR → Chronic Kidney Disease (CKD) or kidney failure
Clinical Presentation
-Symptoms:
- Frothy urine
- Peripheral edema
- Weight gain from fluid retention
- Fatigue
- Reduced urine output in severe disease
-Signs:
- Peripheral edema
- Hypertension
- Features of nephrotic syndrome
- Reduced kidney function in progressive disease
History Taking
-Ask about:
- Frothy urine and edema
- Duration and severity of proteinuria
- Hypertension
- Previous kidney disease
- Obesity or major weight gain
- HIV risk or known infection
- Medication and substance exposure
- Previous nephron loss or kidney surgery
- Family history of kidney disease
Physical Examination
-General Examination
- Blood pressure
- Peripheral or generalized edema
- Weight changes
-System-Specific Examination:
- Cardiovascular assessment for hypertension and fluid overload
- Abdominal examination for underlying kidney disease
- Assessment for features of systemic or secondary causes
Investigations
-Biochemistry / Specific Tests
-
Urinalysis
-
Urine protein-to-creatinine ratio or 24-hour urine protein
-
Serum creatinine and eGFR
-
Serum albumin
-
Lipid profile
-
Tests for secondary causes when indicated, including HIV testing
-Imaging
Renal ultrasound may assess kidney size and exclude structural abnormalities.
-Special / Confirmatory Tests
Kidney biopsy is the definitive investigation.
Typical findings include:
-
Focal involvement of glomeruli
-
Segmental glomerular sclerosis
-
Podocyte foot-process effacement on electron microscopy
Genetic testing may be indicated in selected patients, particularly with early-onset disease or a family history.
Diagnosis
-Diagnosis of Focal Segmental Glomerulosclerosis (FSGS) is based on:
- Significant proteinuria, often nephrotic-range
- Clinical assessment for nephrotic syndrome
- Assessment of kidney function
- Exclusion of secondary causes
- Kidney biopsy confirming focal and segmental glomerular sclerosis
The clinical context and additional investigations are then used to classify FSGS as primary, secondary, or genetic.
Management
1. First-Line / Emergency Management
There is no routine emergency treatment.
Urgent treatment may be required for severe edema, acute kidney injury, or other serious complications.
2. Definitive Treatment
Treatment depends on the underlying type:
-
Primary FSGS: immunosuppressive therapy may be indicated
-
Secondary FSGS: treat the underlying cause and reduce glomerular hyperfiltration
-
Genetic FSGS: supportive management; routine immunosuppression is generally not beneficial
3. Medical Treatment
-
ACE inhibitors or ARBs to reduce proteinuria and control blood pressure
-
Glucocorticoids for appropriate patients with primary FSGS
-
Calcineurin inhibitors in selected patients with steroid-resistant primary FSGS
-
Diuretics for edema
-
Lipid-lowering therapy when indicated
4. Surgical / Procedural Treatment
No routine surgical treatment.
Kidney replacement therapy may be required if kidney failure develops.
5. Supportive Management
-
Sodium restriction
-
Blood pressure control
-
Reduction of proteinuria
-
Weight management when appropriate
-
Treatment of the underlying cause
Complications
- Nephrotic syndrome
- Severe edema
- Hypoalbuminemia
- Hyperlipidemia
- Thromboembolism
- Acute kidney injury
- Chronic Kidney Disease (CKD)
- Kidney failure
Prognosis
-The prognosis varies according to the type of Focal Segmental Glomerulosclerosis (FSGS), degree of proteinuria, response to treatment, and baseline kidney function.
–Persistent nephrotic-range proteinuria and progressive loss of kidney function are associated with a poorer prognosis.
Key Points / Clinical Pearls
- Focal Segmental Glomerulosclerosis (FSGS) is a pattern of glomerular scarring caused primarily by podocyte injury.
- Focal means only some glomeruli are affected.
- Segmental means only part of an affected glomerulus is scarred.
- It is an important cause of nephrotic syndrome.
- Proteinuria is a major clinical finding.
- FSGS may be primary, secondary, or genetic.
- Kidney biopsy is required for confirmation.
- Primary FSGS may respond to glucocorticoids or other immunosuppressive therapy.
- Secondary FSGS should be treated by addressing the underlying cause.
- ACE inhibitors or ARBs help reduce proteinuria.
- Hypertension and persistent proteinuria accelerate kidney damage.
- FSGS can progress to Chronic Kidney Disease (CKD) and kidney failure.
- Kidney Disease: Improving Global Outcomes (KDIGO) Glomerular Diseases Work Group. KDIGO 2021 Clinical Practice Guideline for the Management of Glomerular Diseases. Kidney Int. 2021;100(4S):S1-S276. KDIGO .
- Rovin BH, Adler SG, Barratt J, et al. KDIGO 2021 Clinical Practice Guideline for the Management of Glomerular Diseases: Executive Summary. Kidney Int. 2021;100(4):753-779. Kidney International .
- D'Agati VD, Kaskel FJ, Falk RJ. Focal Segmental Glomerulosclerosis. N Engl J Med. 2011;365(25):2398-2411. New England Journal of Medicine .
- De Vriese AS, Sethi S, Nath KA, Glassock RJ, Fervenza FC. Differentiating Primary, Genetic, and Secondary FSGS in Adults: A Clinicopathologic Approach. J Am Soc Nephrol. 2018;29(3):759-774. Journal of the American Society of Nephrology .
- National Institute of Diabetes and Digestive and Kidney Diseases (NIDDK). Focal Segmental Glomerulosclerosis (FSGS) . National Institutes of Health.
- National Library of Medicine (NIH). Focal Segmental Glomerulosclerosis . StatPearls.