

Clinical Subject Page
Membranous Nephropathy
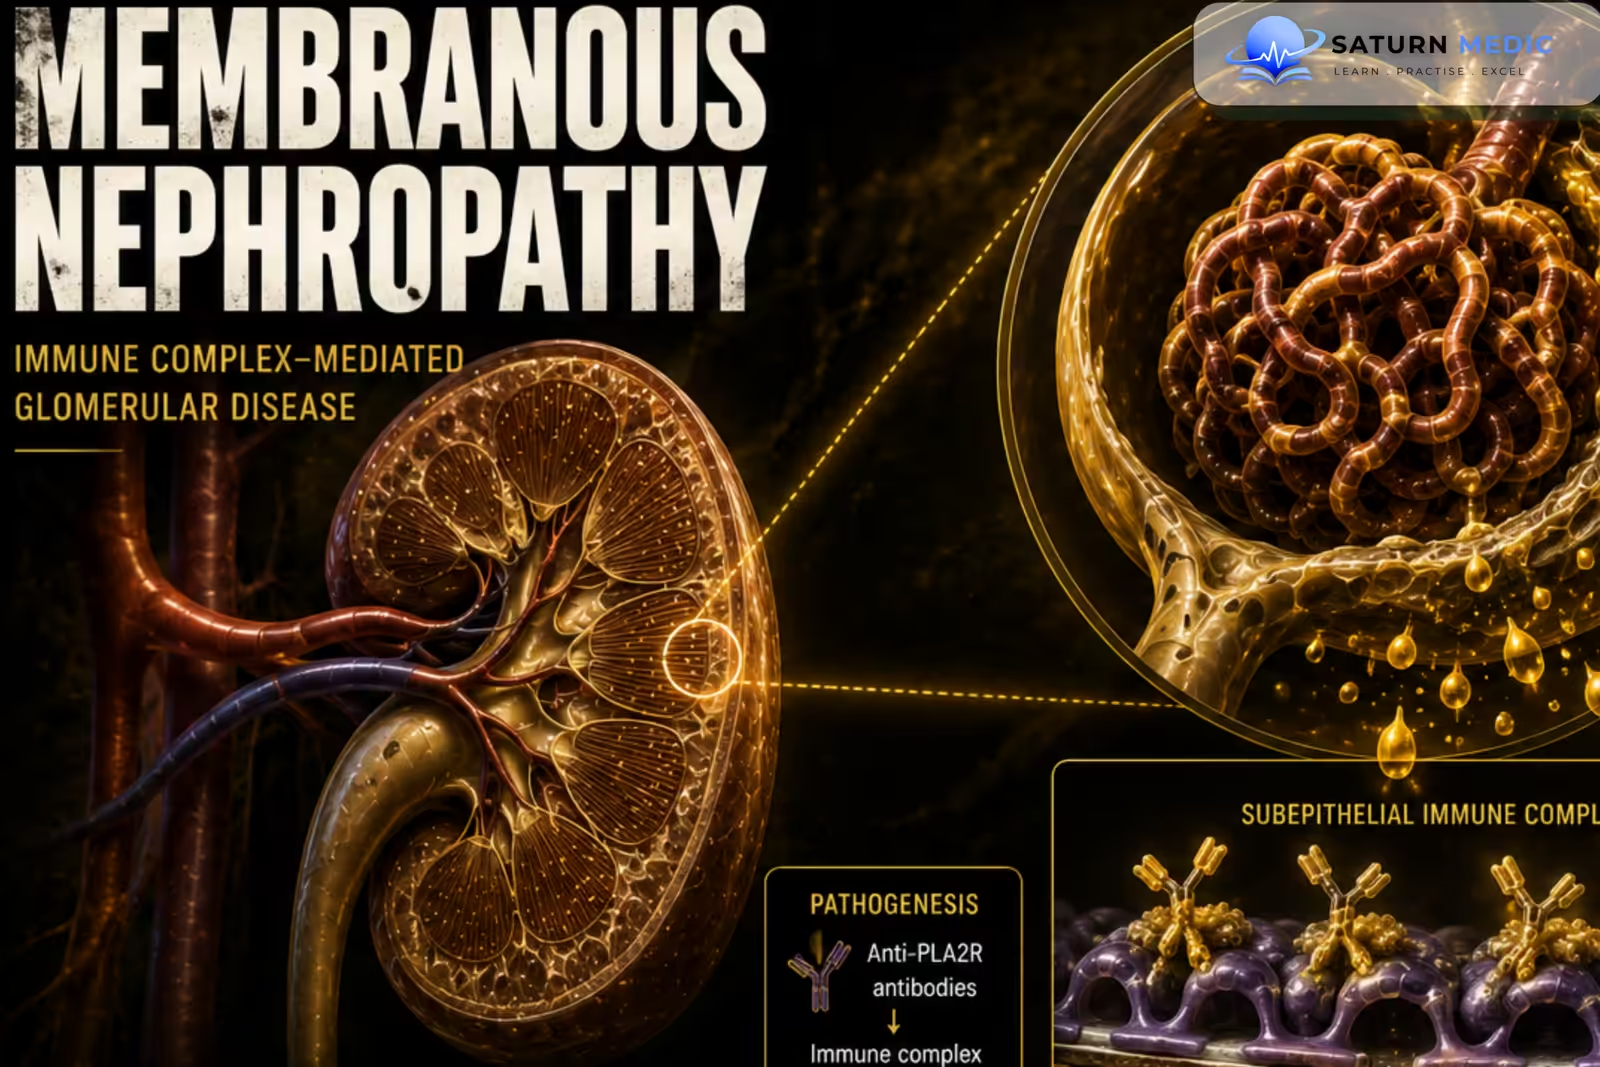
Membranous Nephropathy is a glomerular disease characterized by thickening of the glomerular basement membrane due to immune complex deposition. It is a common cause of nephrotic syndrome in adults.
Also called
ICD-10
Specialty
Onset
Reviewed
-
OverviewOverview
-
Etiology & Risk FactorsEtiology & Risk Factors
-
PathophysiologyPathophysiology
-
Clinical PresentationClinical Presentation
-
History TakingHistory Taking
-
Physical ExaminationPhysical Examination
-
InvestigationsInvestigations
-
DiagnosisDiagnosis
-
ManagementManagement
-
ComplicationsComplications
-
PrognosisPrognosis
-
Key Points / Clinical PearlsKey Points / Clinical Pearls
Overview
-Membranous Nephropathy is caused by immune-mediated injury to the glomerular filtration barrier, particularly the podocytes and Glomerular Basement Membrane (GBM).
-It may be:
- Primary membranous nephropathy — most commonly associated with antibodies against phospholipase A2 receptor (PLA2R)
- Secondary membranous nephropathy — associated with autoimmune disease, infections, malignancy, or certain medications
-The main clinical manifestation is proteinuria, often causing nephrotic syndrome.
Etiology & Risk Factors
-Etiology
–The disease results from immune complex formation along the glomerular basement membrane, causing podocyte injury and protein leakage.
-Major causes include:
- Primary autoimmune disease, commonly involving anti-PLA2R antibodies
- Systemic Lupus Erythematosus
- Chronic infections
- Malignancy
- Certain medications
-Risk Factors:
- Older age
- Autoimmune disease
- Chronic hepatitis B or other relevant infections
- Malignancy
- Exposure to causative medications
Pathophysiology
Autoantibody formation or secondary immune trigger → subepithelial immune complex deposition → complement activation → podocyte injury → glomerular basement membrane thickening → increased protein permeability → proteinuria → nephrotic syndrome → progressive kidney damage
Clinical Presentation
-Symptoms:
- Frothy urine
- Peripheral edema
- Weight gain
- Fatigue
- Reduced urine output in severe disease
-Signs:
- Peripheral or generalized edema
- Hypertension
- Features of nephrotic syndrome
History Taking
-Ask about:
- Frothy urine and edema
- Duration and progression of symptoms
- Previous kidney disease
- Symptoms of systemic lupus erythematosus or other autoimmune disease
- Symptoms suggesting chronic infection
- Unexplained weight loss or symptoms suggesting malignancy
- Medication history
- Previous thrombosis
- Family history of autoimmune or kidney disease
Physical Examination
-General Examination
- Blood pressure
- Peripheral or generalized edema
- Weight changes
-System-Specific Examination:
- Signs of venous thrombosis
- Features of autoimmune disease
- Signs suggesting underlying malignancy or infection
Investigations
-Biochemistry / Specific Tests
Urinalysis
Urine protein-to-creatinine ratio or 24-hour urine protein
Serum albumin
Serum creatinine and eGFR
Lipid profile
Anti-PLA2R antibody testing
Tests for secondary causes when clinically indicated
-Imaging
Renal ultrasound may assess kidney structure and exclude other abnormalities.
–Additional imaging may be required when evaluating suspected malignancy or thrombosis.
-Special / Confirmatory Tests
Kidney biopsy is often used to confirm the diagnosis and assess histological features.
Typical findings include:
Diffuse thickening of the glomerular basement membrane
Subepithelial immune deposits
Granular immunoglobulin and complement deposition on immunofluorescence
Diagnosis
-Diagnosis is based on:
- Significant proteinuria, often nephrotic-range
- Hypoalbuminemia
- Assessment of kidney function
- Anti-PLA2R antibody testing
- Evaluation for secondary causes
- Kidney biopsy when required
A strongly positive anti-PLA2R antibody in an appropriate clinical setting may support the diagnosis of primary membranous nephropathy
Management
1. Definitive Treatment
Treatment depends on the risk of progressive kidney disease.
Low-risk disease: supportive management and monitoring
Moderate- or high-risk disease: immunosuppressive therapy may be required
Secondary membranous nephropathy: treat the underlying cause
2 Medical Treatment
ACE inhibitors or ARBs to reduce proteinuria and control blood pressure
Diuretics for edema
Statins when indicated
Anticoagulation in selected high-risk patients
Rituximab for appropriate patients requiring immunosuppressive treatment
Cyclophosphamide-based therapy or calcineurin inhibitors in selected patients
3. Surgical / Procedural Treatment
No routine surgical treatment.
Kidney replacement therapy may be required if kidney failure develops.
4. Supportive Management
Sodium restriction
Blood pressure control
Reduction of proteinuria
Monitoring kidney function
Monitoring serum albumin and proteinuria
Complications
- Nephrotic syndrome
- Severe edema
- Hypoalbuminemia
- Hyperlipidemia
- Venous thromboembolism
- Renal vein thrombosis
- Acute kidney injury
- Progressive Chronic Kidney Disease (CKD)
- Kidney failure
Prognosis
-The prognosis varies considerably. Some patients undergo spontaneous remission, while others develop persistent proteinuria and progressive kidney dysfunction
–Persistent heavy proteinuria, declining eGFR, and high disease activity are associated with a poorer prognosis.
Key Points / Clinical Pearls
- Membranous Nephropathy is a common cause of nephrotic syndrome in adults.
- It is characterized by immune-mediated podocyte injury.
- Primary disease is commonly associated with anti-PLA2R antibodies.
- Secondary causes include autoimmune disease, infection, malignancy, and medications.
- Heavy proteinuria is the main clinical feature.
- Edema and hypoalbuminemia are common in nephrotic syndrome.
- Anti-PLA2R testing is important for diagnosis and monitoring.
- Kidney biopsy may confirm the diagnosis and assess the disease.
- Patients have an increased risk of venous thromboembolism.
- ACE inhibitors or ARBs help reduce proteinuria.
- Not all patients require immediate immunosuppressive therapy.
- Rituximab is an important treatment option for appropriate patients.
- Kidney Disease: Improving Global Outcomes (KDIGO) Glomerular Diseases Work Group. KDIGO 2021 Clinical Practice Guideline for the Management of Glomerular Diseases. Kidney Int. 2021;100(4S):S1-S276. KDIGO .
- Ronco P, Beck L, Debiec H, et al. Membranous Nephropathy. Nat Rev Dis Primers. 2021;7(1):69. Nature Reviews Disease Primers .
- Sethi S, Glassock RJ. Natural History and Management of Membranous Nephropathy. Kidney Int. 2013;83(5):861-873.
- Fervenza FC, Appel GB, Barbour SJ, et al. Rituximab or Cyclosporine in the Treatment of Membranous Nephropathy. N Engl J Med. 2019;381(1):36-46. New England Journal of Medicine .
- National Institute of Diabetes and Digestive and Kidney Diseases (NIDDK). Membranous Nephropathy . National Institutes of Health.
- National Library of Medicine (NIH). Membranous Nephropathy . StatPearls.