
Clinical Subject Page

Ureteropelvic Junction (UPJ) Obstruction
Varicocele is an abnormal dilatation of the pampiniform plexus of veins within the spermatic cord. It commonly occurs on the left side and may cause scrotal discomfort, testicular atrophy, or impaired fertility
Also called
ICD-10
Specialty
Onset
Reviewed
-
OverviewOverview
-
Etiology & Risk FactorsEtiology & Risk Factors
-
PathophysiologyPathophysiology
-
Clinical PresentationClinical Presentation
-
History TakingHistory Taking
-
Physical ExaminationPhysical Examination
-
InvestigationsInvestigations
-
DiagnosisDiagnosis
-
ManagementManagement
-
ComplicationsComplications
-
PrognosisPrognosis
-
Key Points / Clinical PearlsKey Points / Clinical Pearls
Overview
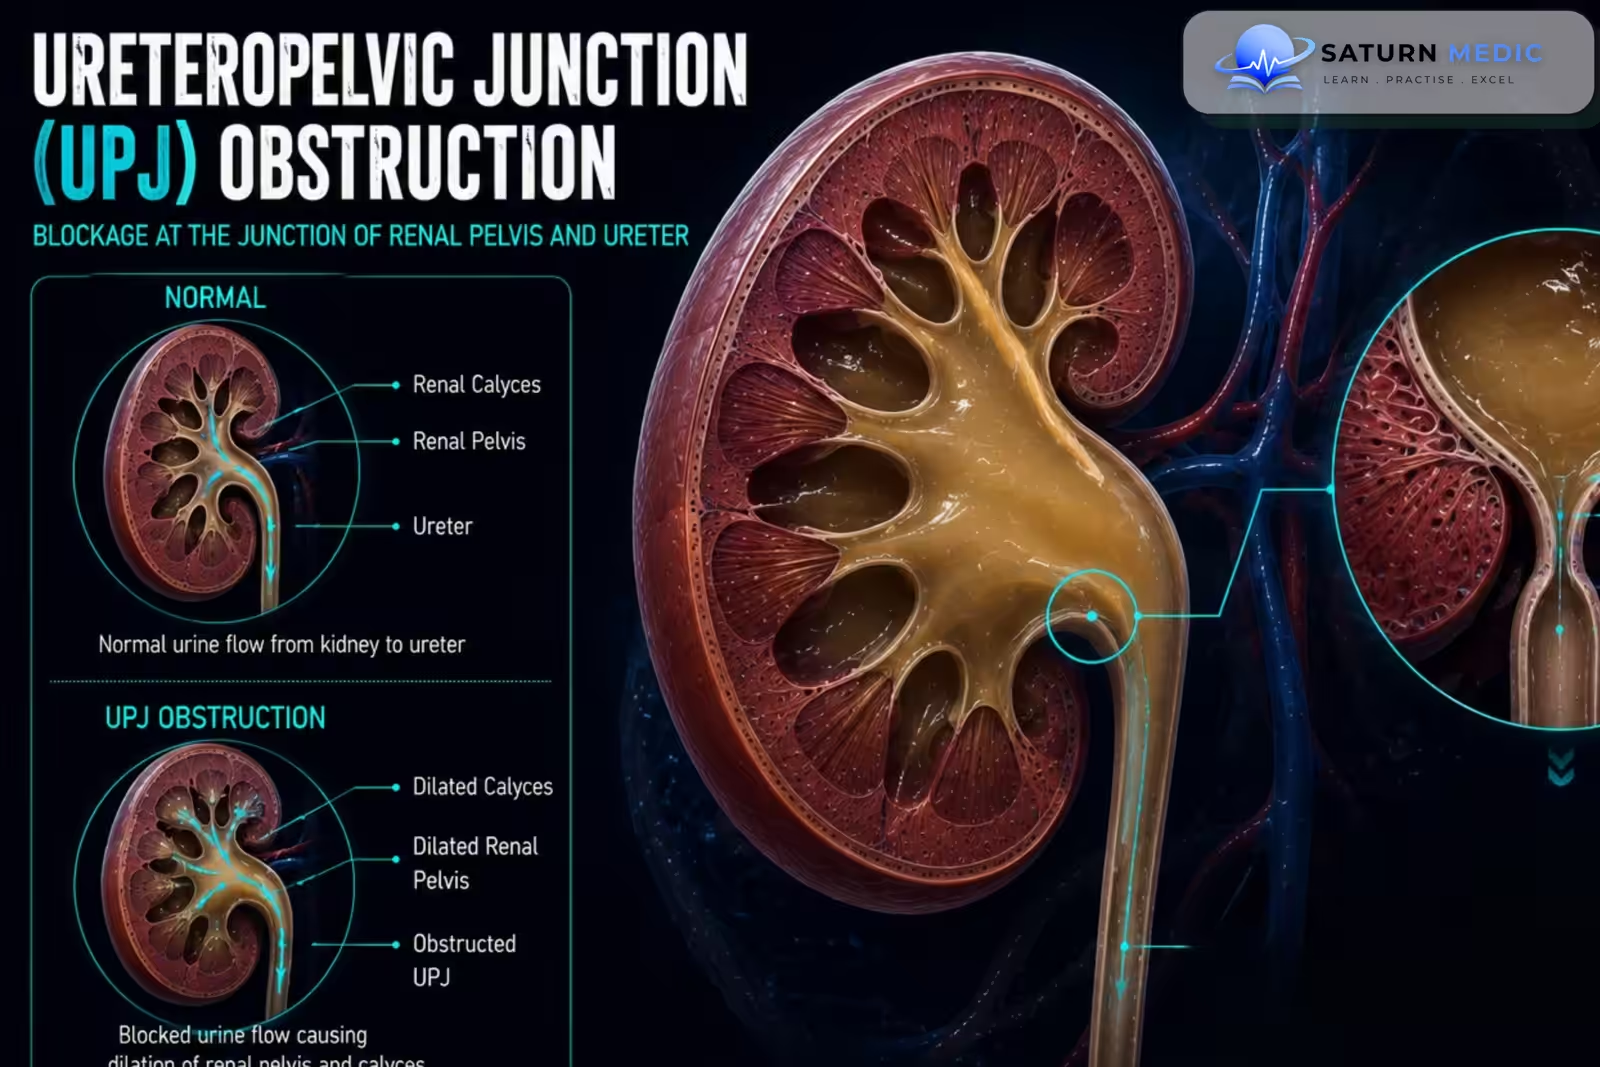
-Ureteropelvic Junction (UPJ) Obstruction is one of the most common causes of congenital Hydronephrosis. It may also develop later in life.
The obstruction may be:
- Congenital: caused by abnormal development or narrowing of the UPJ
- Acquired: caused by scarring, stones, surgery, inflammation, or other pathology
-An external crossing blood vessel may contribute to obstruction in some patients.
-The condition may be detected before birth, during childhood, or later in adulthood.
Etiology & Risk Factors
-Etiology:
Congenital Causes
- Intrinsic narrowing of the ureteropelvic junction
- Abnormal smooth-muscle development
- Abnormal insertion of the ureter
- High ureteral insertion
- Crossing renal vessels causing intermittent external compression
-Acquired Causes
- Scarring after previous surgery
- Urinary stones
- Inflammation
- Trauma
- Fibrosis
- Rarely, tumors
-Risk Factors
- Congenital urinary tract abnormalities
- Previous urinary tract surgery
- History of urinary stones
Pathophysiology
Narrowing or functional obstruction at the ureteropelvic junction → impaired urine drainage from the renal pelvis → urine accumulation → increased intrapelvic pressure → Hydronephrosis → progressive renal parenchymal compression → reduced renal function → renal damage if obstruction is severe or prolonged
Clinical Presentation
–Symptoms
-
The presentation varies with age.
Infants and Children
- Often asymptomatic
- Prenatally detected Hydronephrosis
- Abdominal mass in severe cases
- Recurrent Urinary Tract Infection (UTI)
- Poor growth in severe bilateral disease
Adults
- Intermittent flank pain
- Pain after increased fluid intake
- Nausea and vomiting
-Signs:
- Costovertebral angle tenderness during symptomatic episodes
- Palpable abdominal or flank mass in severe Hydronephrosis
- Fever when infection is present
History Taking
-Ask about:
- Prenatal history of Hydronephrosis
- Age at diagnosis
- Flank pain and whether it is intermittent
- Pain after increased fluid intake
- Nausea or vomiting
- Hematuria
- Recurrent Urinary Tract Infection (UTI)
- Previous urinary stones
- Previous urinary tract surgery
Physical Examination
-General Examination
- Growth and development in children
- Temperature when infection is suspected
- Blood pressure
- General signs of renal impairment in advanced disease
-System-Specific Examination:
- Flank tenderness
- Palpable abdominal or flank mass in severe Hydronephrosis
- Costovertebral angle tenderness during acute symptoms
Investigations
-Complete Blood Count
Not routinely required.
It may be useful when infection or systemic illness is suspected.
-Biochemistry / Specific Tests
-
Serum creatinine and assessment of kidney function in significant or bilateral disease
-
Urinalysis for hematuria and infection
-
Urine culture when Urinary Tract Infection (UTI) is suspected
-Imaging
Renal Ultrasound
Usually the first-line investigation.
It assesses:
-
Hydronephrosis
-
Renal size
-
Renal parenchymal thickness
-
Progression over time
-CT Urography
Useful in selected adults to assess:
-
Anatomical obstruction
-
Urinary stones
-
Crossing vessels
-
Alternative causes of obstruction
Magnetic Resonance Urography
Useful when detailed anatomy and functional assessment are required without ionizing radiation
Diagnosis
-Diagnosis of Ureteropelvic Junction (UPJ) Obstruction is based on:
Imaging demonstrating Hydronephrosis at the renal pelvis + evidence of impaired drainage at the Ureteropelvic Junction (UPJ) + functional assessment of renal drainage and differential kidney function.
Diuretic renography is particularly important when deciding whether the obstruction is clinically significant
Management
1. First-Line / Emergency Management
There is no routine emergency treatment for uncomplicated Ureteropelvic Junction (UPJ) Obstruction.
Urgent treatment may be required when obstruction is associated with:
-
Infection or sepsis
-
Severe pain
-
Significant Acute Kidney Injury (AKI)
-
Obstruction of a solitary functioning kidney
2. Definitive Treatment
Observation
Appropriate for selected patients with:
-
Mild disease
-
Stable Hydronephrosis
-
Preserved renal function
-
No significant symptoms
Pyeloplasty
Pyeloplasty is the standard definitive treatment for significant Ureteropelvic Junction (UPJ) Obstruction.
It involves reconstruction of the obstructed junction to restore normal urine drainage.
It may be performed using:
-
Open surgery
-
Laparoscopic surgery
-
Robotic-assisted surgery
3. Medical Treatment
There is no medication that reliably corrects a structural Ureteropelvic Junction (UPJ) Obstruction.
Medical treatment may include:
-
Analgesics for pain
-
Antibiotics for confirmed infection
-
Treatment of associated urinary stones
Complications
- Progressive Hydronephrosis
- Recurrent Urinary Tract Infection (UTI)
- Pyelonephritis
- Renal stone formation
- Renal atrophy
- Reduced renal function
- Acute Kidney Injury (AKI)
Prognosis
The prognosis is generally excellent when significant Ureteropelvic Junction (UPJ) Obstruction is recognized and treated before irreversible renal damage occurs. Many mild cases remain stable with observation. Pyeloplasty has a high success rate and usually improves urinary drainage and preserves renal function. Prognosis is worse when diagnosis is delayed until substantial loss of renal function has already occurred.
Key Points / Clinical Pearls
- Ureteropelvic Junction (UPJ) Obstruction is impaired urine drainage where the renal pelvis joins the ureter.
- It is a common cause of congenital Hydronephrosis.
- The condition may also be acquired later in life.
- Crossing vessels can contribute to obstruction in some patients.
- Flank pain may be intermittent and triggered by increased urine production.
- Recurrent Urinary Tract Infection (UTI) and stones can occur.
- Renal ultrasound is usually the first-line investigation.
- Hydronephrosis alone does not prove significant obstruction.
- Diuretic renography is the key functional test.
- Differential renal function helps guide management.
- Mild and stable cases may be managed with observation.
- Significant symptoms or declining renal function usually require intervention.
- Pyeloplasty is the standard definitive treatment.
- European Association of Urology (EAU) – Paediatric Urology Guidelines . Ureteropelvic junction obstruction: diagnosis, imaging, differential diagnosis, and management.
- American Urological Association (AUA) – Pediatric Urology Guidelines . Pediatric upper urinary tract obstruction and related urological conditions.
- Ureteropelvic Junction Obstruction. StatPearls . NCBI Bookshelf. Clinical overview of congenital and acquired ureteropelvic junction obstruction.
- Braga LH, et al. Ureteropelvic junction obstruction in children . Review of presentation, diagnostic evaluation, and surgical management of pediatric ureteropelvic junction obstruction.