

Clinical Subject Page
Human Immunodeficiency Virus (HIV) Infection
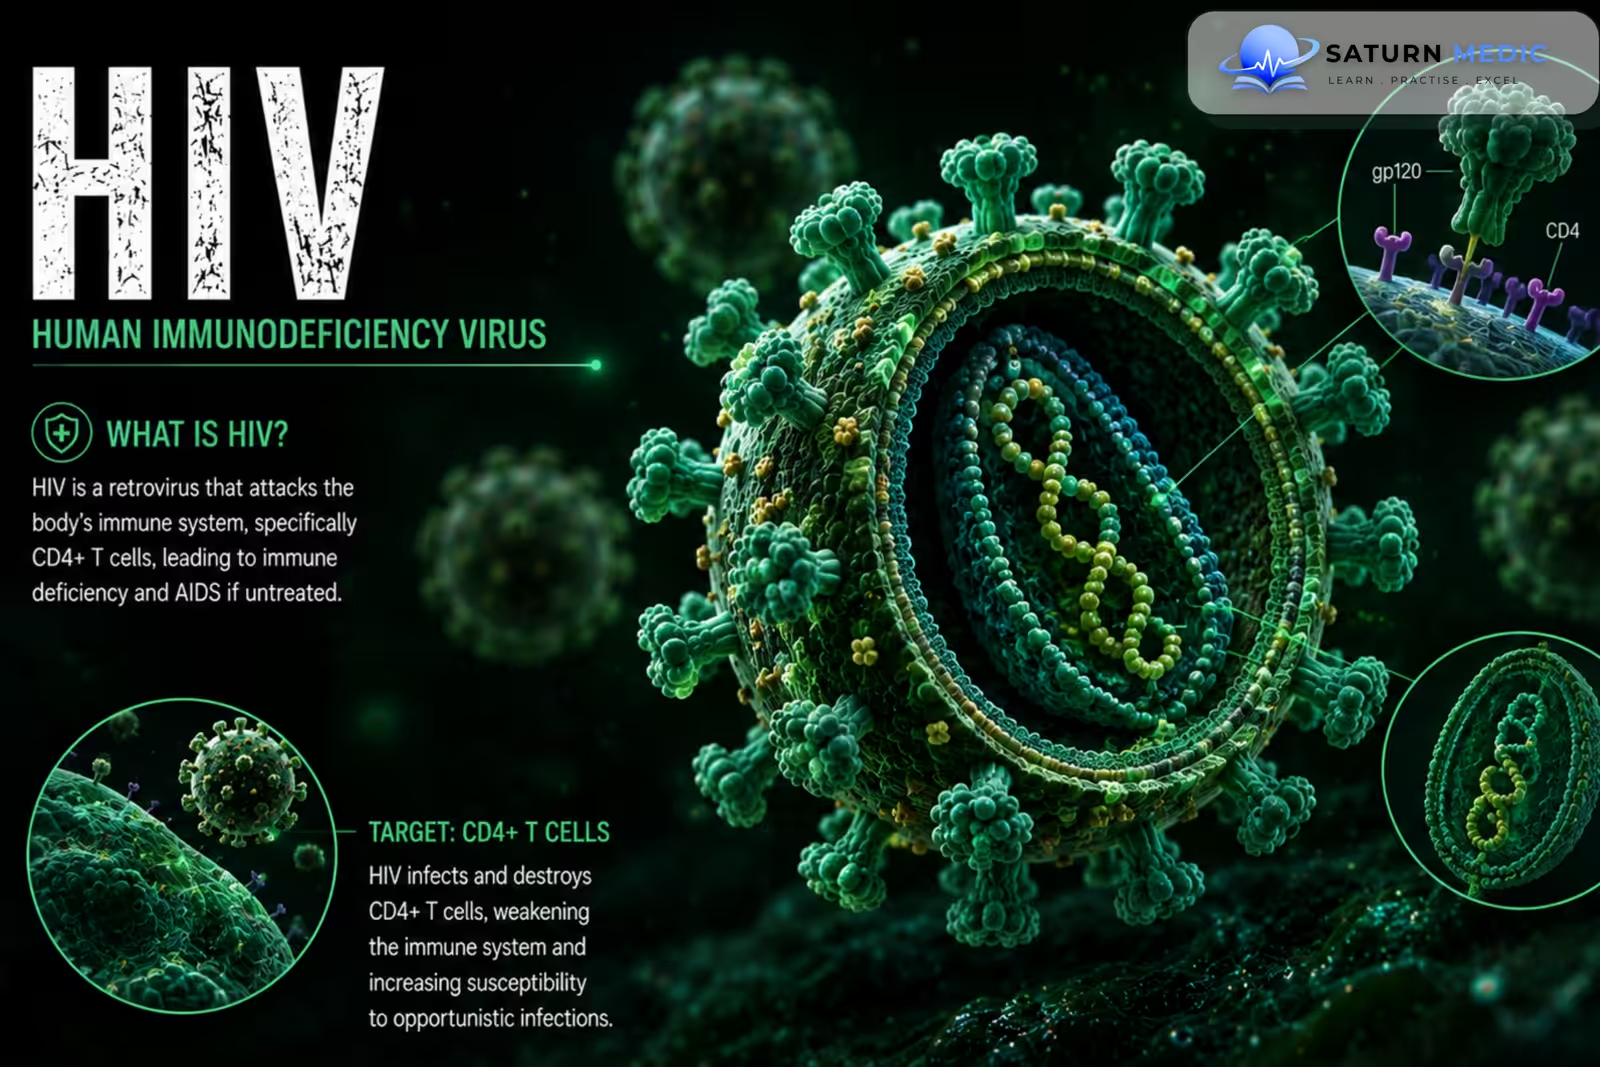
Human Immunodeficiency Virus (HIV) is a viral infection that progressively damages the immune system, mainly by infecting and destroying CD4 T lymphocytes. Without effective treatment, progressive immune deficiency can lead to opportunistic infections, malignancies, and Acquired Immunodeficiency Syndrome (AIDS)
Also called
ICD-10
Specialty
Onset
Reviewed
-
OverviewOverview
-
Etiology & Risk FactorsEtiology & Risk Factors
-
PathophysiologyPathophysiology
-
Clinical PresentationClinical Presentation
-
History TakingHistory Taking
-
Physical ExaminationPhysical Examination
-
InvestigationsInvestigations
-
DiagnosisDiagnosis
-
ManagementManagement
-
ComplicationsComplications
-
PrognosisPrognosis
-
Key Points / Clinical PearlsKey Points / Clinical Pearls
Overview
-Human Immunodeficiency Virus (HIV) transmitted mainly through:
- Sexual contact
- Blood exposure
- Sharing contaminated needles
- Mother-to-child transmission during pregnancy, delivery, or breastfeeding
-The infection progresses through an acute phase, a chronic phase, and, without adequate treatment, advanced immune deficiency.
Modern antiretroviral therapy (ART) can suppress viral replication, preserve immune function, prevent progression, and greatly reduce transmission.
Etiology & Risk Factors
-Etiology
–The causative virus is Human Immunodeficiency Virus (HIV), mainly:
- HIV-1 — responsible for most infections worldwide
- HIV-2 — less common and concentrated mainly in West Africa
The virus primarily targets CD4 T lymphocytes, macrophages, and dendritic cells.
-Risk Factors for Human Immunodeficiency Virus (HIV)
- Unprotected sexual exposure
- Multiple sexual partners
- Sharing injection equipment
- Exposure to contaminated blood
- Perinatal exposure
- High-risk occupational exposure
Pathophysiology
Human Immunodeficiency Virus (HIV) enters the body → binds CD4 cells → viral replication → progressive CD4 T-cell loss and dysfunction → impaired cellular immunity → increased susceptibility to opportunistic infections and malignancies → advanced immune deficiency/AIDS
Clinical Presentation
-Symptoms:
Acute Human Immunodeficiency Virus (HIV) Infection
Often occurs 2–4 weeks after infection and may resemble a viral illness:
- Fever
- Sore throat
- Rash
- Lymphadenopathy
- Myalgia
- Headache
- Fatigue
- Oral ulcers
Chronic Human Immunodeficiency Virus (HIV) Infection
May remain asymptomatic for years.
Possible symptoms include:
- Persistent lymphadenopathy
- Recurrent infections
- Weight loss
- Chronic diarrhea
- Fever
-Signs:
- Generalized lymphadenopathy
- Weight loss
- Oral candidiasis
- Recurrent infections
- Skin manifestations
History Taking
-Ask about:
- Recent sexual exposure
- Condom use
- Number and type of sexual partners
- Previous sexually transmitted infections
- Injection drug use
- Needle sharing
- Previous blood transfusions when relevant
- Occupational exposure
- Pregnancy or breastfeeding status when applicable
- Previous HIV testing
- Previous opportunistic infections
- Weight loss
- Chronic diarrhea
- Fever and night sweats
Physical Examination
-General Examination
- Weight and nutritional status
- Temperature
- Lymph nodes
- Skin and mucous membranes
Look for:
- Lymphadenopathy
- Oral candidiasis
- Skin lesions
- Wasting
- Signs of opportunistic infection
-System-Specific Examination:
- Respiratory system
- Neurological system
- Oral cavity
- Skin
- Abdomen
Investigations
-Complete Blood Count
May show:
Anemia
Leukopenia
Thrombocytopenia
It is mainly used to assess complications and overall health rather than establish the diagnosis.
-Biochemistry / Specific Tests
Human Immunodeficiency Virus (HIV) Testing
Initial laboratory testing commonly uses a combination antigen/antibody test.
A reactive screening test requires an appropriate confirmatory testing algorithm.
Human Immunodeficiency Virus (HIV)-1 RNA
Used when:
Acute infection is suspected
Initial testing is indeterminate
Viral load needs to be measured
CD4 T-Cell Count
Used to assess:
Degree of immune suppression
Risk of opportunistic infections
Need for certain prophylactic therapies
Baseline immune status
Viral Load
Measures plasma Human Immunodeficiency Virus (HIV) RNA and is the main laboratory marker used to monitor response to ART.
Baseline Assessment
Common baseline tests include:
Renal function
Liver function
Glucose
Lipid profile
Hepatitis A, B, and C testing
Diagnosis
-Diagnosis of Human Immunodeficiency Virus (HIV) is established by:
Screening HIV antigen/antibody test → laboratory confirmation → Human Immunodeficiency Virus (HIV) -1 RNA when acute infection or an indeterminate result is suspected
After diagnosis:
CD4 count + viral load → assess immune status and establish baseline for treatment monitoring
AIDS is the most advanced stage and is defined by CD4 count <200 cells/mm³ or an AIDS-defining condition
Related Topics
Management
HIV · Management — When to Start & Monitoring
| Parameter | Target / Goal | Frequency | Action if abnormal |
|---|---|---|---|
| HIV Viral Load | Undetectable <50 copies/mL — treatment success | At baseline, 4 wks, 3 months, then every 3–6 months | If detectable at 6 months → resistance testing → switch regimen |
| CD4 Count | Should rise ~100–150 cells/μL/year on effective ART | Every 3–6 months until >200, then annually | CD4 <200 → add OI prophylaxis |
| Renal function (eGFR) | Monitor for TDF toxicity (proximal tubulopathy) | Every 3–6 months | eGFR drop → switch TDF to TAF or ABC |
| Lipids / glucose | Metabolic syndrome risk — especially with PIs | Annually | Switch PI; statin therapy |
| LFTs | Hepatotoxicity (NVP, PIs) + HBV flare if HBV+ | Every 3–6 months | Switch agent; manage HBV |
HIV · Antiretroviral Drug Classes
- Tenofovir (TDF / TAF) — backbone of most regimens; TAF safer for kidneys/bones
- Emtricitabine (FTC) — paired with TDF/TAF
- Abacavir (ABC) — requires HLA-B*5701 testing; hypersensitivity risk
- Lamivudine (3TC) — also active against HBV
- Zidovudine (AZT) — PMTCT; anaemia side effect
- Efavirenz (EFV) — once daily; CNS side effects (vivid dreams, depression)
- Rilpivirine (RPV) — fewer SE; requires food; not if VL >100,000
- Doravirine (DOR) — newer; fewer drug interactions
- Nevirapine (NVP) — hepatotoxicity risk; avoid if CD4 >250 (F) / 400 (M)
- Darunavir (DRV) — boosted with ritonavir or cobicistat; high barrier to resistance
- Atazanavir (ATV) — once daily; jaundice (benign ↑ bilirubin)
- Lopinavir/r (LPV/r) — used in resource-limited settings; GI SE
- Ritonavir (RTV) — pharmacokinetic booster only (inhibits CYP3A4)
- Dolutegravir (DTG) — preferred 1st line; high barrier to resistance; once daily
- Bictegravir (BIC) — in Biktarvy (BIC/TAF/FTC); excellent tolerability
- Cabotegravir (CAB) — injectable long-acting; monthly/bimonthly
- Raltegravir (RAL) — older; twice daily; fewer drug interactions
- Maraviroc (MVC) — blocks CCR5 co-receptor; requires tropism testing first (R5-tropic only)
- Enfuvirtide (T-20) — SC injection; salvage therapy only; expensive
- Fostemsavir — gp120 attachment; for heavily treatment-experienced
- First-in-class capsid inhibitor — multiple steps of HIV lifecycle
- SC injection every 6 months — highest barrier to resistance
- Approved for heavily treatment-experienced MDR-HIV
- Cabotegravir + rilpivirine (CAB+RPV) IM — monthly or every 2 months
- Alternative to daily pills for adherence challenges
Complications
HIV Complications · Opportunistic Infections by CD4 Count
Bacterial pneumonia (recurrent)
Herpes zoster (shingles)
Oral candidiasis (thrush)
Kaposi sarcoma (HHV-8)
Oesophageal candidiasis
Cryptosporidiosis
Microsporidiosis
Miliary TB
Cryptococcal meningitis
CMV retinitis / colitis
Bartonellosis
Progressive multifocal leukoencephalopathy (PML)
CMV disseminated
Disseminated histoplasmosis
Disseminated coccidioidomycosis
CNS lymphoma
- Dry cough, progressive dyspnea, fever — insidious onset
- CXR: bilateral perihilar ground-glass — may be normal early
- LDH markedly elevated; exercise desaturation
- Dx: BAL + silver stain / immunofluorescence
- Tx: Co-trimoxazole (high dose) + steroids if PaO₂ <70
- Most common OI worldwide — atypical CXR in low CD4
- CD4 <200: miliary, extrapulmonary, lower lobe — no cavitation
- CD4 >200: classic upper lobe cavitation
- Start ART 2 weeks after TB therapy (except TB meningitis — 4–8 wks)
- IRIS common — do NOT stop ART
- Bacterial pneumonia — recurrent (>2×/yr) = AIDS-defining; S. pneumoniae most common
- CMV pneumonitis — CD4 <50; bilateral interstitial; treat: ganciclovir
- Kaposi sarcoma (pulmonary) — haemoptysis, nodules, pleural effusion
- Lymphoma — B-cell NHL; mediastinal involvement
HIV Complications · CNS, GI & Systemic
- Fever, headache, focal deficits, seizures
- CT/MRI: multiple ring-enhancing lesions — basal ganglia
- Toxoplasma IgG positive (90%)
- Tx: Pyrimethamine + sulfadiazine + folinic acid × 6 wks
- DDx: CNS lymphoma (single lesion, EBV+, PET avid)
- Subacute headache, fever, neck stiffness — may be subtle
- LP: high opening pressure, India ink + (80%), CrAg positive
- Tx: Amphotericin B + flucytosine × 2 wks → fluconazole
- LP drainage critical — raised ICP = major cause of death
- Maintenance: Fluconazole lifelong until CD4 >200
- PML (JC virus) — CD4 <100; focal deficits, no fever; white matter lesions; no enhancement; no treatment except ART
- HIV encephalopathy (HAND) — subcortical dementia; cognitive decline, motor slowing; treated with ART
- CNS lymphoma — single enhancing lesion; EBV in CSF; treat with whole-brain RT
- Oesophageal candidiasis — CD4 <200; dysphagia + odynophagia; Tx: fluconazole
- CMV colitis — CD4 <50; bloody diarrhoea, ulcers; Tx: ganciclovir
- Cryptosporidiosis — CD4 <200; profuse watery diarrhoea; no reliable treatment — ART is key
- MAC — CD4 <50; chronic diarrhoea, fever, weight loss, high LDH; Tx: azithromycin + ethambutol
- Floaters, visual field loss, painless — "pizza pie" appearance on fundoscopy
- Fluffy white perivascular exudates + haemorrhage
- Tx: Ganciclovir / valganciclovir — lifelong until CD4 >100 × 3–6 months
- Most common cause of blindness in AIDS patients
- Kaposi sarcoma — HHV-8; violaceous skin/mucosal lesions; any CD4; Tx: ART ± chemotherapy
- NHL (non-Hodgkin lymphoma) — EBV-related; aggressive B-cell; Tx: R-CHOP
- Cervical cancer — HPV-related; AIDS-defining; annual cervical screening
- Anal cancer — HPV; MSM; high-resolution anoscopy
Prognosis
With effective ART, people living with Human Immunodeficiency Virus (HIV) can achieve long-term viral suppression and substantially improved health outcomes. WHO notes that effective ART reduces HIV-associated illness and death and prevents onward sexual transmission.
Key Points / Clinical Pearls
- Human Immunodeficiency Virus (HIV) is a virus that primarily targets CD4 T lymphocytes.
- HIV-1 causes most infections worldwide.
- Transmission occurs mainly through sexual exposure, blood exposure, and mother-to-child transmission.
- Acute infection may present with a flu-like illness, rash, sore throat, and lymphadenopathy.
- Chronic infection may remain asymptomatic for years.
- Progressive CD4 loss causes immune deficiency.
- Fourth-generation antigen/antibody testing is commonly used for initial diagnosis.
- Human Immunodeficiency Virus (HIV) -1 RNA is important when acute infection is suspected.
- CD4 count assesses immune status and opportunistic infection risk.
- Viral load is the main marker of treatment response.
- AIDS is defined by CD4 <200 cells/mm³ or an AIDS-defining condition.
- ART should be started as soon as possible after diagnosis.
- World Health Organization (WHO). HIV and AIDS .
- Centers for Disease Control and Prevention (CDC). HIV .
- Panel on Antiretroviral Guidelines for Adults and Adolescents. Guidelines for the Use of Antiretroviral Agents in Adults and Adolescents With HIV . U.S. Department of Health and Human Services.
- European AIDS Clinical Society (EACS). EACS Guidelines .
- Deeks SG, Overbaugh J, Phillips A, Buchbinder S. HIV Infection. Nat Rev Dis Primers. 2015;1:15035. PubMed .
- Fauci AS, Lane HC. Human Immunodeficiency Virus Disease: AIDS and Related Disorders. Harrison's Principles of Internal Medicine.
- National Library of Medicine (NIH). Human Immunodeficiency Virus Infection . StatPearls.