Saturn Medic

Clinical Cases

Chemical Pneumonitis

Clinical Subject Page

Also called

Aspiration pneumonitis — when caused by aspiration of gastric contents

ICD-10

J68.0

Specialty

Pulmonology

Onset

Acute & Chronic

Reviewed

July 2026
On This Page

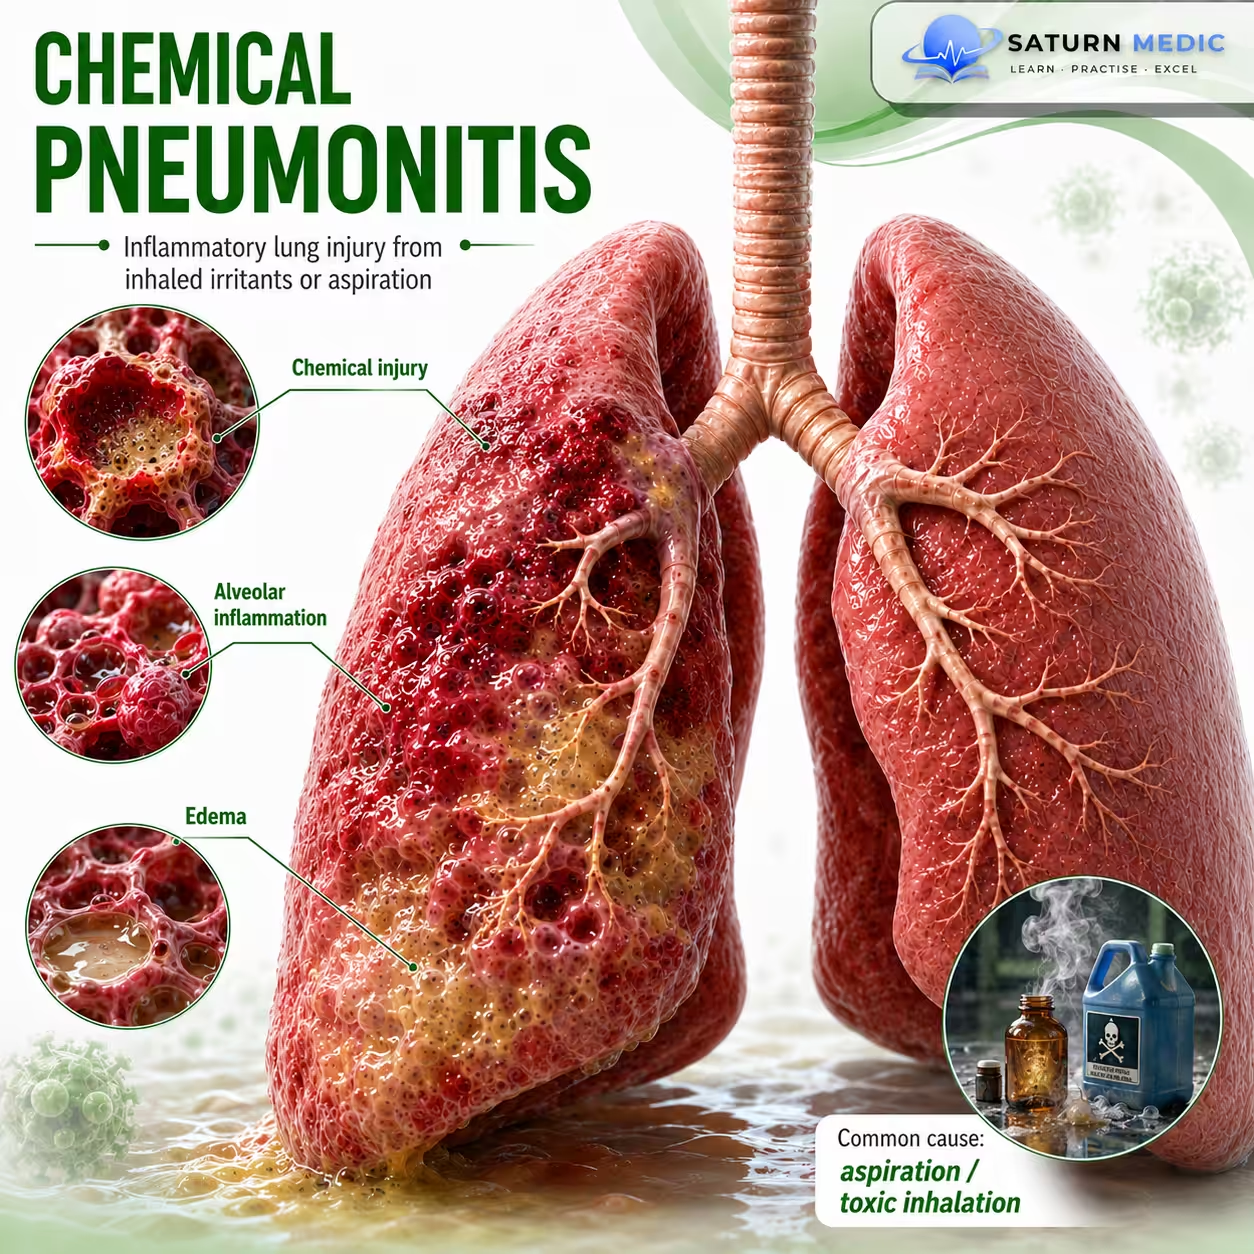
What is Chemical Pneumonitis?

Chemical substances can directly damage the:

  • Airways
  • Alveoli
  • Lung interstitium

The injury causes:

Chemical exposure → Direct lung tissue damage → Inflammation → Edema → Impaired gas exchange and leading to Chemical Pneumonitis

Severe cases may progress to acute respiratory failure or acute respiratory distress syndrome (ARDS).

Etiology & Risk Factors

Common Causes of Chemical Pneumonitis

-Aspiration of Gastric Contents

  • Vomiting

  • Reduced consciousness

  • General anesthesia

  • Seizures

-Inhaled Gases and Fumes

  • Chlorine gas

  • Ammonia

  • Nitrogen dioxide

  • Sulfur dioxide

  • Smoke

-Hydrocarbons

  • Gasoline

  • Kerosene

  • Petroleum products

-Other Chemical Exposures

  • Cleaning products

  • Industrial chemicals

  • Pesticides

  • Solvents

-Risk Factors For Chemical Pneumonitis

  • Occupational chemical exposure

  • Fire or smoke exposure

  • Poorly ventilated environments

  • Reduced consciousness

  • Dysphagia

  • Vomiting

  • Seizures

  • General anesthesia

  • Substance intoxication

Important Note

Chemical pneumonitis is caused by direct tissue injury and is not initially a bacterial infection.

Pathophysiology

Inhalation or aspiration of toxic substance
⬇
Direct injury to airway and alveolar cells
⬇
Inflammatory response
⬇
Increased capillary permeability
⬇
Pulmonary edema + Alveolar damage
⬇
Impaired ventilation and gas exchange
⬇
Hypoxemia
⬇
Severe injury → ARDS and respiratory failure

Key Concept

The severity of Chemical pneumonitis depends on the type, concentration, duration, and amount of chemical exposure.

Clinical Presentation

Symptoms

  • Sudden cough
  • Dyspnea
  • Chest tightness
  • Burning sensation in the chest
  • Wheezing
  • Choking
  • Chest pain

After Aspiration

May include:

  • Sudden coughing
  • Respiratory distress
  • Hypoxemia
  • Fever

Signs

  • Tachypnea
  • Tachycardia
  • Reduced oxygen saturation
  • Wheezing
  • Crackles

Severe Disease

    • Cyanosis
    • Severe hypoxemia
    • Altered mental status
    • Respiratory failure
Chemical Pneumonitis Overview

History Taking

  • Ask about:

    • What substance was involved?
    • Was it inhaled or aspirated?
    • When did the exposure occur?
    • How long was the exposure?
    • Was the exposure in an enclosed space?
    • Cough or choking?
    • Shortness of breath?
    • Chest pain or tightness?
    • Vomiting or aspiration?
    • Loss of consciousness?

Physical Examination

-General Examination

Look for:

  • Respiratory distress
  • Tachypnea
  • Tachycardia
  • Cyanosis
  • Reduced oxygen saturation

-Chest Examination

Look for:

  • Wheezing
  • Crackles
  • Reduced air entry

-Upper Airway Examination

Look for:

  • Facial burns
  • Soot around the mouth or nose
  • Hoarseness
  • Stridor
  • Oropharyngeal burns

Investigations of Chemical pneumonitis

-Pulse Oximetry

Assess oxygen saturation.

-Arterial Blood Gas

Consider in:

  • Significant hypoxemia

  • Respiratory distress

  • Severe exposure

-Chest X-ray

May show:

  • Pulmonary infiltrates

  • Pulmonary edema

  • Diffuse bilateral opacities

Important Note

The initial chest X-ray may be normal despite significant lung injury.

-CT Chest

Consider when:

  • Diagnosis is uncertain

  • Symptoms are severe

  • Complications are suspected

-Additional Tests

Depending on the exposure:

    • CBC

    • Electrolytes

    • Renal function

    • ECG

    • Carboxyhemoglobin after smoke exposure

    • Methemoglobin level for specific toxic exposures

Types of Pneumonias

CAP vs HAP vs Chemical Pneumonitis · Overview

Community-Acquired
Pneumonia (CAP)
Outside hospital or <48h of admission
Hospital-Acquired
Pneumonia (HAP)
≥48h after hospital admission
Chemical
Pneumonitis
Non-infectious lung injury
Definition
Lung infection acquired outside hospital or within 48h of admission, in a non-healthcare resident
Lung infection developing ≥48 hours after hospital admission, including ventilator-associated pneumonia (VAP)
Non-infectious lung injury from inhalation or aspiration of chemical irritants — no bacteria involved initially
Common causes
S. pneumoniae H. influenzae Atypicals
Mycoplasma, Chlamydophila, Legionella — especially in younger patients. Viruses (influenza, COVID-19) increasingly common.
Gram-negative bacilli P. aeruginosa MRSA
Klebsiella, Acinetobacter, Enterobacter. Often multidrug-resistant (MDR) organisms.
Gastric acid Toxic gases Hydrocarbons
Aspiration of gastric contents (Mendelson's syndrome), smoke inhalation, chemical fumes, petroleum products.
Typical patient
Any age. Risk ↑ with: age >65, smoking, COPD, asplenia, immunosuppression, alcoholism
ICU patients, ventilated patients, post-surgery, prolonged hospitalisation, immunocompromised
Reduced consciousness (anaesthesia, seizures, alcohol intoxication), GERD, dysphagia, occupational chemical exposure
Onset
Acute — hours to days; fever, productive cough, pleuritic chest pain
Variable — often more insidious; may be masked by underlying illness or sedation in ICU
Rapid — symptoms within 1–6 hours of exposure; acute dyspnea, cough, bronchospasm

CAP vs HAP vs Chemical Pneumonitis · Management & Prognosis

Community-Acquired
Pneumonia (CAP)
Outside hospital or <48h of admission
Hospital-Acquired
Pneumonia (HAP)
≥48h after hospital admission
Chemical
Pneumonitis
Non-infectious lung injury
Severity score
CURB-65 — score 0–5; guides home vs hospital vs ICU disposition
CPIS score — Clinical Pulmonary Infection Score; uses temperature, WBC, secretions, oxygenation, CXR
PaO₂/FiO₂ ratio — severity of hypoxia; ARDS criteria if <300 with bilateral infiltrates
Treatment
Mild: Amoxicillin 500mg TDS oral
Moderate: Amoxicillin + Clarithromycin
Severe: Co-amoxiclav IV + Clarithromycin IV
Duration: 5–7 days (severe: 7–10)
Broad-spectrum IV: Pip-tazo or Meropenem
+ MRSA cover (Vancomycin / Linezolid) if risk factors
Duration: 7–8 days. De-escalate based on cultures.
Supportive: O₂, bronchodilators, NIV/intubation if needed
Corticosteroids — consider in severe cases
Antibiotics NOT given initially — add only if secondary bacterial infection develops
Remove source of exposure. Decontamination if skin/oral contact.
Prognosis
Generally good with treatment. 30-day mortality: ~5–14% (hospitalised). Full recovery expected in most; elderly & severe cases higher mortality.
Worse prognosis than CAP. 30-day mortality: ~20–50%. MDR organisms, ICU stay, and underlying disease worsen outcomes.
Variable — depends on agent and severity. Mild cases resolve in 24–72h. Severe cases may progress to ARDS with mortality >30%.

CAP vs HAP vs Chemical Pneumonitis · Key Differentiating Points

Key differentiating points
CAP — think typical vs atypical
Typical (S. pneumoniae): sudden onset, high fever, single lobe, productive cough
Atypical (Mycoplasma, Legionella): gradual onset, dry cough, bilateral, younger patient
Always use CURB-65 to guide admission decision
HAP — think resistant organisms
Always cover MDR Gram-negatives and Pseudomonas — standard CAP antibiotics are NOT adequate
VAP (ventilator-associated) = HAP developing ≥48h after intubation
Prevention: head-of-bed elevation 30–45°, oral chlorhexidine, early mobilisation, VAP bundles
Chemical pneumonitis — no antibiotics initially
No fever in early hours — fever = infection, not aspiration itself
Mendelson's syndrome = aspiration of sterile gastric acid — bilateral infiltrates, rapid onset
Start antibiotics only if no improvement by 48–72h or cultures become positive

Management of Chemical Pneumonitis

-Immediate Management For Chemical Pneumonitis

  • Remove the patient from further exposure

  • Ensure a safe environment

  • Assess airway, breathing, and circulation

  • Provide oxygen when needed

-Supportive Treatment

  • Oxygen therapy

  • Bronchodilators for bronchospasm

  • Mechanical ventilation if respiratory failure develops

-Aspiration Pneumonitis

  • Supportive care is the main treatment

  • Monitor respiratory status closely

-Antibiotics For Chemical Pneumonitis

  • Not routinely indicated for uncomplicated chemical or aspiration pneumonitis

  • Consider only when secondary bacterial infection is suspected

-Corticosteroids

  • Not routinely recommended

  • May be considered only in selected specific chemical exposures

-Severe Chemical Pneumonitis

May require:

    • ICU admission

    • High-flow oxygen

    • Mechanical ventilation

    • ARDS management

Complications of Chemical Pneumonitis

  • Acute respiratory failure
  • Acute respiratory distress syndrome (ARDS)
  • Pulmonary edema
  • Secondary bacterial pneumonia
  • Bronchospasm
  • Airway injury
  • Pulmonary fibrosis
  • Death

Prognosis of Chemical Pneumonitis

  • Prognosis depends on:
    • Type of chemical
    • Amount of exposure
    • Duration of exposure
    • Severity of initial lung injury
    • Development of ARDS
  • Mild cases may recover completely.
  • Severe exposure may cause prolonged respiratory failure.
  • Some patients develop chronic lung disease or pulmonary fibrosis.
  • Early removal from exposure and appropriate supportive care improve outcomes.

Key Points / Clinical Pearls of Chemical Pneumonitis

  • Chemical pneumonitis is caused by direct chemical injury to the lungs.
  • It is not initially a bacterial infection.
  • Aspiration of gastric contents is an important cause.
  • Symptoms may be immediate or delayed.
  • The initial chest X-ray may be normal.
  • Treatment is mainly supportive.
  • Antibiotics are not routinely required unless secondary infection is suspected.
  • Corticosteroids are not routinely recommended.
  • Severe cases may progress to ARDS and respiratory failure.
Test yourself

Practice Chemical Pneumonitis questions

Lock in what you just read with exam-style MCQs and active-recall flashcards from Saturn Medic.

More in Respiratory System Clinical Cases

SaturnMedic