
Clinical Subject Page

Fournier's Gangrene
Fournier’s Gangrene is a rapidly progressive, life-threatening form of necrotizing fasciitis affecting the perineum, external genitalia, and surrounding soft tissues. It is usually caused by a polymicrobial infection and can rapidly progress to sepsis, multiorgan failure, and death without immediate treatment.
Also called
ICD-10
Specialty
Onset
Reviewed
-
OverviewOverview
-
Etiology & Risk FactorsEtiology & Risk Factors
-
PathophysiologyPathophysiology
-
Clinical PresentationClinical Presentation
-
History TakingHistory Taking
-
Physical ExaminationPhysical Examination
-
InvestigationsInvestigations
-
DiagnosisDiagnosis
-
ManagementManagement
-
ComplicationsComplications
-
PrognosisPrognosis
-
Key Points / Clinical PearlsKey Points / Clinical Pearls
Overview
-Fournier’s Gangrene is a severe soft-tissue infection involving the fascial planes of the perineum and genital region. Infection may originate from the anorectal, genitourinary, or cutaneous regions and spreads rapidly along fascial planes.
It is usually polymicrobial, involving a mixture of aerobic and anaerobic organisms. Common pathogens include:
- Escherichia coli (E. coli)
- Streptococcus species
- Staphylococcus species
- Enterobacterales
- Bacteroides species
- Clostridium species in selected cases
Etiology & Risk Factors
-Etiology
–Fournier’s Gangrene usually begins with infection from a local source that spreads into the fascial planes.
Common sources include:
- Perianal or anorectal infection
- Perirectal abscess
- Urethral or urinary tract infection
- Genital skin infection or trauma
- Recent urological or anorectal procedures
- Skin breakdown or infected wounds
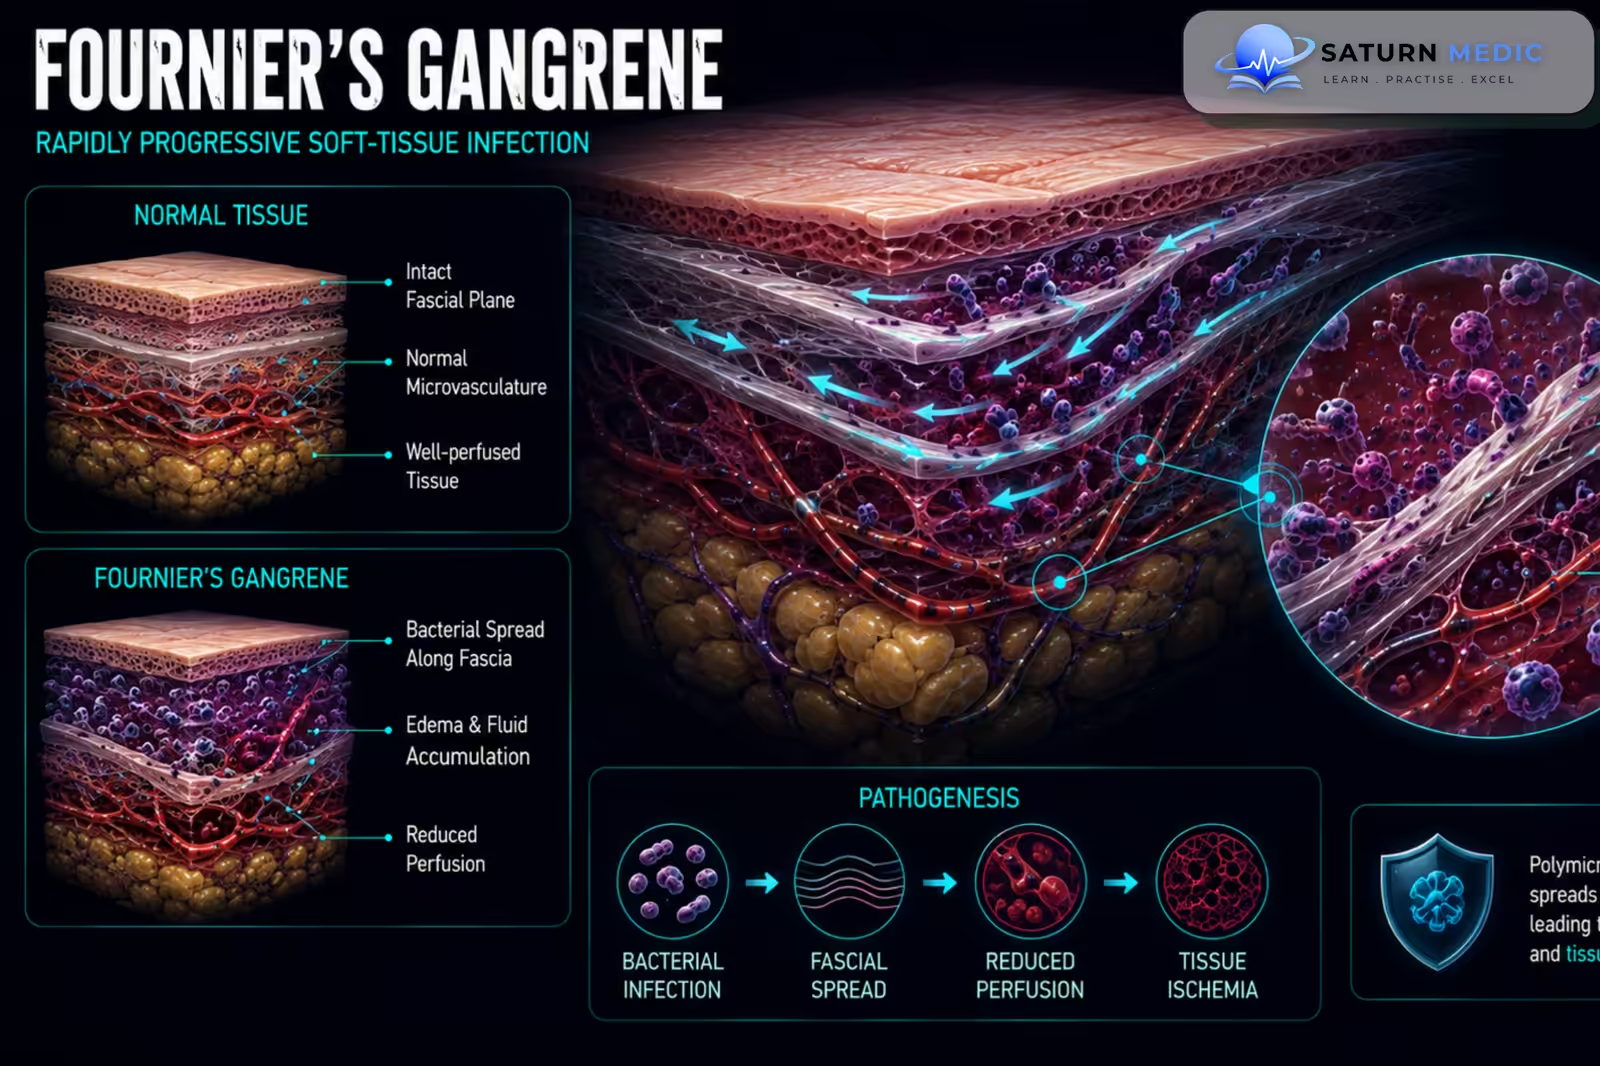
The infection causes thrombosis of small blood vessels, tissue ischemia, and rapidly progressive necrosis.
-Risk Factors
- Diabetes mellitus
- Immunosuppression
- Obesity
- Chronic kidney disease or severe renal dysfunction
- Alcohol misuse or severe malnutrition
Pathophysiology
Local anorectal, genitourinary, or skin infection → bacterial invasion of fascial planes → rapid polymicrobial spread → toxin production and inflammation → microvascular thrombosis → tissue ischemia → fascial and soft-tissue necrosis → bacteremia and sepsis → multiorgan failure
Clinical Presentation
–Symptoms
- Severe perineal or genital pain
- Pain out of proportion to examination findings
- Swelling of the scrotum or perineum
- Fever
- Malaise
- Weakness
- Foul-smelling discharge
-Signs:
- Perineal or genital edema
- Erythema
- Marked tenderness
- Skin discoloration
- Bullae
- Crepitus from gas-forming infection
- Areas of skin necrosis
- Foul-smelling drainage
History Taking
-Ask about:
- Time of symptom onset and rate of progression
- Severe genital or perineal pain
- Fever or chills
- Recent skin injury or wound
- Perianal pain or discharge
- Urinary symptoms
- Recent urinary catheterization
- Recent urological or anorectal procedures
- Previous abscesses or infections
- Diabetes mellitus
Physical Examination
-General Examination
- Temperature
- Heart rate
- Blood pressure
- Respiratory rate
- Mental status
- Signs of sepsis or shock
-System-Specific Examination:
- Inspect the perineum and external genitalia
- Assess erythema, swelling, and skin discoloration
- Look for bullae or necrosis
- Assess for crepitus
- Identify purulent or foul-smelling discharge
- Examine the anorectal and genitourinary regions when appropriate
Investigations
-Complete Blood Count
Relevant for assessing:
-
Leukocytosis or leukopenia
-
Severity of systemic infection
-
Baseline status before surgery
Biochemistry / Specific Tests
Important tests include:
-
Serum creatinine and electrolytes
-
Blood glucose
-
C-reactive protein
-
Serum lactate
-
Blood gas analysis in severe illness
-
Coagulation profile
-
Blood cultures
-
Wound or tissue cultures obtained when possible
These investigations help assess severity and guide treatment but must not delay surgery.
-Imaging
Imaging is not required when the diagnosis is clinically clear and should not delay surgical intervention.
CT Scan
May demonstrate:
-
Fascial thickening
-
Soft-tissue gas
-
Fluid collections
-
Extent of infection
-
Possible source of infection
Ultrasound
May demonstrate soft-tissue gas or fluid but has a limited role in definitive assessment.
-Special / Confirmatory Tests
Urgent surgical exploration is the definitive diagnostic and therapeutic procedure when Fournier’s Gangrene is strongly suspected.
Diagnosis
-Fournier’s Gangrene is primarily a clinical diagnosis based on:
Rapidly progressive perineal or genital infection + severe pain and systemic toxicity ± skin necrosis, bullae, or crepitus.
-Laboratory tests assess severity, while CT may help define the extent in stable patients. However, strong clinical suspicion requires immediate surgical assessment.
Management
1. First-Line / Emergency Management
Fournier’s Gangrene requires immediate emergency treatment.
Initial management includes:
-
Airway, breathing, and circulation assessment
-
Aggressive intravenous fluid resuscitation when indicated
-
Sepsis management
-
Immediate broad-spectrum intravenous antibiotics
-
Urgent surgical consultation
-
Blood and tissue cultures when possible without delaying treatment
-
Intensive care support for severe disease
2. Definitive Treatment
Urgent and aggressive surgical debridement of all necrotic tissue is the cornerstone of treatment.
Repeated surgical debridement is often necessary until all nonviable tissue has been removed.
3. Medical Treatment
Broad-spectrum intravenous antibiotics should cover:
-
Gram-positive organisms
-
Gram-negative organisms
-
Anaerobic organisms
Antibiotic therapy should then be adjusted according to culture results and local antimicrobial guidance.
Additional medical management may include:
-
Vasopressors for septic shock
-
Insulin therapy for uncontrolled hyperglycemia
-
Correction of electrolyte abnormalities
-
Nutritional support
4. Surgical / Procedural Treatment
-
Immediate extensive surgical debridement
-
Repeat debridement when required
-
Drainage of abscesses
-
Urinary diversion in selected cases
Complications
- Septic shock
- Acute Kidney Injury (AKI)
- Disseminated intravascular coagulation
- Multiorgan failure
- Extensive soft-tissue loss
- Urinary dysfunction
- Sexual dysfunction
Prognosis
The prognosis of Fournier’s Gangrene depends on how quickly treatment begins, the extent of infection, severity of sepsis, comorbidities, and adequacy of surgical debridement. Mortality remains significant, particularly in patients with delayed diagnosis, septic shock, extensive disease, or major underlying illness. Early recognition, rapid resuscitation, broad-spectrum antibiotics, and prompt aggressive surgery improve outcomes.
Key Points / Clinical Pearls
- Fournier’s Gangrene is a rapidly progressive necrotizing fasciitis of the perineum and genital region.
- It is a life-threatening surgical emergency.
- The infection is usually polymicrobial.
- Diabetes mellitus is an important risk factor.
- Severe pain out of proportion to the examination is an important early warning sign.
- Early skin findings may appear less severe than the underlying infection.
- Crepitus may occur but its absence does not exclude the disease.
- Fever, hypotension, and confusion suggest severe sepsis.
- Blood tests and imaging help assess severity but must not delay treatment.
- Urgent surgical debridement is the cornerstone of treatment.
- Multiple debridement procedures are often required.
- European Association of Urology (EAU). EAU Guidelines on Urological Infections .
- European Association of Urology (EAU). EAU Guidelines and Recommendations Relevant to Fournier's Gangrene .
- Stevens DL, Bisno AL, Chambers HF, et al. Practice Guidelines for the Diagnosis and Management of Skin and Soft Tissue Infections. Clin Infect Dis. 2014;59(2):e10-e52. Clinical Infectious Diseases .
- Eke N. Fournier's Gangrene: A Review of 1726 Cases. Br J Surg. 2000;87(6):718-728. British Journal of Surgery .
- Sorensen MD, Krieger JN, Rivara FP, et al. Fournier's Gangrene: Population Based Epidemiology and Outcomes. J Urol. 2009;181(5):2120-2126. Journal of Urology .
- National Library of Medicine (NIH). Fournier Gangrene . StatPearls.