
Also called
ICD-10
Specialty
Onset
Reviewed
-
OverviewOverview
-
Etiology & Risk FactorsEtiology & Risk Factors
-
PathophysiologyPathophysiology
-
Clinical PresentationClinical Presentation
-
History TakingHistory Taking
-
Physical ExaminationPhysical Examination
-
InvestigationsInvestigations
-
DiagnosisDiagnosis
-
ManagementManagement
-
ComplicationsComplications
-
PrognosisPrognosis
-
Key Points / Clinical PearlsKey Points / Clinical Pearls
Overview
• Rare but highly aggressive malignancy.
• Most cases are adenocarcinomas.
• Chronic gallbladder inflammation is the major predisposing factor.
• Early disease is often asymptomatic.
• Management depends on tumor stage and resectability.
Etiology & Risk Factors
• Cholelithiasis (most common risk factor)
• Chronic cholecystitis
• Porcelain gallbladder
• Choledocholithiasis
• Chronic cholangitis (e.g., salmonellosis)
• Gallbladder polyps
• Liver fluke infection (e.g., Clonorchis sinensis)
Pathophysiology
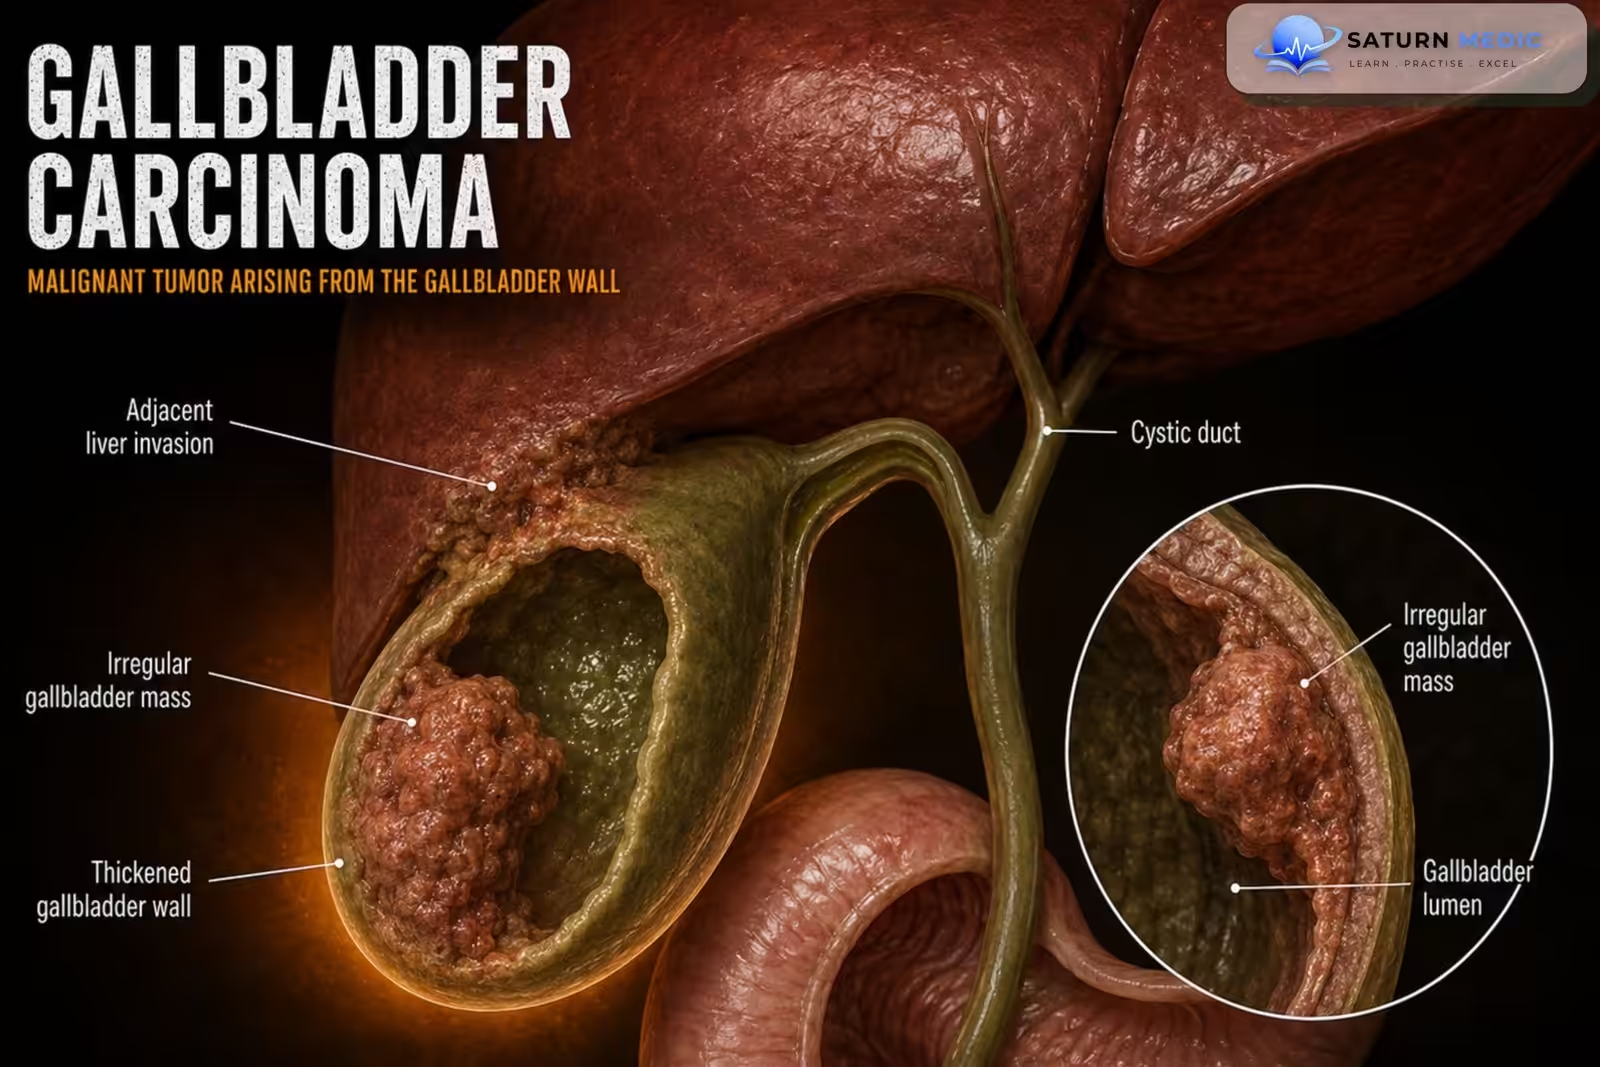
• Chronic inflammation of the gallbladder promotes malignant transformation of the mucosal
epithelium.
• Most tumors are adenocarcinomas.
• Tumors may invade the liver, lymph nodes, and adjacent structures.
Clinical Presentation
Early disease
• Usually asymptomatic
Symptomatic disease
• Right upper quadrant or epigastric pain
• Symptoms resembling biliary colic or chronic cholecystitis
• Weight loss
• Nausea
• Weakness
• Fatigue
• Abdominal mass
Advanced disease
• Obstructive jaundice (may occur, sometimes with Courvoisier sign)
History Taking
-Ask about:
• Right upper quadrant pain
• Weight loss
• Loss of appetite
• Nausea
• Fatigue
• History of gallstones
• Chronic cholecystitis
• Gallbladder polyps
• Previous biliary disease
Physical Examination
• General examination
• Right upper quadrant tenderness
• Abdominal mass
• Jaundice (advanced disease)
• Signs of biliary obstruction
• Assessment for metastatic disease
Investigations
Laboratory studies
• Liver chemistries (often normal)
• Tumor markers: CA 19-9, CEA
Tumor markers are used for baseline monitoring, not for diagnosis.
Imaging
• Transabdominal ultrasound: Gallbladder mass, Gallbladder wall thickening
• MRI/MRCP (preferred for evaluating local disease and vascular involvement)
• Multidetector CT (MDCT) abdomen and pelvis
• CT chest (± whole-body PET-CT) for staging
• Endoscopic ultrasound (EUS): Better visualization; may allow tissue sampling when required.
Pathology
• Preoperative biopsy is usually unnecessary.
• Diagnosis is commonly established from the resected surgical specimen.
• Adenocarcinoma is the most common histological type.
-Molecular testing: Consider in advanced disease or high risk of recurrence to identify therapeutic
targets (e.g., HER2 expression, IDH1 mutation).
Diagnosis
-Diagnosis is based on:
• Clinical suspicion
• Imaging studies
• Histopathology after surgical resection
• Staging with cross-sectional imaging
Related Topics
Management
-Surgical management (Curative treatment)
•T1a disease: Simple cholecystectomy may be sufficient.
•≥T1b disease: Extended surgical resection – Liver tissue resection; Portal lymph node dissection.
•Severe obstructive jaundice: Preoperative percutaneous transhepatic biliary drainage may be performed.
-Adjuvant therapy
After resection of T2 or more advanced disease: Gemcitabine + Cisplatin.
-Unresectable or advanced disease
• First-line: Gemcitabine + Cisplatin
• Second-line: FOLFOX; Targeted therapy when appropriate based on molecular testing
• Radiotherapy: May be used for palliative treatment.
Complications
• Local liver invasion
• Lymph node metastasis
• Biliary obstruction
• Metastatic disease
• Death
Prognosis
• Prognosis is generally poor.
• 5-year survival is <5% overall.
• Early-stage disease treated surgically offers the best chance of cure.
Key Points / Clinical Pearls
• Gallbladder carcinoma is the most common biliary tract malignancy.
• Cholelithiasis is the strongest risk factor.
• Early disease is often asymptomatic.
• Transabdominal ultrasound is the initial imaging study.
• MRI/MRCP is preferred for local staging.
• CT chest ± PET-CT is used for staging.
• CA 19-9 and CEA are monitoring markers, not diagnostic tests.
• Preoperative biopsy is usually unnecessary.
• Simple cholecystectomy is adequate for T1a disease.
• Extended resection is required for ≥T1b disease.
• Advanced disease is treated with gemcitabine + cisplatin, with FOLFOX or targeted therapy as
later options
- National Center for Biotechnology Information (NIH). Gallbladder Carcinoma, StatPearls.
- National Comprehensive Cancer Network (NCCN). NCCN Clinical Practice Guidelines in Oncology: Biliary Tract Cancers, Version 1.2026.
- Machado NO. Porcelain Gallbladder: Decoding the Malignant Truth. Sultan Qaboos Univ Med J. 2016;16:e416-e421. PMC5135451.
- National Center for Biotechnology Information (NIH). Porcelain Gallbladder, StatPearls.
- MedlinePlus, National Library of Medicine (NIH). Gallbladder Cancer: Health Topic.
Practice Gallbladder Carcinoma questions
Lock in what you just read with exam-style MCQs and active-recall flashcards from Saturn Medic.