
Also called
ICD-10
Specialty
Onset
Reviewed
-
OverviewOverview
-
Etiology & Risk FactorsEtiology & Risk Factors
-
PathophysiologyPathophysiology
-
Clinical PresentationClinical Presentation
-
History TakingHistory Taking
-
Physical ExaminationPhysical Examination
-
InvestigationsInvestigations
-
DiagnosisDiagnosis
-
ManagementManagement
-
ComplicationsComplications
-
PrognosisPrognosis
-
Key Points / Clinical PearlsKey Points / Clinical Pearls
Overview
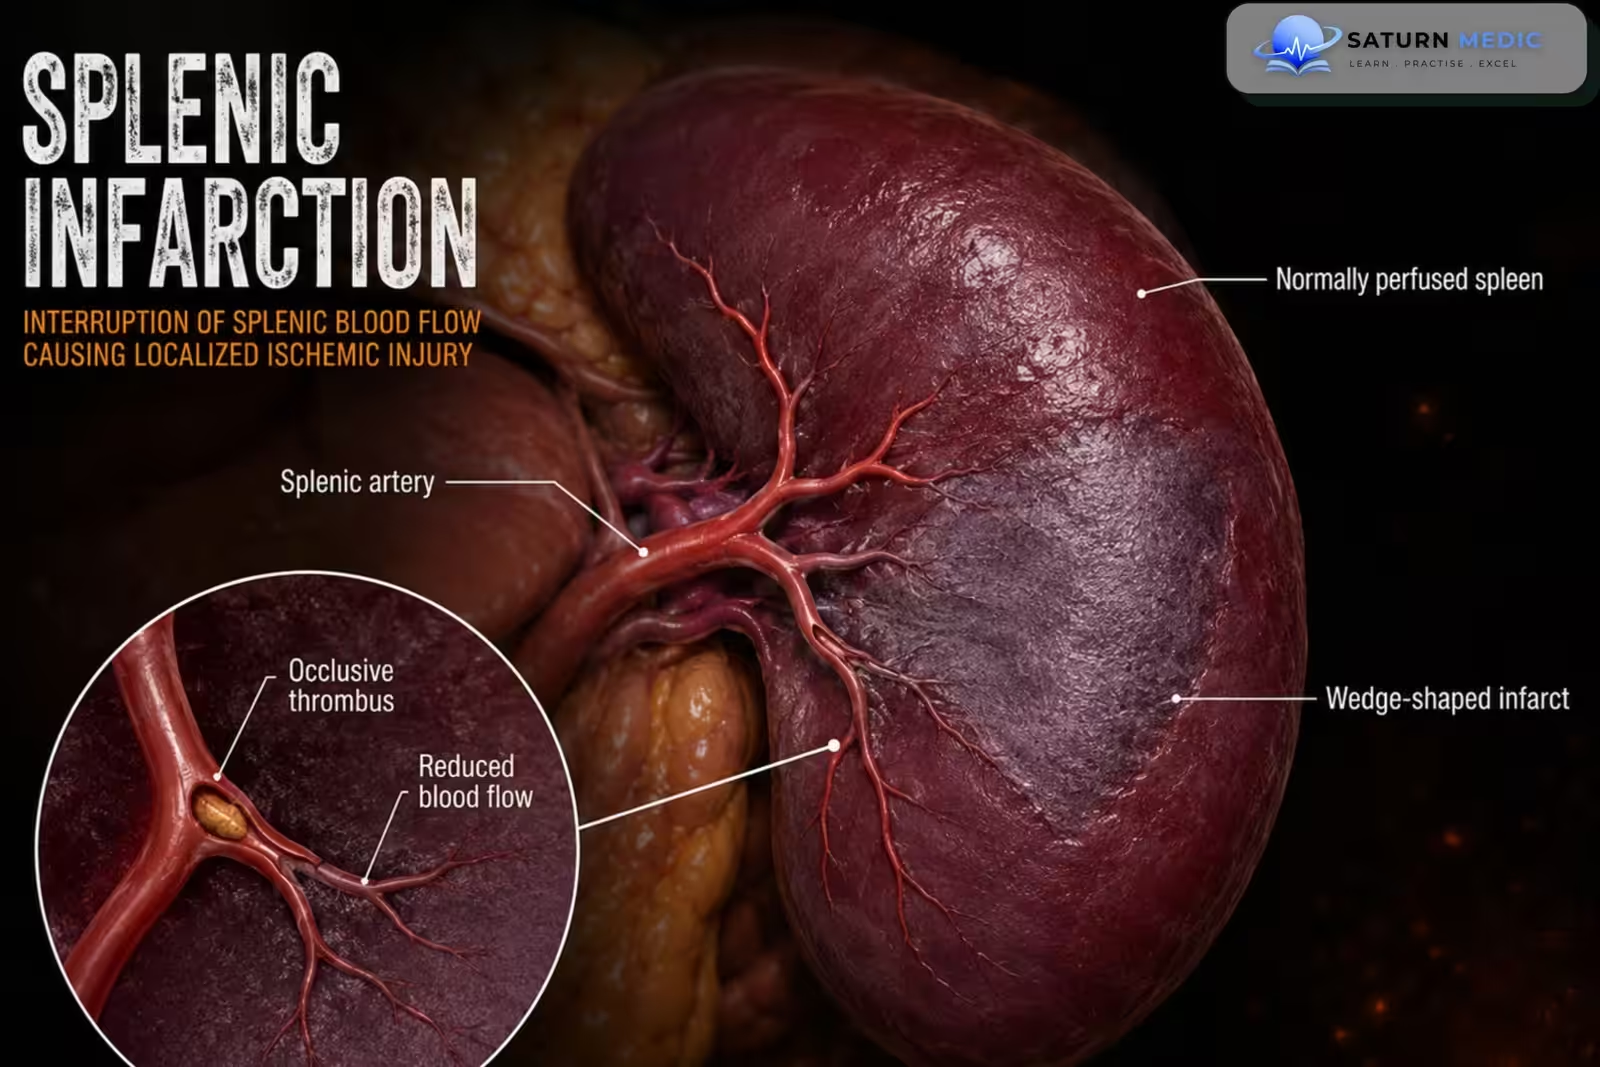
- Splenic infarction occurs when blood flow to part or all of the spleen is interrupted, causing ischemia and tissue necrosis. Patients commonly present with acute left upper-quadrant abdominal pain, sometimes radiating to the left shoulder. Contrast-enhanced CT is the preferred imaging test. Treatment mainly involves pain control and management of the underlying cause.
Etiology & Risk Factors
-Common Causes and Risk Factors
Atrial fibrillation
Infective endocarditis
Cardiac thromboembolism
Atherosclerotic embolism
Sickle cell disease
Polycythemia vera
Leukemia or lymphoma
Myeloproliferative disorders
Antiphospholipid syndrome
Factor V Leiden mutation
Protein C or protein S deficiency
Malignancy
Vasculitis
Splenic artery thrombosis
Pancreatitis
Abdominal trauma
Hypercoagulable states
Pathophysiology
Splenic arterial obstruction → reduced splenic blood flow → tissue ischemia → coagulative necrosis → local inflammation → left upper-quadrant pain and possible complications.
Clinical Presentation
Clinical Presentation
- Sudden or persistent left upper-quadrant pain
- Pain radiating to the left shoulder
- Left upper-quadrant tenderness
- Fever
- Nausea or vomiting
- Pleuritic left-sided chest pain
- Abdominal guarding in severe cases
- Some patients may be asymptomatic
History Taking
Ask about:
- Onset, severity, and duration of abdominal pain
- Radiation of pain to the left shoulder
- Fever, chills, nausea, or vomiting
- Previous thromboembolic events
- Atrial fibrillation or valvular heart disease
- Recent infection or infective endocarditis
- Sickle cell disease or hematological disorders
- Malignancy
- Recent abdominal trauma
- Use of anticoagulant medications
- Personal or family history of thrombophilia
Physical Examination
- General examination: Assess temperature, heart rate, blood pressure, hydration, pallor, and signs of sepsis or shock.Abdominal examination: Look for left upper-quadrant tenderness, guarding, rebound tenderness, abdominal distension, or splenomegaly.Cardiovascular examination: Assess for an irregular pulse, cardiac murmurs, or signs of infective endocarditis.Other examination: Look for signs of hematological disease, embolic phenomena, or underlying malignancy.
Investigations
-Laboratory Tests:
Complete blood count
C-reactive protein and ESR
Renal function and electrolytes
Liver function tests
Serum lactate
Coagulation profile
Blood cultures when fever or infective endocarditis is suspected
Peripheral blood smear
Thrombophilia testing in selected patients
ECG to detect atrial fibrillation
-Imaging:
- Contrast-enhanced CT abdomen is the preferred investigation. It usually shows a peripheral, wedge-shaped, low-attenuation area within the spleen.
- Abdominal ultrasound with Doppler may be used when CT is unavailable or contraindicated, but it is less sensitive during the early stage.
- Echocardiography should be considered when a cardiac embolic source or infective endocarditis is suspected.
Diagnosis
-Diagnosis is based on :
- compatible symptoms, risk factors, physical examination, and characteristic findings on contrast-enhanced CT.
- The underlying cause should also be identified because splenic infarction may be the first sign of atrial fibrillation, infective endocarditis, hematological malignancy, or a hypercoagulable disorder.
Related Topics
Management
Supportive Treatment
Analgesia
Adequate hydration
Antiemetics when required
Rest and clinical observation
Treat the Underlying Cause
Anticoagulation for thromboembolic or thrombotic causes when indicated
Antibiotics for infective endocarditis or splenic infection
Treatment of sickle cell crisis
Management of hematological or myeloproliferative disease
Treatment of the underlying malignancy or hypercoagulable state
Surgical or Interventional Treatment, Urgent surgical assessment is required for:
Splenic rupture
Hemodynamic instability
Splenic abscess
Persistent hemorrhage
Large symptomatic pseudocyst
Failure of conservative managemen
Complications
- Splenic abscess
- Splenic rupture
- Hemorrhage
- Splenic pseudocyst
- Sepsis
- Persistent abdominal pain
- Loss of splenic function after extensive infarction
Prognosis
- The prognosis is generally good in uncomplicated cases treated promptly.
- Outcome depends mainly on the size of the infarction, the underlying disease, and the development of complications.
- Splenic rupture, abscess, sepsis, and associated malignancy worsen the prognosis.
Key Points / Clinical Pearls
- Splenic infarction results from interruption of the splenic blood supply.
- Acute left upper-quadrant pain is the most common symptom.
- Atrial fibrillation, infective endocarditis, and hematological disorders are important causes.
- Contrast-enhanced CT is the preferred diagnostic investigation.
- Treatment is mainly supportive and directed at the underlying cause.
- Anticoagulation is used only when clinically indicated.
- Splenic abscess and rupture are serious complications requiring urgent treatment.
- Chapman J, Helm TA, Kahwaji CI. National Center for Biotechnology Information (NIH). Splenic Infarcts, StatPearls.
- Wand O, Tayer-Shifman OE, Khoury S, et al. A Practical Approach to Infarction of the Spleen as a Rare Manifestation of Multiple Common Diseases. Ann Med. 2018;50:494-500. PMID: 29929401.
- Yen CC, Wang CK, Chen SY, et al. Risk Assessment and Prognostic Analysis of Patients With Splenic Infarction in Emergency Department: A Multicenter Retrospective Study. Sci Rep. 2021;11:21423. PMID: 34728700.
- MedlinePlus, National Library of Medicine (NIH). Splenic Sequestration Crisis: Medical Encyclopedia.
- National Center for Biotechnology Information (NIH). Splenic Rupture, StatPearls.
Practice Splenic Infarction questions
Lock in what you just read with exam-style MCQs and active-recall flashcards from Saturn Medic.