
Clinical Subject Page

Cryptorchidism
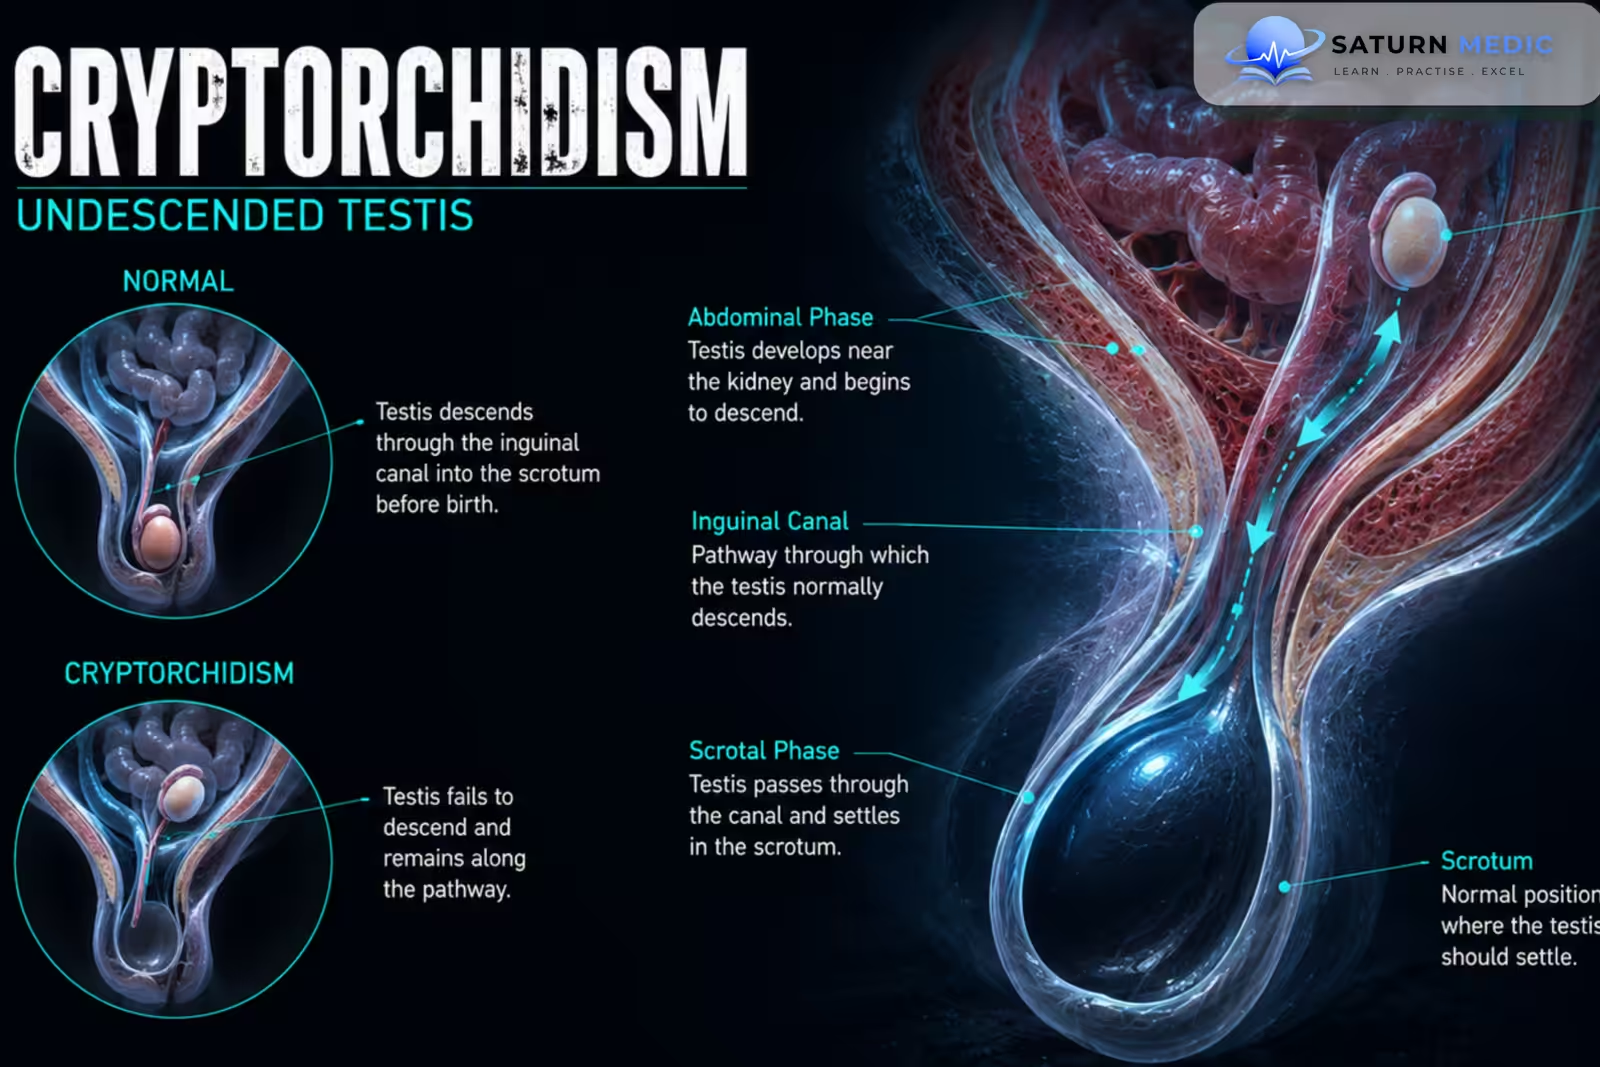
Cryptorchidism is the failure of one or both testes to descend into the scrotum. The undescended testis may be located anywhere along the normal pathway of testicular descent, most commonly in the inguinal canal.
Also called
ICD-10
Specialty
Onset
Reviewed
-
OverviewOverview
-
Etiology & Risk FactorsEtiology & Risk Factors
-
PathophysiologyPathophysiology
-
Clinical PresentationClinical Presentation
-
History TakingHistory Taking
-
Physical ExaminationPhysical Examination
-
InvestigationsInvestigations
-
DiagnosisDiagnosis
-
ManagementManagement
-
ComplicationsComplications
-
PrognosisPrognosis
-
Key Points / Clinical PearlsKey Points / Clinical Pearls
Overview
-Cryptorchidism is one of the most common congenital abnormalities affecting the male genital system.
It may be:
- Unilateral or bilateral
- Palpable or non-palpable
- Intra-abdominal, inguinal, or ectopic
-Most testes descend spontaneously during early infancy. A testis that remains undescended beyond early infancy is unlikely to descend spontaneously and usually requires specialist assessment and treatment.
Etiology & Risk Factors
-Etiology
–Cryptorchidism is multifactorial and may result from abnormal hormonal signaling, impaired anatomical development, or disruption of normal testicular descent during fetal development.
It is associated with:
- Prematurity
- Low birth weight
- Disorders of testicular development
- Endocrine abnormalities
- Genetic syndromes in selected cases
-Risk Factors
- Prematurity
- Low birth weight
- Family history
- Fetal growth restriction
- Associated genital abnormalities
Pathophysiology
Abnormal fetal testicular development or impaired descent → testis remains outside the scrotum → exposure to higher temperature → progressive germ-cell dysfunction and impaired spermatogenesis → increased risk of subfertility and testicular malignancy
Clinical Presentation
–Symptoms
Cryptorchidism is usually asymptomatic.
It is commonly identified as:
- Empty hemiscrotum
- Absent testis on routine examination
-Signs:
- One or both testes absent from the scrotum
- Palpable testis in the inguinal canal in some patients
- Underdeveloped hemiscrotum on the affected side
History Taking
-Ask about:
- Whether the testis has ever been seen or felt in the scrotum
- Age at diagnosis
- Prematurity or low birth weight
- Previous genital examination findings
- Previous inguinal or scrotal surgery
- Groin swelling
- Pain suggesting testicular torsion
- Family history of undescended testis
- Associated genital abnormalities
Physical Examination
-General Examination
- Assess for associated congenital abnormalities
- Assess genital development when clinically indicated
-System-Specific Examination:
- Examine the scrotum for both testes
- Palpate the inguinal canal
- Assess whether the testis is palpable
- Distinguish an undescended testis from a retractile testis
- Examine the contralateral testis
- Assess for associated inguinal hernia
Investigations
-Imaging
Ultrasound is not routinely recommended before specialist referral because it may not reliably locate a non-palpable testis.
Further imaging may occasionally be considered in selected cases.
-Special / Confirmatory Tests
Diagnostic laparoscopy is commonly used to locate and manage a non-palpable intra-abdominal testis.
Important Investigation Note
Cryptorchidism is primarily diagnosed by physical examination; routine ultrasound should not delay referral to a specialist.
Diagnosis
-Diagnosis is based on:
Absence of one or both testes from the scrotum + careful physical examination to determine whether the testis is palpable.
Further specialist assessment is required for non-palpable testes and suspected associated disorders.
Management
1. First-Line / Emergency Management
There is no routine emergency treatment.
Acute testicular or groin pain requires urgent assessment for Testicular Torsion.
2. Definitive Treatment
Orchiopexy is the definitive treatment.
The testis is surgically moved into the scrotum and fixed in position.
Early treatment is preferred, generally during infancy after the period when spontaneous descent is expected.
3. Medical Treatment
Hormonal therapy has a limited role and is not the routine definitive treatment for most cases.
4. Surgical / Procedural Treatment
Orchiopexy for palpable undescended testes
Laparoscopic exploration for non-palpable testes
Laparoscopic orchiopexy for selected intra-abdominal testes
Orchiectomy may be considered in selected postpubertal patients with a severely abnormal or non-viable testis
5. Supportive Management
Regular postoperative follow-up
Monitor testicular position and growth
Education regarding future testicular cancer awareness
Complications
- Subfertility
- Infertility
- Testicular malignancy
- Testicular torsion
- Inguinal hernia
- Testicular atrophy
- Psychological distress
Prognosis
The prognosis is generally good when Cryptorchidism is recognized and treated early. Fertility outcomes are usually better in unilateral disease than bilateral disease. The risk of testicular malignancy remains increased compared with the general population, even after successful orchiopexy, so long-term awareness and examination are important.
Key Points / Clinical Pearls
- Cryptorchidism is failure of one or both testes to descend into the scrotum.
- It may be unilateral or bilateral.
- The testis may be palpable or non-palpable.
- The inguinal canal is a common location for an undescended testis.
- Prematurity is an important risk factor.
- A retractile testis is different from a truly undescended testis.
- Cryptorchidism is usually diagnosed by physical examination.
- Routine ultrasound is not required before specialist referral.
- Bilateral non-palpable testes require evaluation for disorders of sexual development.
- Orchiopexy is the definitive treatment.
- Early surgical correction is preferred to protect fertility potential.
- An undescended testis has an increased risk of testicular torsion.
- Cryptorchidism increases the risk of subfertility and infertility.
- American Urological Association (AUA). Evaluation and Treatment of Cryptorchidism: AUA Guideline .
- European Association of Urology (EAU). EAU Guidelines on Paediatric Urology .
- Kolon TF, Herndon CDA, Baker LA, et al. Evaluation and Treatment of Cryptorchidism: AUA Guideline. J Urol. 2014;192(2):337-345. Journal of Urology .
- Hutson JM, Li R, Southwell BR, Petersen BL, Thorup J, Cortes D. The Pathogenesis of Undescended Testis: Further Hints From the Study of Animal Models. Int J Androl. 1997;20(6):309-316.
- Virtanen HE, Bjerknes R, Cortes D, et al. Cryptorchidism: Classification, Prevalence and Long-Term Consequences. Acta Paediatr. 2007;96(5):611-616. Acta Paediatrica .
- National Institute of Diabetes and Digestive and Kidney Diseases (NIDDK). Undescended Testicle (Cryptorchidism) . National Institutes of Health.
- National Library of Medicine (NIH). Cryptorchidism . StatPearls.