
Also called
Autoimmune hyperthyroidism
ICD-10
E05.0
Specialty
Endocrine
Onset
Chronic
Reviewed
August 2026
On This Page
-
OverviewOverview
-
Etiology & Risk FactorsEtiology & Risk Factors
-
PathophysiologyPathophysiology
-
Clinical PresentationClinical Presentation
-
History TakingHistory Taking
-
Physical ExaminationPhysical Examination
-
InvestigationsInvestigations
-
DiagnosisDiagnosis
-
ManagementManagement
-
ComplicationsComplications
-
PrognosisPrognosis
-
Key Points / Clinical PearlsKey Points / Clinical Pearls
What is Graves Disease?
–Graves Disease is the most common cause of hyperthyroidism.
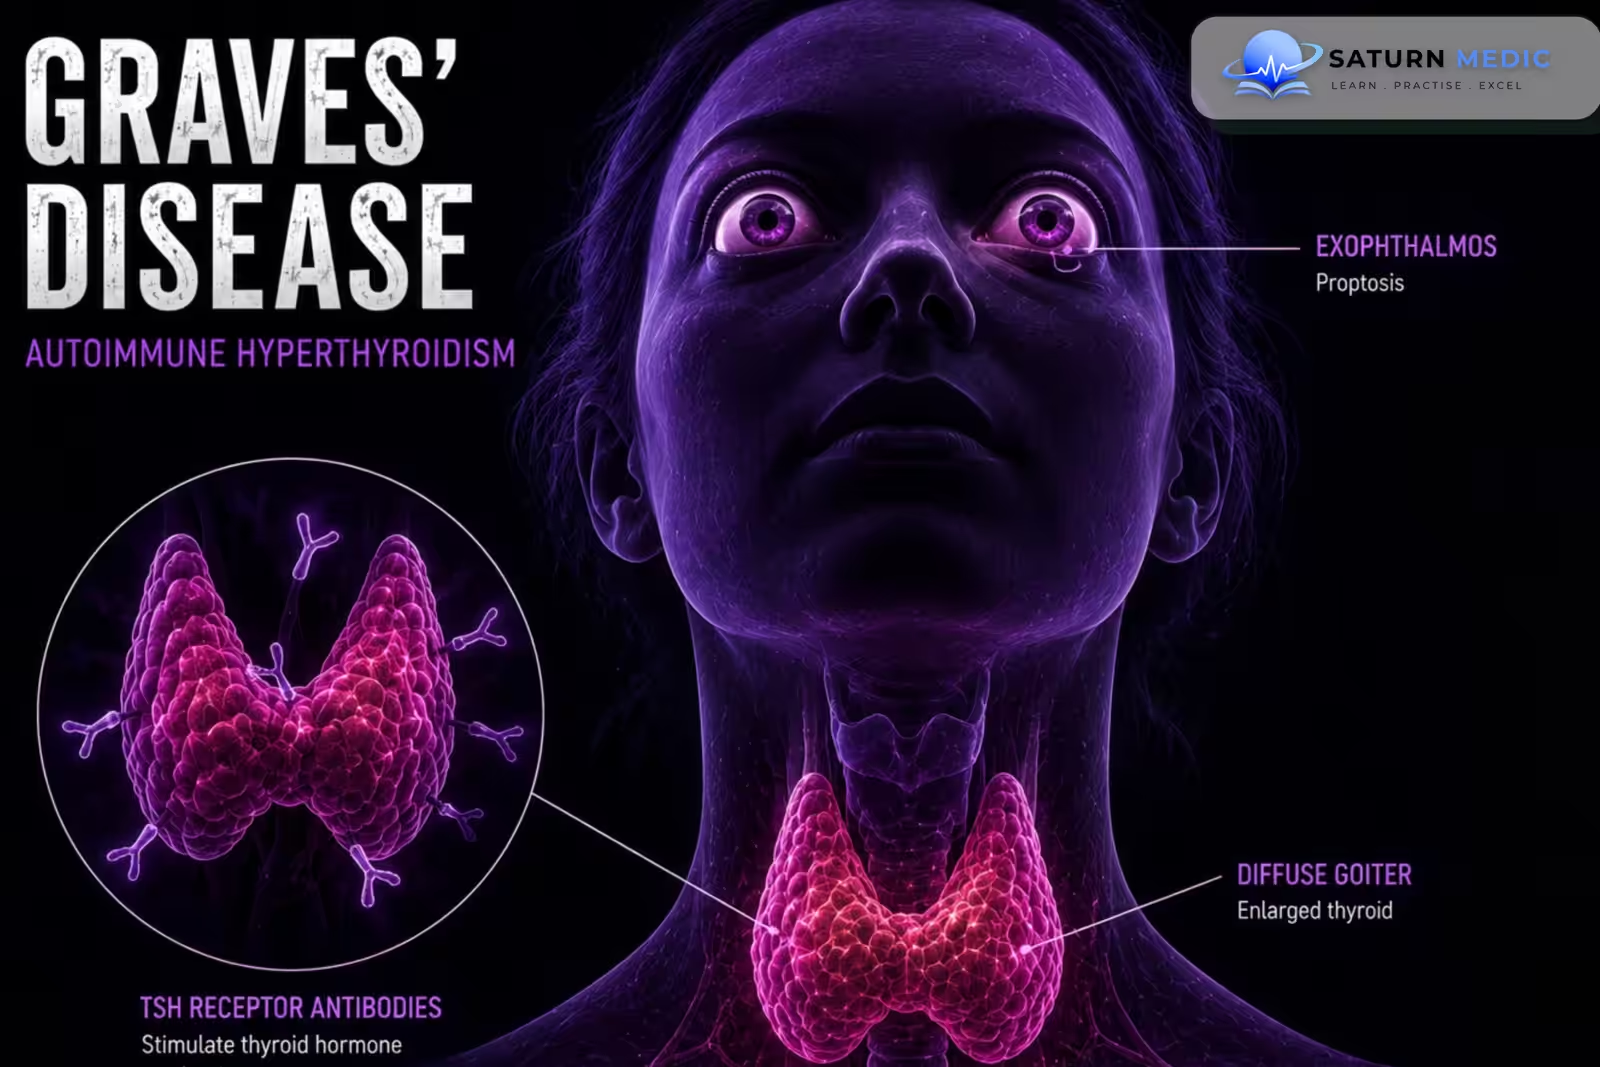
-It occurs when autoantibodies stimulate the TSH receptor on thyroid follicular cells, causing increased production of thyroid hormones (T3 and T4).
-It commonly presents with weight loss, heat intolerance, palpitations, tremor, and anxiety. It may also cause Graves ophthalmopathy and pretibial myxedema
Etiology & Risk Factors
-Etiology
•Graves Disease is caused by an autoimmune response in which antibodies bind to and activate the TSH receptor on thyroid follicular cells.
-These antibodies include:
• Thyroid-stimulating immunoglobulins (TSI)
• TSH receptor antibodies (TRAb)
-Activation of the TSH receptor causes:
• Increased thyroid hormone synthesis
• Increased thyroid gland growth
• Diffuse thyroid enlargement
-Risk Factors:
• Female sex
• Family history of Graves Disease or autoimmune thyroid disease
• Personal history of autoimmune disease
• Young to middle adulthood
• Pregnancy and postpartum period
• Smoking (strong risk factor for Graves ophthalmopathy)
• Excess iodine exposure
Pathophysiology
-Genetic susceptibility + environmental triggers
→ Loss of immune tolerance
→ Activation of autoreactive B and T lymphocytes
→ Production of TSH receptor antibodies (TSI/TRAb)
→ Antibodies stimulate TSH receptors on thyroid follicular cells
→ ↑ Thyroid hormone synthesis and release (↑ T3 and ↑ T4)
→ Negative feedback suppression of pituitary TSH
→ Low TSH + high thyroid hormones → Hypermetabolic state → symptoms of thyrotoxicosis
-Autoimmune inflammation of orbital tissues → Activation of fibroblasts and increased glycosaminoglycan deposition → Orbital tissue swelling → Graves ophthalmopathy
Clinical Presentation
-Symptoms:
• Weight loss despite increased appetite
• Heat intolerance
• Excessive sweating
• Palpitations
• Anxiety
• Irritability
• Tremor
• Fatigue
• Insomnia
• Increased bowel frequency
• Menstrual irregularities
-Signs:
• Tachycardia
• Fine tremor
• Warm, moist skin
• Weight loss
• Hyperactive reflexes
• Goiter
• Thyroid bruit due to increased vascularity
-Graves Ophthalmopathy
• Proptosis (exophthalmos)
• Periorbital swelling
• Eye irritation
• Diplopia
• Reduced eye movement in severe cases
History Taking
-Ask about:
• Weight loss
• Appetite changes
• Heat intolerance
• Sweating
• Palpitations
• Tremor
• Anxiety and irritability
• Sleep disturbance
• Bowel habit changes
Physical Examination
-General Examination:
• Assess weight and BMI
• Measure pulse and blood pressure
• Assess temperature
• Look for anxiety or agitation
• Observe for tremor
• Assess hydration status
-Thyroid Examination:
• Diffuse thyroid enlargement
• Soft, smooth goiter
• Thyroid bruit due to increased blood flow
-Cardiovascular:
• Tachycardia
• Irregular rhythm if atrial fibrillation occurs
• Signs of heart failure in severe disease
Investigations
-Biochemistry / Specific Tests
-Thyroid Function Tests:
-Typical findings:
Primary hyperthyroidism:
• ↓ TSH
• ↑ Free T4
• ↑ Free T3
-Thyroid-Stimulating Immunoglobulin (TSI)
• Positive in many patients.
• Supports the diagnosis of Graves Disease.
TSH Receptor Antibodies (TRAb)
• Useful for confirming Graves Disease.
• Helpful in pregnancy to assess fetal risk.
-Thyroid Peroxidase Antibodies (TPO Antibodies):
• May be positive.
• Less specific than TSI/TRAb.
-Imaging
Radioactive Iodine Uptake Scan
Shows:
• Diffuse increased uptake throughout the thyroid gland
-Useful for distinguishing Graves Disease from other causes of thyrotoxicosis.
-Thyroid Ultrasound
May show:
• Enlarged thyroid
• Increased blood flow on Doppler ultrasound
Diagnosis
-Graves Disease is diagnosed by:
• Clinical features of hyperthyroidism
• Thyroid function tests showing:
• Low TSH
• High free T4 and/or free T3
• Positive TSH receptor antibodies (TRAb/TSI)
Management
1. First-Line / Emergency Management
Stable Hyperthyroidism
-
Beta-blocker for symptom control.
-
Start antithyroid medication when indicated.
Thyroid Storm
-
Beta-blocker
-
Antithyroid drug
-
Iodine after antithyroid drug
-
Corticosteroids
-
Supportive care and treatment of the trigger
2. Definitive Treatment
-
Radioactive iodine: destroys thyroid tissue.
-
Thyroidectomy: preferred for large goiter, suspicious nodules/cancer, compressive symptoms, selected pregnancy cases, or severe ophthalmopathy.
3. Medical Treatment
-
Methimazole (MMI): First-line antithyroid drug in most patients.
-
Carbimazole: Prodrug of methimazole; commonly used outside the United States.
-
Propylthiouracil (PTU): Preferred during the first trimester of pregnancy and in thyroid storm.
-
Propranolol: Beta-blocker used for palpitations, tremor, and anxiety.
-
Atenolol: Beta-blocker used for symptomatic control.
4. Surgical / Procedural Treatment
Thyroidectomy for:
- Large goiter
- Suspected cancer
- Compressive symptoms
- Need for rapid definitive control
Complications
• Thyroid storm
• Atrial fibrillation
• Heart failure
• Osteoporosis
• Muscle weakness
Page 11
• Infertility
• Pregnancy complications
Prognosis
–Graves Disease has a good prognosis with appropriate treatment.
–Many patients achieve remission after antithyroid therapy, while others require definitive treatment.
-Prognosis depends on:
• Disease severity
• Goiter size
• Smoking status
• Presence of ophthalmopathy
Key Points / Clinical Pearls
• Graves Disease is the most common cause of hyperthyroidism.
• It is an autoimmune disease caused by TSH receptor stimulation.
• TSH receptor antibodies (TRAb) are the key diagnostic antibodies.
• Typical thyroid function pattern: ↓ TSH + ↑ Free T4/T3.
• Common symptoms include weight loss, heat intolerance, tremor, and palpitations.
• Graves Disease causes a diffuse, hyperfunctioning goiter.
• Graves ophthalmopathy is a characteristic extrathyroid manifestation.
• Smoking worsens Graves eye disease.
• Beta-blockers help control symptoms but do not treat the underlying cause.
- Ross DS, Burch HB, Cooper DS, et al. 2016 American Thyroid Association Guidelines for Diagnosis and Management of Hyperthyroidism and Other Causes of Thyrotoxicosis. Thyroid. 2016;26(10):1343-1421. Thyroid .
- Kahaly GJ, Bartalena L, Hegedüs L, Leenhardt L, Poppe K, Pearce SH. 2018 European Thyroid Association Guideline for the Management of Graves' Hyperthyroidism. Eur Thyroid J. 2018;7(4):167-186. European Thyroid Journal .
- Smith TJ, Hegedüs L. Graves' Disease. N Engl J Med. 2016;375(16):1552-1565. New England Journal of Medicine .
- Bartalena L, Kahaly GJ, Baldeschi L, et al. The 2021 European Group on Graves' Orbitopathy (EUGOGO) Clinical Practice Guidelines for the Medical Management of Graves' Orbitopathy. Eur J Endocrinol. 2021;185(4):G43-G67. European Journal of Endocrinology .
- National Institute of Diabetes and Digestive and Kidney Diseases (NIDDK). Graves' Disease . National Institutes of Health.
- National Library of Medicine (NIH). Graves Disease . StatPearls.
Practice Graves Disease questions
Lock in what you just read with exam-style MCQs and active-recall flashcards from Saturn Medic.