

Clinical Subject Page
Prostate Cancer
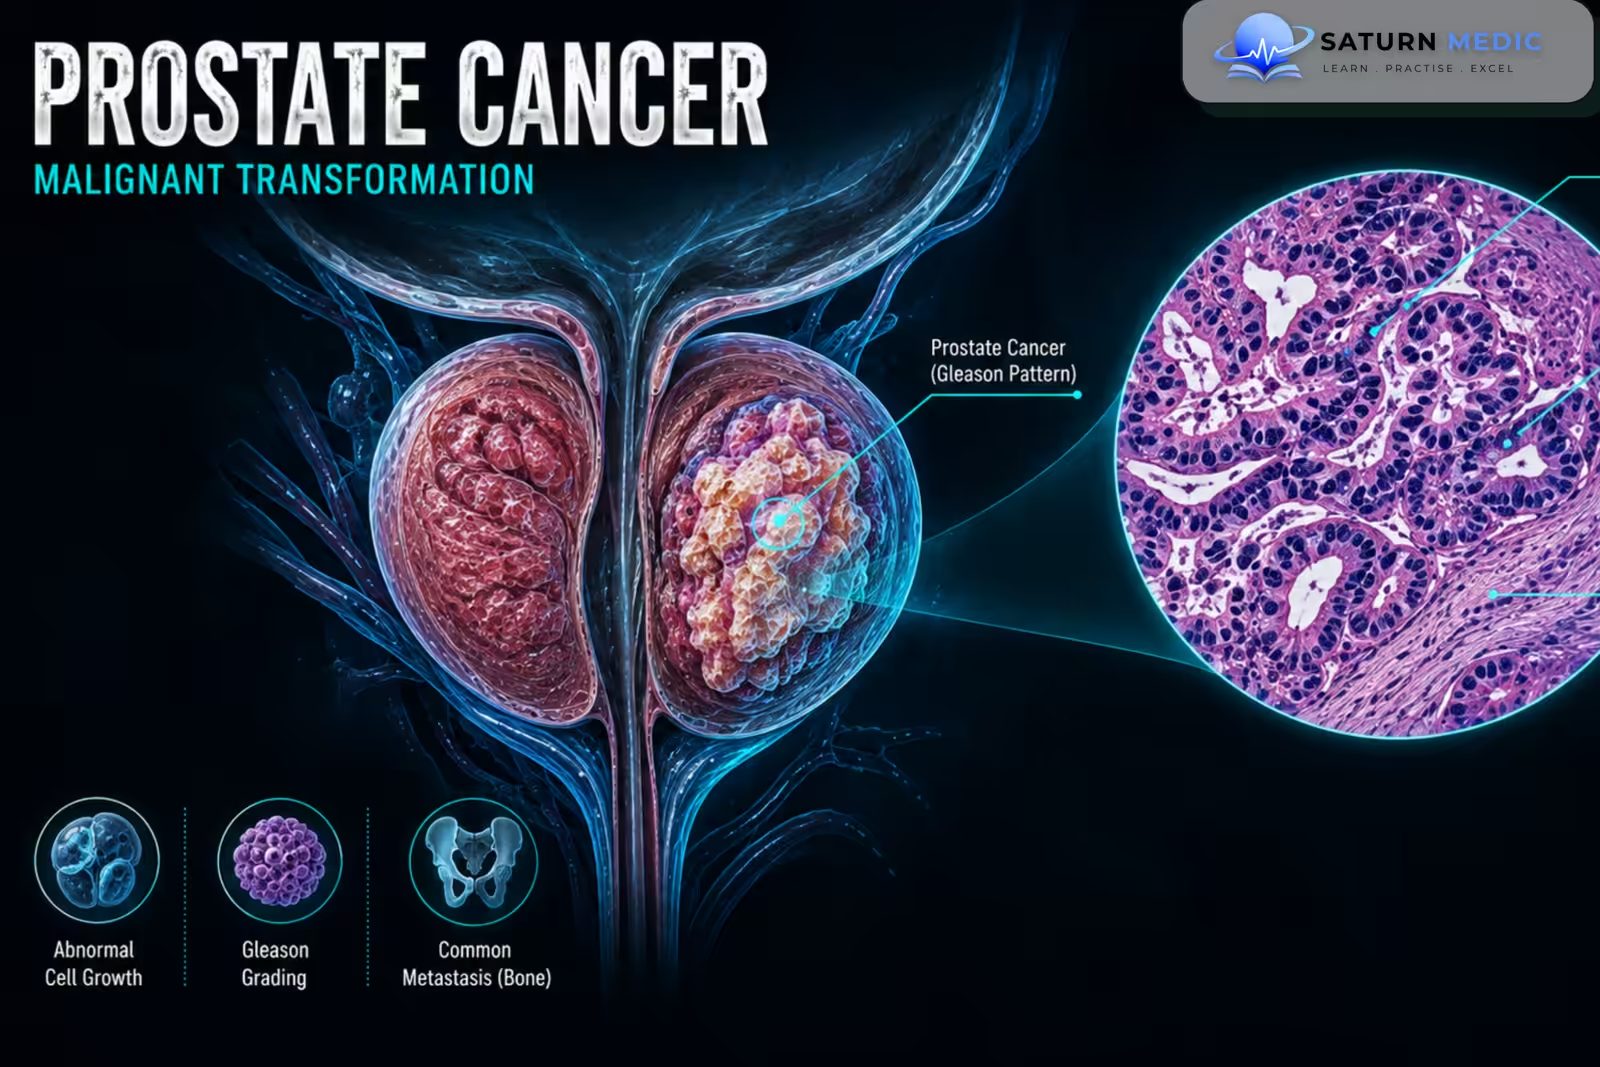
Prostate Cancer is a malignant tumor arising from the prostate gland, most commonly from the glandular epithelial cells. Most cases are adenocarcinomas. Prostate Cancer is one of the most common cancers affectingmen and may range from slow-growing localized disease to aggressive metastatic cancer
Also called
ICD-10
Specialty
Onset
Reviewed
-
OverviewOverview
-
Etiology & Risk FactorsEtiology & Risk Factors
-
PathophysiologyPathophysiology
-
Clinical PresentationClinical Presentation
-
History TakingHistory Taking
-
Physical ExaminationPhysical Examination
-
InvestigationsInvestigations
-
DiagnosisDiagnosis
-
ManagementManagement
-
ComplicationsComplications
-
PrognosisPrognosis
-
Key Points / Clinical PearlsKey Points / Clinical Pearls
Overview
Most Prostate Cancer develops in the peripheral zone of the prostate. Many tumors grow slowly, but some are clinically aggressive and can spread to regional lymph nodes, bones, and other organs.
The clinical significance of Prostate Cancer depends mainly on:
- Tumor stage
- Gleason grade / Grade Group
- Prostate-Specific Antigen (PSA) level
- Presence of metastasis
Etiology & Risk Factors
-Etiology
–The exact cause of Prostate Cancer is not fully understood. It develops through the accumulation of genetic and molecular abnormalities that cause uncontrolled growth of prostate cells.
Most cases are adenocarcinomas arising from the glandular epithelium.
-Risk Factors
- Increasing age
- Family history of Prostate Cancer
- Pathogenic variants such as BRCA2
- African ancestry
Pathophysiology
Genetic and molecular alterations → uncontrolled proliferation of prostate epithelial cells → adenocarcinoma formation → local tumor growth → invasion beyond the prostate → lymphatic and hematogenous spread → metastasis, commonly to bone
Clinical Presentation
-Symptoms:
-
Early Prostate Cancer is often asymptomatic.
When present, symptoms may include:
- Weak urinary stream
- Hesitancy
- Urinary frequency
- Nocturia
- Hematuria
- Hematospermia
- Erectile Dysfunction (ED)
Advanced disease may cause:
- Bone pain
- Weight loss
- Fatigue
- Neurological symptoms from spinal metastases
-Signs:
-
Abnormal findings on Digital Rectal Examination (DRE), such as:
- Hard prostate
- Irregular prostate
- Nodularity
- Asymmetry
History Taking
-Ask about:
- Lower urinary tract symptoms
- Hematuria or hematospermia
- Bone or back pain
- Unintentional weight loss
- Fatigue
- Erectile function
- Family history of Prostate Cancer
- Previous PSA results
- Previous prostate biopsy or imaging
Physical Examination
-General Examination
- Assess general condition and weight loss
- Look for signs of advanced malignancy
-System-Specific Examination:
- Perform Digital Rectal Examination (DRE)
- Assess for a hard, irregular, or nodular prostate
- Perform a focused neurological examination if spinal cord compression is suspected
Investigations
Biochemistry / Specific Tests
Prostate-Specific Antigen (PSA)
PSA is an important test for risk assessment but is not specific for cancer. It may also be elevated in Benign Prostatic Hyperplasia (BPH), prostatitis, and other conditions.
Alkaline Phosphatase (ALP)
May be elevated in extensive bone metastases.
-Imaging
Multiparametric Magnetic Resonance Imaging (mpMRI)
Used to identify suspicious lesions and guide biopsy.
-Staging Imaging
Computed Tomography (CT), Magnetic Resonance Imaging (MRI), bone scanning, or Prostate-Specific Membrane Antigen (PSMA) imaging may be used depending on the risk and stage of disease.
Special / Confirmatory Tests
Prostate Biopsy
Histological examination of prostate tissue confirms Prostate Cancer.
Biopsy results are graded using the Gleason scoring system and International Society of Urological Pathology (ISUP) Grade Groups.
Diagnosis
Prostate Cancer is assessed through:
PSA and clinical risk assessment → multiparametric MRI → targeted and/or systematic prostate biopsy → histological confirmation → staging and risk classification.
Diagnosis is confirmed by biopsy demonstrating malignant prostate cells.
Prostate Cancer · Gleason Grading — Patterns 1–5
Prostate Cancer · Gleason Score vs ISUP Grade Groups
| ISUP Grade Group | Gleason Score | Pattern | Risk | 5-yr Recurrence-free | Typical Management |
|---|---|---|---|---|---|
| 1 | ≤6 (3+3) | Only pattern 3 | Low | ~96% | Active surveillance |
| 2 | 7 (3+4) | Mostly 3, minor 4 | Intermediate favourable | ~88% | Surveillance or treatment |
| 3 | 7 (4+3) | Mostly 4, minor 3 | Intermediate unfavourable | ~63% | Radical treatment |
| 4 | 8 (4+4 / 3+5 / 5+3) | Pattern 4 only, or any 5 | High | ~48% | Radical + ADT |
| 5 | 9–10 (4+5 / 5+4 / 5+5) | Predominantly pattern 5 | Very high | ~26% | ADT + intensification |
Prostate Cancer · How to Calculate the Gleason Score
Pathologist assigns patterns to the two most predominant areas on biopsy
If a tertiary pattern is worse than the secondary → use it as secondary instead (upgrades score)
If only one pattern present → double it (e.g. pattern 3 only = score 6 / 3+3)
Order matters: 3+4 ≠ 4+3 — the primary pattern (first number) reflects the dominant tumour biology
Management
1. Definitive Treatment
Treatment depends on stage, risk group, life expectancy, comorbidities, and patient preference.
Localized Disease
Options include:
-
Active surveillance for selected low-risk disease
-
Radical prostatectomy
-
Radiotherapy
Locally Advanced Disease
Treatment may include:
-
Radiotherapy with Androgen Deprivation Therapy (ADT)
-
Radical prostatectomy in selected patients as part of multimodal treatment
Metastatic Disease
Systemic treatment is required.
2. Medical Treatment
Important systemic treatments include:
-
Androgen Deprivation Therapy (ADT)
-
Androgen receptor pathway inhibitors
-
Chemotherapy in selected patients
-
Bone-targeted treatment when indicated
3. Surgical / Procedural Treatment
Radical Prostatectomy
Removal of the prostate and selected surrounding tissues.
Other procedures may be required to manage complications such as urinary obstruction or spinal compression.
4. Supportive Management
-
PSA monitoring
-
Management of treatment-related Erectile Dysfunction (ED)
-
Management of urinary incontinence
-
Bone health assessment
Complications
- Local tumor progression
- Urinary obstruction
- Hematuria
- Bone metastases
- Pathological fractures
- Spinal cord compression
- Lymph node metastases
- Cancer-related weight loss
Prognosis
The prognosis of Prostate Cancer varies widely. Localized and low-risk disease generally has an excellent prognosis, while metastatic or high-grade disease has a lessfavorable outcome. Important prognostic factors include tumor stage, Grade Group, PSA level, metastatic status, and response to treatment.
Key Points / Clinical Pearls
- Prostate Cancer is usually an adenocarcinoma of the prostate gland.
- It commonly arises in the peripheral zone.
- Increasing age is the most important risk factor.
- Family history and BRCA2 variants increase risk.
- Early Prostate Cancer is often asymptomatic.
- Lower urinary tract symptoms do not reliably indicate cancer.
- A hard or nodular prostate on DRE is suspicious.
- PSA is useful for assessment but is not diagnostic alone.
- Multiparametric MRI helps identify suspicious lesions.
- Prostate biopsy confirms the diagnosis.
- Gleason score and Grade Group help assess tumor aggressiveness.
- Active surveillance is appropriate for selected low-risk disease.
- European Association of Urology (EAU). EAU Guidelines on Prostate Cancer.
- American Urological Association (AUA). Clinically Localized Prostate Cancer Guideline.
- National Comprehensive Cancer Network (NCCN). NCCN Guidelines for Prostate Cancer.
- Mottet N, et al. EAU-EANM-ESTRO-ESUR-ISUP-SIOG Guidelines on Prostate Cancer. PubMed.
- National Cancer Institute (NCI). Prostate Cancer.