

Clinical Subject Page
Hypertensive Nephrosclerosis
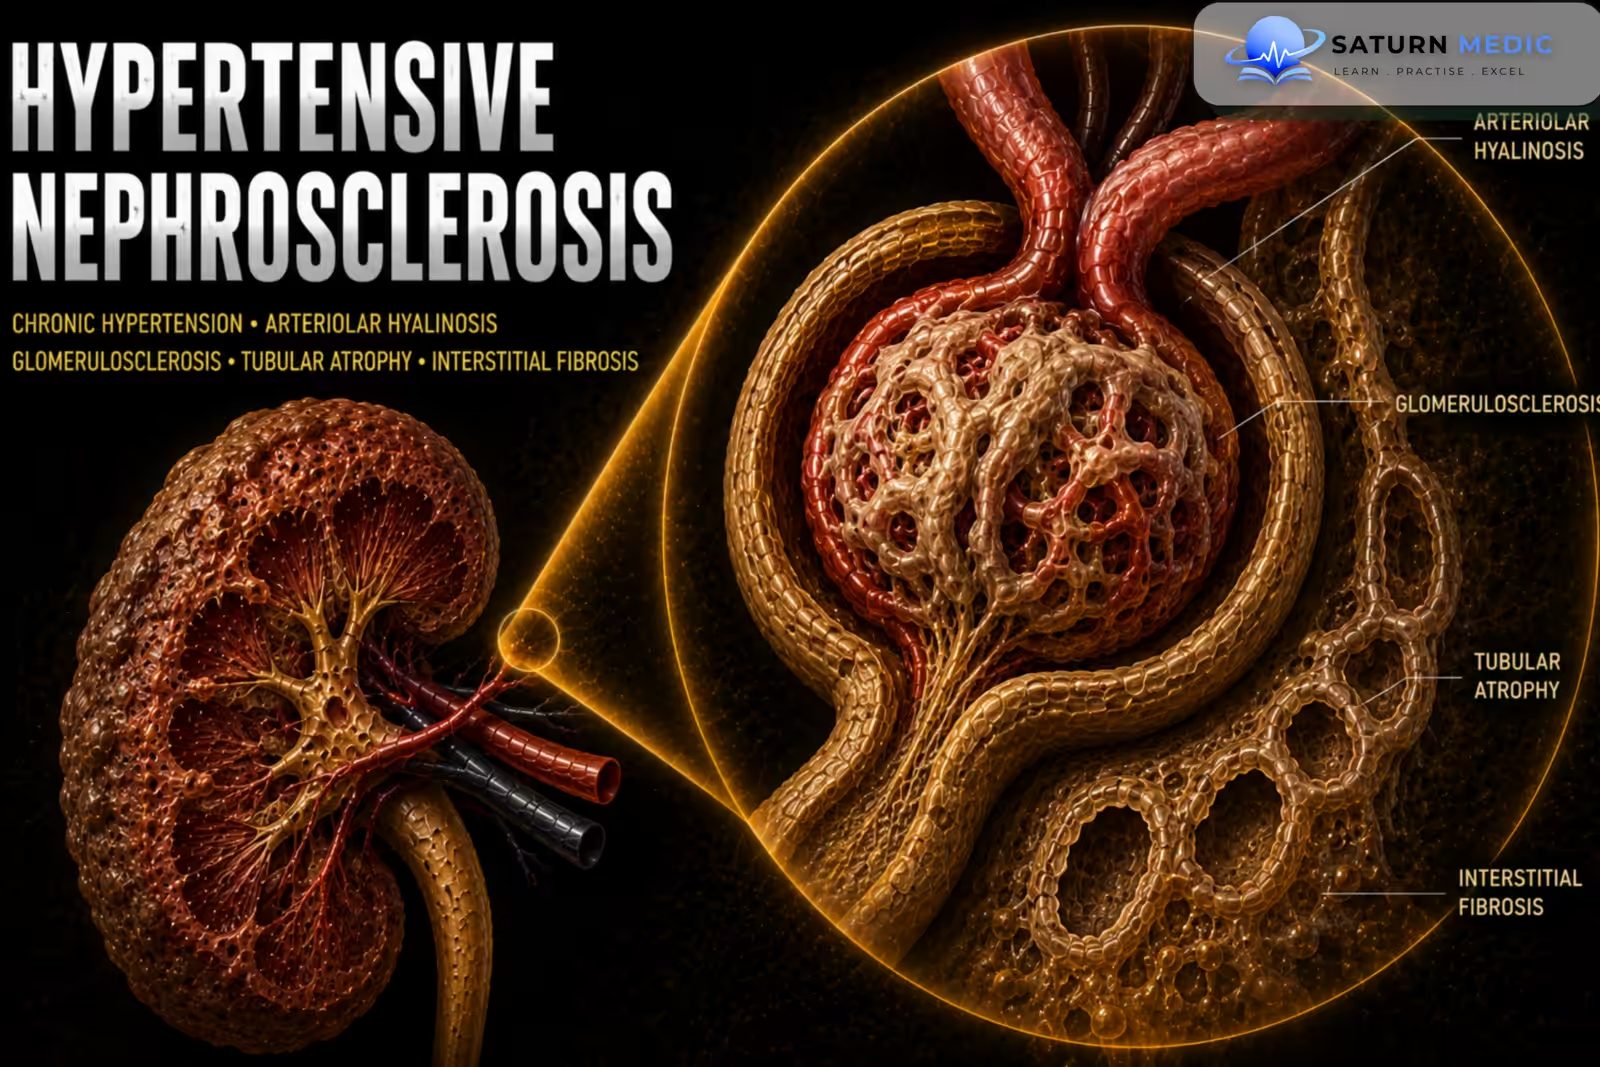
Hypertensive Nephrosclerosis is chronic kidney damage caused by long-standing hypertension, resulting in progressive narrowing and sclerosis of the renal arterioles and glomeruli. It can lead to Chronic Kidney Disease (CKD) and, in advanced cases, kidney failure
Also called
ICD-10
Specialty
Onset
Reviewed
-
OverviewOverview
-
Etiology & Risk FactorsEtiology & Risk Factors
-
PathophysiologyPathophysiology
-
Clinical PresentationClinical Presentation
-
History TakingHistory Taking
-
Physical ExaminationPhysical Examination
-
InvestigationsInvestigations
-
DiagnosisDiagnosis
-
ManagementManagement
-
ComplicationsComplications
-
PrognosisPrognosis
-
Key Points / Clinical PearlsKey Points / Clinical Pearls
Overview
-Hypertensive Nephrosclerosis develops after prolonged elevation of blood pressure causes structural damage to the renal vasculature.
-It is characterized by:
- Arteriolar hyalinosis
- Arterial intimal thickening
- Glomerulosclerosis
- Progressive nephron loss
-It usually causes slowly progressive kidney dysfunction with relatively modest proteinuria.
Etiology & Risk Factors
-Etiology:
Persistent hypertension causes chronic vascular injury, particularly affecting small renal arteries and arterioles. This reduces renal blood flow and produces ischemic glomerular and tubular injury.
-Risk Factors
- Long-standing hypertension
- Poor blood pressure control
- Severe or resistant hypertension
- Diabetes mellitus
- Older age
- Smoking
Pathophysiology
Chronic hypertension → renal arteriolar injury → hyaline deposition and vascular wall thickening → renal ischemia → glomerulosclerosis and tubular atrophy → nephron loss → declining GFR → Chronic Kidney Disease (CKD)
Clinical Presentation
-Symptoms:
Early disease is often asymptomatic.
Progressive disease may cause:
- Fatigue
- Nocturia
- Reduced exercise tolerance
- Peripheral edema in advanced disease
- Symptoms of uremia in severe disease
-Signs:
- Persistent hypertension
- Hypertensive retinopathy
- Mild peripheral edema in advanced disease
- Features of Chronic Kidney Disease (CKD)
History Taking
-Ask about:
- Duration and severity of hypertension
- Previous blood pressure measurements
- Medication adherence
- Resistant hypertension
- Diabetes mellitus
- Cardiovascular disease
- Smoking
- Previous kidney disease
- Urinary symptoms
- NSAID and other nephrotoxic medication use
Physical Examination
-General Examination
- Blood pressure
- Peripheral edema
- Weight and volume status
-System-Specific Examination:
- Fundoscopy for hypertensive retinopathy
- Cardiovascular examination for hypertensive heart disease
- Assessment for signs of Chronic Kidney Disease (CKD)
Investigations
-Biochemistry / Specific Tests
- Serum creatinine and eGFR
- Serum potassium
- Serum bicarbonate
- Urinalysis
- Urine albumin-to-creatinine ratio (ACR)
- Serum electrolytes
- Lipid profile when assessing cardiovascular risk
-Imaging
Renal ultrasound may assess kidney size and exclude structural abnormalities or urinary obstruction.
Typical chronic disease may show small, echogenic kidneys.
-Special / Confirmatory Tests
Kidney biopsy is not routinely required.
It may be considered when the clinical presentation is atypical or another glomerular disease is suspected.
Diagnosis
-Diagnosis of Hypertensive Nephrosclerosis is primarily clinical and based on:
- Long-standing hypertension
- Progressive decline in kidney function
- Relatively modest proteinuria
- Absence of findings strongly suggesting another primary kidney disease
- Supportive evidence of chronic hypertensive vascular disease
Kidney biopsy is generally unnecessary unless the presentation is atypical.
Management
1. Definitive Treatment
The main treatment is strict blood pressure control and prevention of further kidney damage.
Optimize antihypertensive therapy
Reduce albuminuria
Control cardiovascular risk factors
Treat diabetes when present
Avoid nephrotoxins
2. Medical Treatment
ACE inhibitors or ARBs when albuminuria is present
Calcium channel blockers
Thiazide-type diuretics when appropriate
Loop diuretics in advanced CKD or significant fluid overload
Other antihypertensive agents according to blood pressure control needs
Statins for appropriate cardiovascular risk reduction
3. Surgical / Procedural Treatment
No routine surgical treatment.
Kidney replacement therapy may be required if kidney failure develops.
4. Supportive Management
Regular blood pressure monitoring
Sodium restriction
Smoking cessation
Weight management
Avoid NSAIDs and other nephrotoxins
Monitor eGFR and urine ACR
Manage cardiovascular risk factors
Complications
- Chronic Kidney Disease (CKD)
- Kidney failure
- Severe hypertension
- Proteinuria
- Hyperkalemia
- Metabolic acidosis
- Fluid overload
- Cardiovascular disease
- Hypertensive retinopathy
- Uremia
Prognosis
–Prognosis of Hypertensive Nephrosclerosis depends mainly on the severity and duration of hypertension, degree of kidney dysfunction, albuminuria, and cardiovascular comorbidity
–Good blood pressure control can significantly slow progression, while uncontrolled hypertension may lead to progressive Chronic Kidney Disease (CKD) and kidney failure.
Key Points / Clinical Pearls
- Hypertensive Nephrosclerosis is chronic kidney damage caused by long-standing hypertension.
- Persistent hypertension damages renal arteries and arterioles.
- Arteriolar hyalinosis and vascular wall thickening are characteristic pathological changes.
- Progressive vascular injury causes renal ischemia and glomerulosclerosis.
- Early disease is often asymptomatic.
- Hypertension is usually the dominant clinical finding.
- Kidney dysfunction typically develops gradually.
- Proteinuria is usually low-grade to moderate.
- Heavy proteinuria should prompt investigation for another renal disease.
- Serum creatinine and eGFR assess kidney function.
- Urine ACR helps assess albuminuria and prognosis.
- Kidney biopsy is usually unnecessary.
- Blood pressure control is the cornerstone of treatment.
- Kidney Disease: Improving Global Outcomes (KDIGO) Blood Pressure Work Group. KDIGO 2021 Clinical Practice Guideline for the Management of Blood Pressure in Chronic Kidney Disease. Kidney Int. 2021;99(3S):S1-S87. KDIGO .
- Unger T, Borghi C, Charchar F, et al. 2020 International Society of Hypertension Global Hypertension Practice Guidelines. Hypertension. 2020;75(6):1334-1357. Hypertension .
- Ku E, Lee BJ, Wei J, Weir MR. Hypertension in CKD: Core Curriculum 2021. Am J Kidney Dis. 2021;78(4):576-585. American Journal of Kidney Diseases .
- Bidani AK, Griffin KA. Pathophysiology of Hypertensive Renal Damage: Implications for Management. J Hum Hypertens. 2004;18:759-766.
- National Institute of Diabetes and Digestive and Kidney Diseases (NIDDK). High Blood Pressure & Kidney Disease . National Institutes of Health.
- National Library of Medicine (NIH). Hypertensive Nephrosclerosis . StatPearls.